Related Experiment Video
Updated: Jul 19, 2026
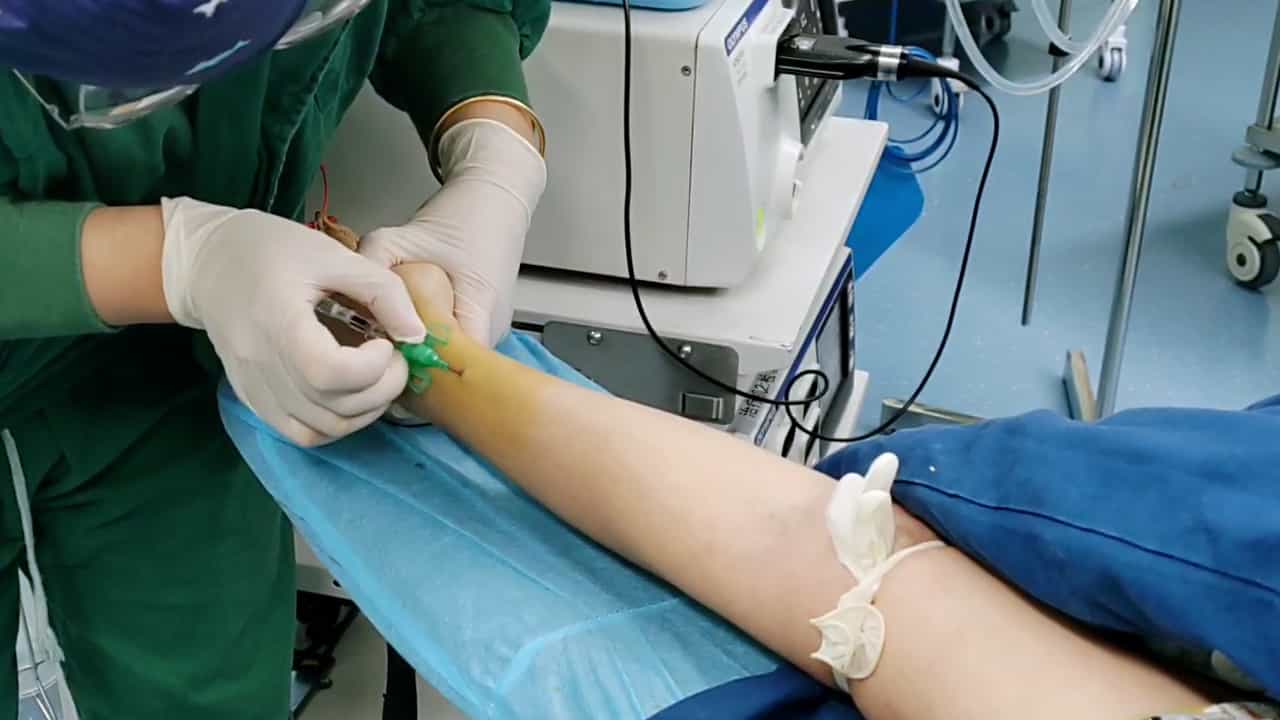

Improved Hysteroscopic Resection of Endometrial Polyps Using 6-Fr Micro-Scissors and Forceps
Published on: August 2, 2024
[Endometrial hyperplasia: A review]
1Service de Gynécologie Obstétrique, Hôpital Pellegrin, CHU de Bordeaux, place Amélie-Raba-Léon, 33076 Bordeaux. jean-luc.brun@chu-bordeaux.fr

Abstract:
Endometrial hyperplasias can be divided into two categories based on the presence or absence of cytological atypia and further classified as simple or complex according to the extent of architectural abnormalities. They are usually diagnosed because of irregular bleeding in perimenopause. Hysteroscopy with a biopsy gives a more accurate diagnosis than transvaginal ultrasonography, sonohysterography, or blind curettage. Endometrial hyperplasias with no cytological atypia, regarded as a response to unopposed endogenous estrogenic stimulation, are normally treated with progestins. The intra-uterine route (levonorgestrel intra-uterine system) is more effective and better tolerated than the oral route. Either conservative surgery (endometrial resection, thermal ablation) or radical surgery (hysterectomy) in the case of other genital diseases is performed on women who did not respond to medical treatment. Endometrial hyperplasias with cytological atypia, considered as intra-epithelial neoplasias, are traditionally treated by hysterectomy. The absence of management protocols in the literature offers various treatment options and indications. Gonadotropin-releasing hormone agonists, danazol, or aromatase inhibitor are effective, but have adverse effects and are expensive. Endometrial ablation can be performed as a first line therapy in women suffering from bleeding related to hyperplasia without cytological atypia. Medical treatment may be offered to young women suffered from hyperplasias with cytological atypia and desiring pregnancy.

Related Concept Videos
 01:26
Cellular Adaptation III: Hyperplasia
 01:24
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:19
Histology of the Uterus
The endometrium is the...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:24
Disorders of the Female Reproductive System