Related Experiment Video
Updated: Jul 19, 2026
Metacarpal Small Incision for Carpal Tunnel Syndrome
Published on: April 5, 2024
[The endoscopic release of the transverse carpal ligament for carpal tunnel syndrome.]
1Kreiskrankenhaus Gummersbach, Klinik für Unfall-, Hand- und Wiederherstellungschirurgie, Wilhelm-Breckow-Allee 20, D-51643, Gummersbach.

Goal Of Surgery:
Complete division of the flexor retinaculum for decompression of the medial nerve to restore normal neurologic function.
Indications:
Idiopathic and posttraumatic carpal tunnel syndrome.
Contraindications:
Postoperative recurrence, carpal tunnel syndrome in patients with rheumatoid arthritis, with tumors or with carpal canal compromise due to bony causes.
Positioning And Anaesthesia:
Supine General or regional anaesthesia.
Surgical Technique:
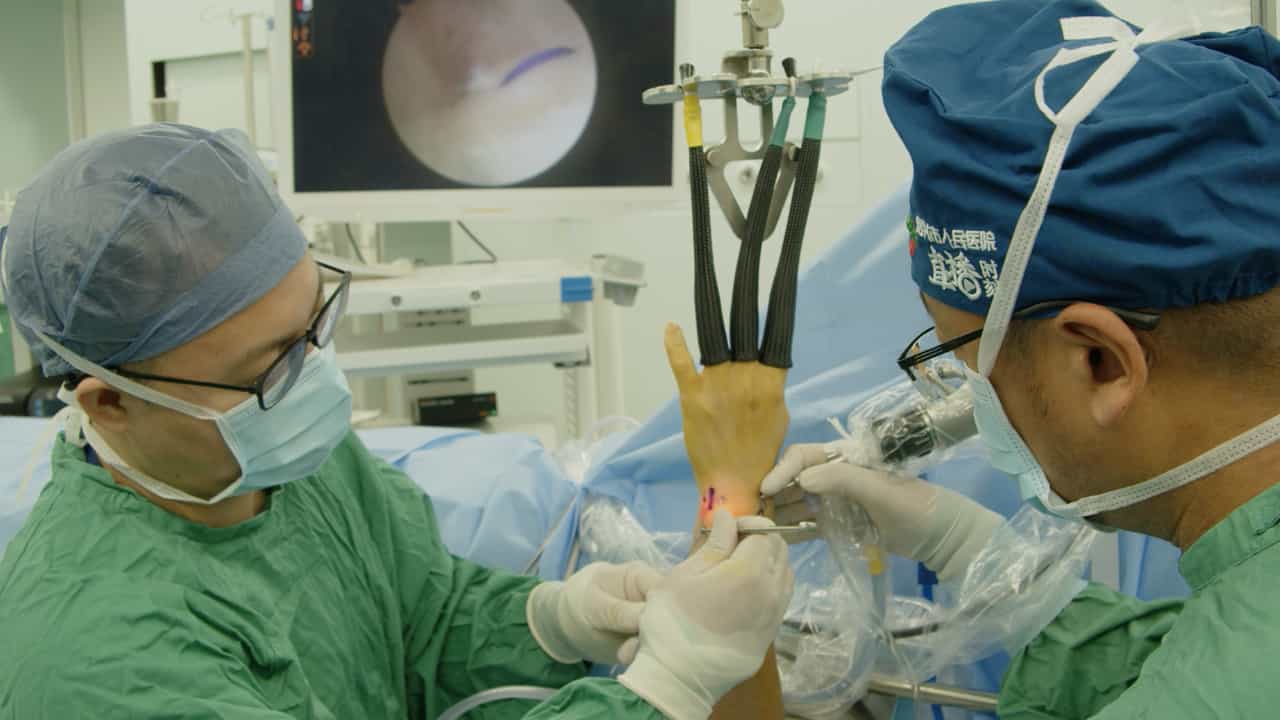
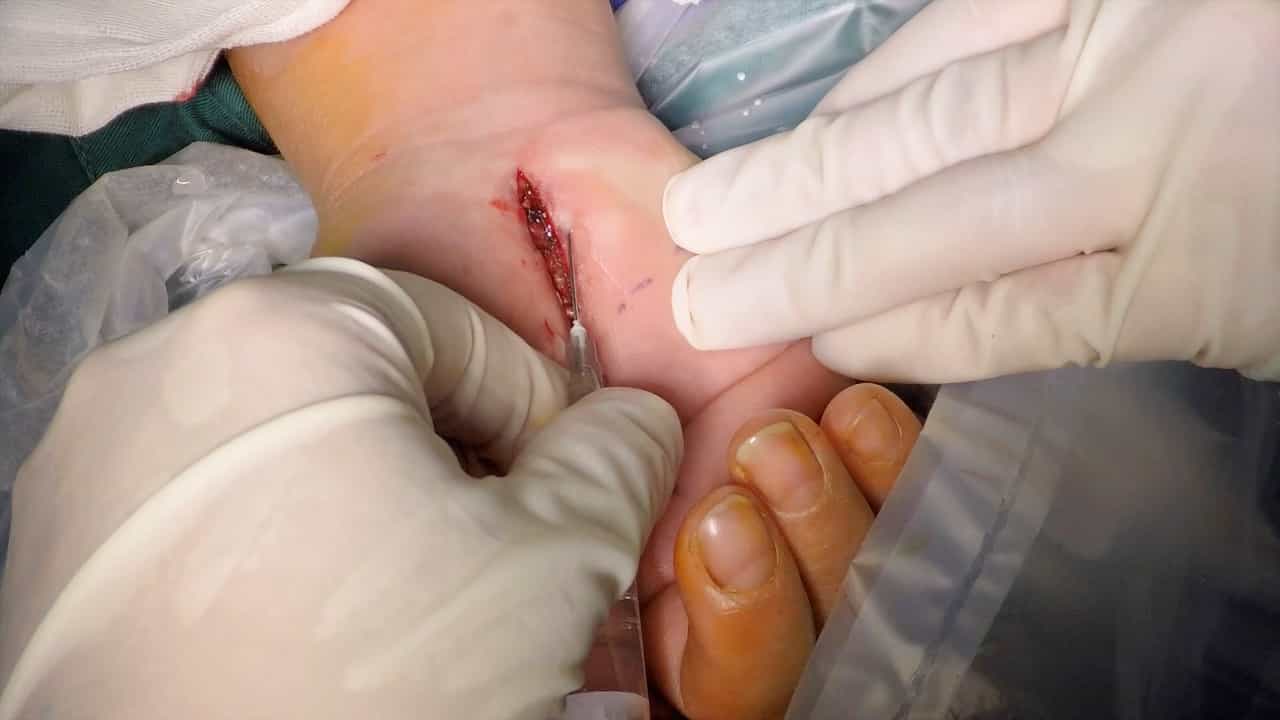
Identification of the palmaris longus tendon. 1.5 cm long incision along the flexor crease of the wrist. If the palmaris longus is absent the incision should be made 1.5 cm medial to the flexor carpi radialis tendon. Introduction of the scope and exploration of the ulnar border of the carpal canal with a special instrument until the hook of the hamate has been identified. Endoscopic identification of the distal end of the retinaculum and insertion of the cutter. Complete division of the retinaculum.
Postoperative Management:
Posterior plaster splint for 7 days. Elevation of the limb. Active exercises of fingers, elbow and shoulder and, after cast removal, also of the wrist. Lifting and carrying of heavy objects should be avoided for 4 to 6 weeks.
Possible Complications:
Injury of the median nerve or one of its branches, of the superficial palmar arch, and of the flexor tendons.
Results:
Prospective randomized study of 120 patients of which 101 could be followed up. Forty-five patients (group A) had an open decompression and 47 (group B) were decompressed endoscopically. Average follow-up period for group A 271 days, for group B 275 days. Mean age of both groups: 53 years. There were 13 men and 41 women in group A and 17 men and 30 women in group B. No complications or night pain in either group. No significant difference in atrophy of the thenar eminence in the strength of the hand or in the 2 point discrimination. Results of pre- and postoperative nerve conduction and of temporary disability are listed in Figures 10 and 11. At follow-up 6 to 12 weeks postoperatively no difference could be found between the 2 groups in respect to scar pain, grip power and range of motion. Main advantage of the endoscopic approach: reduced postoperative pain and shorter disability.