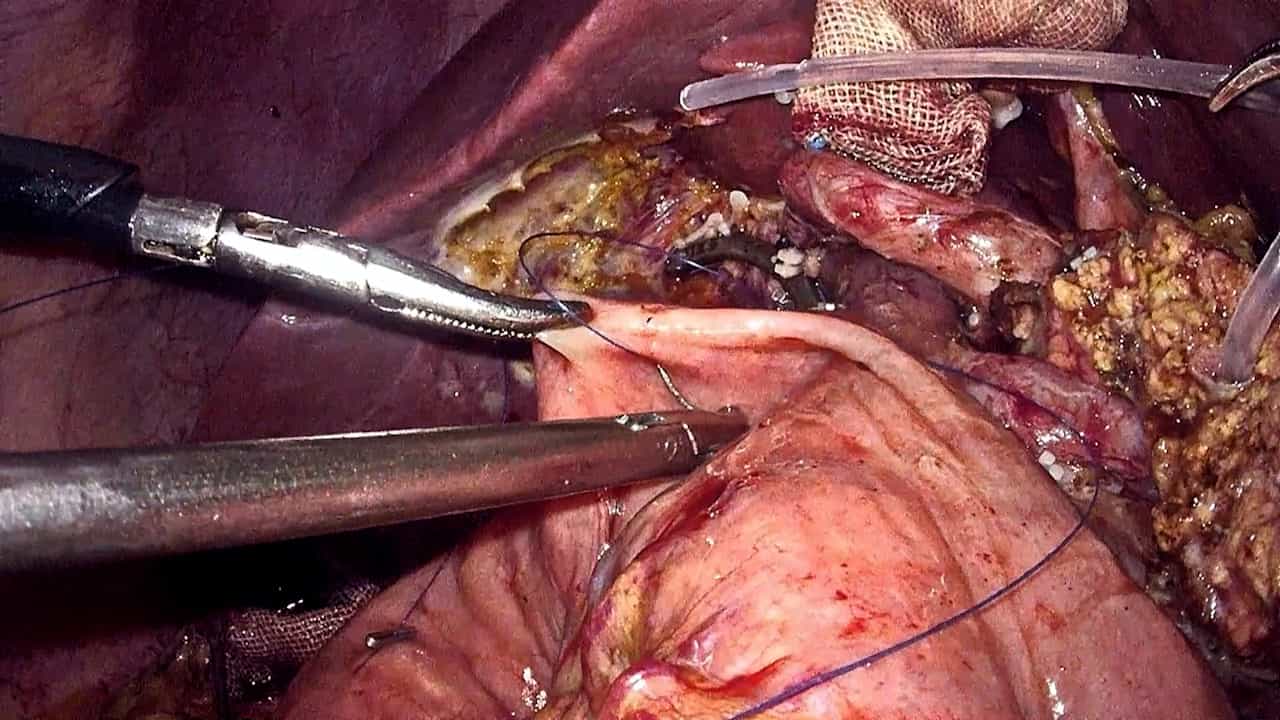
Current management of pancreatic fistula after pancreaticoduodenectomy
Gerard V Aranha1, Joshua M Aaron, Margo Shoup
1Division of Surgical Oncology, the Department of Surgery, Loyola University, Maywood, Illinois, USA. garanha@lumc.edu

Insights
Pancreatic fistula (PF) after pancreaticoduodenectomy (PD) is a serious complication. Most cases can be managed conservatively with diet or nutrition, avoiding surgery.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Abdominal Surgery
Background:
- Pancreatic fistula (PF) is a significant complication following pancreaticoduodenectomy (PD).
- Effective management strategies for PF post-PD are crucial for patient outcomes.
Purpose of the Study:
- To outline the management approach for pancreatic fistula (PF) after pancreaticoduodenectomy (PD).
- To analyze the outcomes associated with PF following PD.
Main Methods:
- Retrospective review of 396 patients undergoing PD.
- Comparison of preoperative, intraoperative, and postoperative outcomes between patients with and without PF.
Main Results:
- 16% of patients developed PF, with higher incidence for certain neoplasms.
- PF was associated with increased complications, longer hospital stays, and greater blood loss.
- Conservative management (oral diet or parenteral nutrition) was successful for most PF patients.
Conclusions:
- Pancreatic fistula is a serious complication of PD, linked to significant mortality and morbidity.
- Conservative management strategies are effective for the majority of patients experiencing PF post-PD.
Background:
Pancreatic fistula (PF) is a major and serious complication following pancreaticoduodenectomy (PD). The purpose of this study was to outline our management of PF after PD.
Methods:
A retrospective review of a prospectively collected database of 396 patients undergoing PD for various indications at Loyola University Medical Center and Hines Veterans Administration Hospital from July 1, 1990, to December 31, 2005. Patients were divided group 1 (no PF) and group 2 (PF). Each group was compared regarding preoperative, intraoperative, and postoperative outcomes.
Results:
Of the patients included in the study, 65 patients (16%) developed a PF. PF was more common after PD for ampullary neoplasms (28%), duodenal neoplasms (35%), and serous cystic neoplasms (44%), and was uncommon after PD for pancreatic cancer (6%). Associated complications with PF was 51% when compared with patients with no PF (21%; P
Conclusions:
PF is a serious complication after PD and is associated with substantial mortality and other complications. The majority of patients with PF can be managed conservatively with either maintenance of oral diet or parenteral nutrition until closure of the PF.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease