Related Experiment Video
Updated: Jul 19, 2026
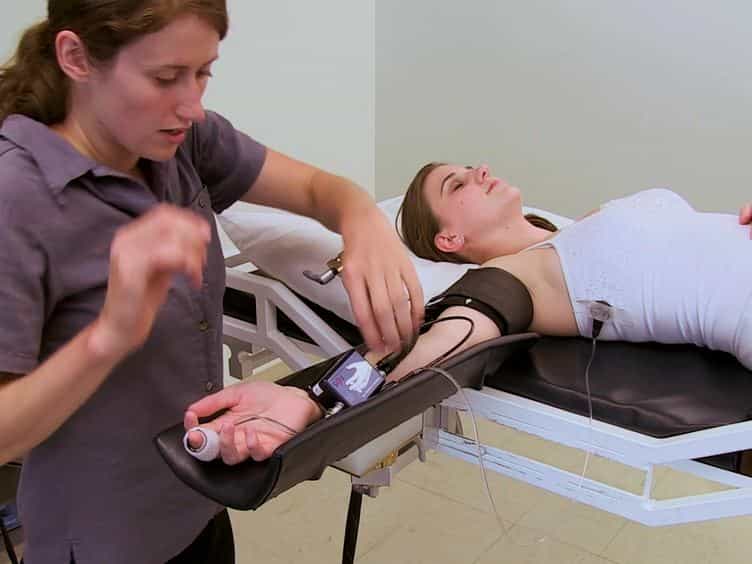
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Diagnosis and characteristics of syncope in older patients referred to geriatric departments
Andrea Ungar1, Chiara Mussi, Attilio Del Rosso
1Unit of Gerontology and Geriatric Medicine, Department of Critical Care Medicine and Surgery, University of Florence, and Division of Cardiology, Ospedale San Pietro Igneo, Florence, Italy. aungar@unifi.it

Objectives:
To test the applicability and safety of a standardized diagnostic algorithm in geriatric departments and to define the prevalence of different causes of syncope in older patients.
Design:
Multicenter cross-sectional observational study.
Setting:
In-hospital geriatric acute care departments and outpatient clinics.
Participants:
Two hundred forty-two patients (aged>or=65, mean+/-standard deviation=79+/-7, range 65-98) consecutively referred for evaluation of transient loss of consciousness to any of six clinical centers participating in the study. Of these, 11 had a syncope-like condition (5 transient ischemic attack; 6 seizures), and 231 had syncope (aged 65-74, n=71; aged>or=75, n=160).
Measurements:
Protocol designed to define etiology and clinical characteristics of syncope derived from European Society of Cardiology Guidelines on syncope.
Results:
No major complication occurred with use of the protocol. Neurally mediated was the more prevalent form of syncope in this population (66.6%). Cardiac causes accounted for 14.7% of all cases. The neuroreflex form of syncope (vasovagal, situational, and carotid sinus syndrome) was more common in younger than in older patients (62.3% vs 36.2%; P=.001), whereas orthostatic syncope was more frequent in the older than in the younger group (30.5% vs 4.2%; P<.001). In only 10.4% of cases, syncope remained of unexplained origin. After initial evaluation, a definite diagnosis was possible in 40.1% of the cases, and a suspected diagnosis was obtained in 57.9%. Syncope of suspected cardiac origin after initial evaluation was confirmed in 43.7% of cases, and neuromediated causes were confirmed in 83.5% of the cases.
Conclusion:
The protocol is applicable even beyond the age of 90 in geriatric departments. The standardized protocol is associated with a reduction in the frequency of unexplained syncope to about 10%.

Related Concept Videos
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:15
Drug Dosing: Geriatric Patients
 01:14
Decreased pulse rate
There are specific risk factors that can elevate the likelihood of developing bradycardia. Advanced age is a significant factor, with bradycardia...
 01:25
Dysrhythmias VII: Nursing Management of Dysrhythmias
 01:26
Heart Failure III: Clinical Manifestations