Related Experiment Video
Updated: Jul 19, 2026


Use of Hematopoietic Stem Cell Transplantation to Assess the Origin of Myelodysplastic Syndrome
Published on: October 3, 2018
Clinical manifestations of hematologic and oncologic disorders in patients with Down syndrome
Natalia Dixon1, Priya S Kishnani, Sherri Zimmerman
1Box 2916 DUMC, 222 Bell Building, Duke University Medical Center, Durham, NC 27710, USA. Natalia.Dixon@duke.edu

Abstract:
Hematologic abnormalities are common in individuals with Down syndrome (DS). Increased erythrocyte mean corpuscular volume (MCV) is frequently found among DS infants and remains elevated throughout life in two-thirds of patients, making interpretation of red cell indices for diagnosis of nutritional anemias or bone marrow failure disorders more challenging. Transient myeloproliferative disorder (TMD) associated with pancytopenia, hepatosplenomegaly, and circulating immature WBCs, is found almost exclusively in DS infants with an incidence of approximately 10%. In most cases, TMD regresses spontaneously within the first 3 months of life, but in some children, it can be life threatening or even fatal. Despite the high rate of spontaneous regression, TMD can be a preleukemic disorder in 20-30% of children with DS. The types of malignancy, response to therapy, and clinical outcome in children with DS are also unique. There is an increased risk of leukemia with an equal incidence of lymphoid and myeloid leukemia. Acute megakaryocytic leukemia (AMKL) subtype is the most common form of acute myeloid leukemia (AML) in this setting, and is uncommon in children without DS. Somatic mutations of the gene encoding the hematopoetic growth factor GATA1 have been shown to be specific for TMD and AMKL in children with DS. Myelodysplastic syndrome can precede AML. Children with DS and leukemia are more sensitive to some chemotherapeutic agents such as methotrexate than other children which requires careful monitoring for toxicity. Although the risk for leukemia is higher in individuals with DS, these patients have a lower risk of developing solid tumors, with the exception of germ cell tumors, and perhaps retinoblastoma and lymphoma.


Related Concept Videos
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:49
Meiosis I
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune system...
 02:57
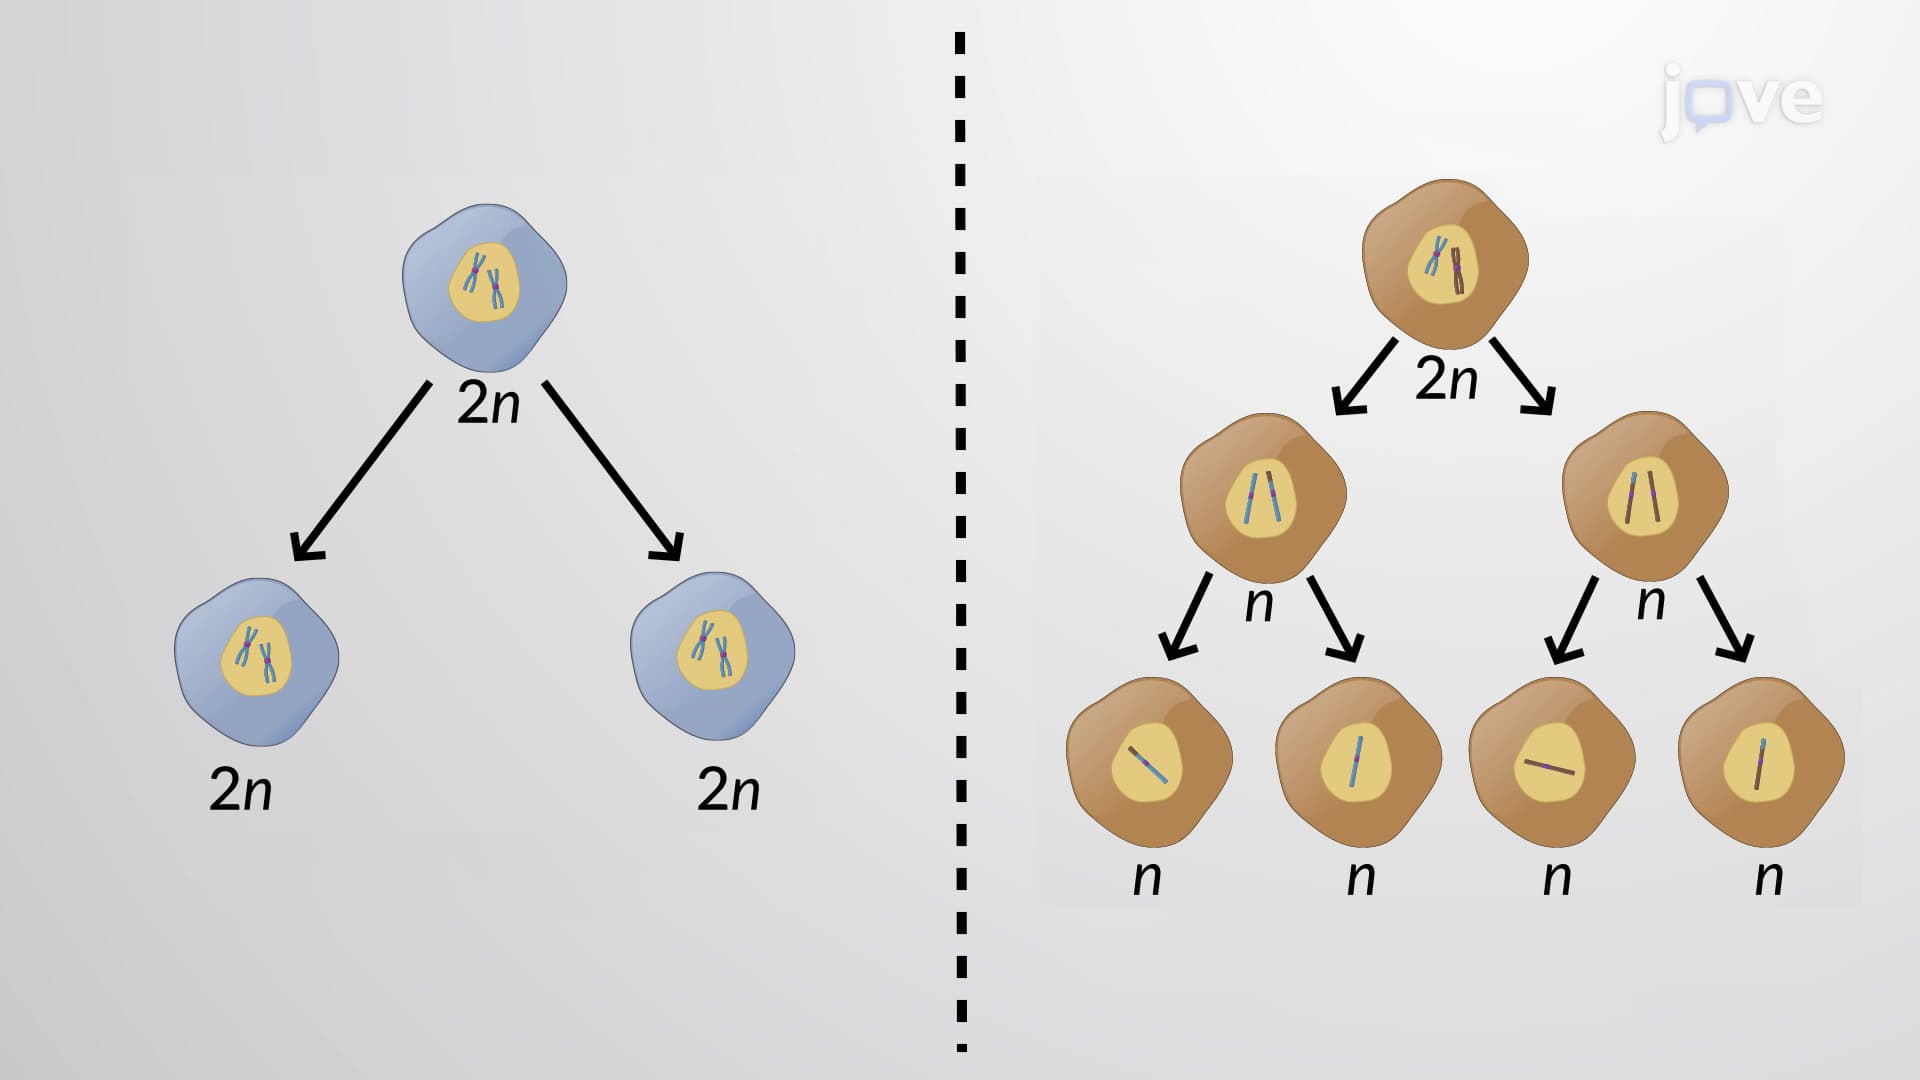
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...