Decrease in circulating glucose, insulin and leptin levels and improvement in insulin resistance at 1 and 3 months after gastric bypass
Related Experiment Video
Updated: Jul 19, 2026

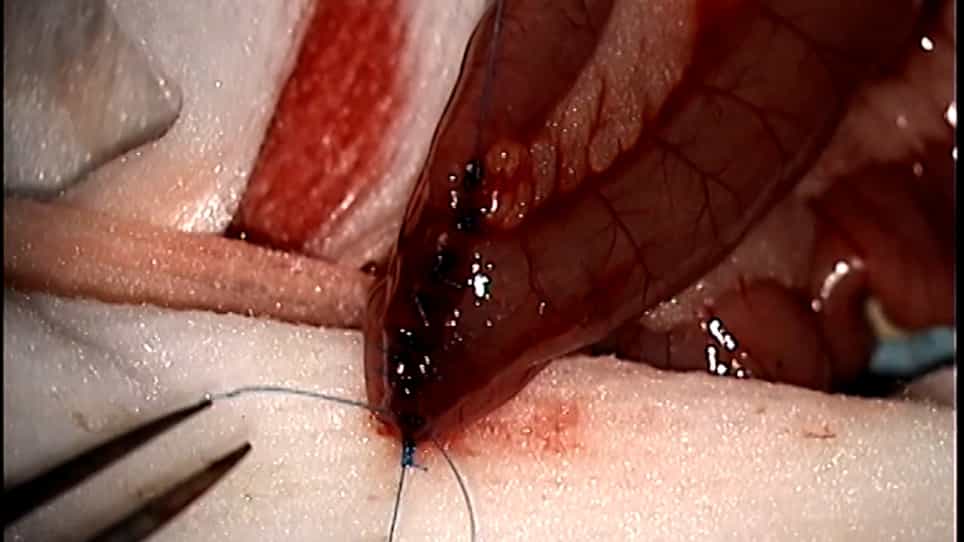
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Adriana Pelegrino Pinho Ramos1, Márcia Regina Azevedo de Abreu, Regina Célia Vendramini
1Laboratório de Análises Clínicas do Curso de Ciências Farmacêuticas da Universidade de Ribeirão Preto (UNAERP), Ribeirão Preto-SP, Brazil.

Background:
Hyperglycemia, insulin resistance and hyperleptinemia are some of the consequences of obesity. Gastric bypass for morbid obesity provides gastric restriction with decreased energy absorption. To confirm and extend previous reports in the literature, we evaluated the plasma glucose, serum insulin and leptin and insulin resistance of patients preoperatively and 1 and 3 months after Roux-en-Y gastric bypass (RYGBP).
Methods:
We determined body mass index (BMI), plasma glucose (glucose-oxidase method), serum leptin (immunoassay) and insulin (chemiluminescent immunometric assay), and insulin resistance index (IRI) by Homeostasis Model Assessment (HOMA) of 20 patients with morbid obesity both preoperatively and 1 and 3 months after RYGBP.
Results:
Patients showed a mean decrease in weight of 8 kg/month. Glycemia was above reference levels in 65% of the preoperative patients but dropped significantly 1 month postoperatively, serum insulin and leptin levels and the HOMA index also decreasing significantly in the same period. The percentage of patients with preoperative elevated serum insulin and leptin relative to reference levels decreased significantly following RYGBP. We also observed a weak but significant correlation between BMI and glucose, BMI and insulin, and leptin and insulin.
Conclusions:
The beneficial effects of bariatric surgery are already noticeable 1 month postoperatively, the reduction in insulin levels being more important for leptin reduction than decreased BMI. Leptin appeared to be subject to multifactorial control and showed a larger reduction than body weight.
Related Concept Videos
 01:24
Type II Diabetes II: Pathophysiology
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:19
Type I Diabetes III: Clinical Manifestations
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution