Related Experiment Video
Updated: Jul 19, 2026
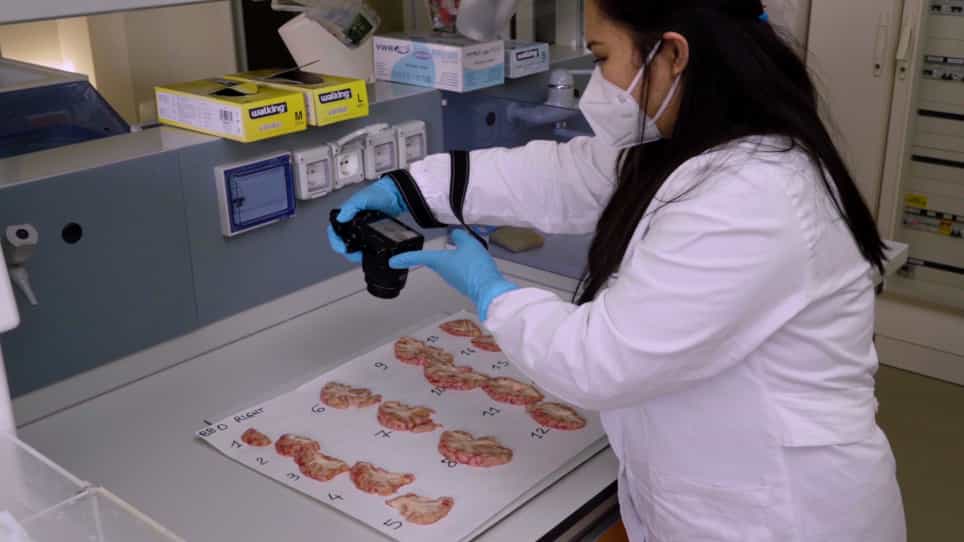
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Clinical practice with anti-dementia drugs: a consensus statement from British Association for Psychopharmacology
Alistair Burns1, John O'Brien,
1University of Manchester, Manchester, UK. alistair.burns@manchester.ac.uk

Abstract:
The British Association for Psychopharmacology (BAP) coordinated a meeting of experts to review the evidence on the drug treatment for dementia. The level of evidence (types) was rated using a standard system: Types 1a and 1b (evidence from meta-analysis of randomised controlled trials or at least one controlled trial respectively); types 2a and 2b (one well-designed study or one other type of quasi experimental study respectively); type 3 (non-experimental descriptive studies); and type 4 (expert opinion). There is type 1a evidence for cholinesterase inhibitors (donepezil, rivastigmine and galantamine) for mild to moderate Alzheimer's disease; memantine for moderate to severe Alzheimer's disease; and for the use of bright light therapy and aromatherapy. There is type 1a evidence of no effect of anti inflammatory drugs or statins. There is conflicting evidence regarding oestrogens, with type 2a evidence of a protective effect of oestrogens but 1b evidence of a harmful effect. Type 1a evidence for any effect of B12 and folate will be forthcoming when current trials report. There is type 1b evidence for gingko biloba in producing a modest benefit of cognitive function; cholinesterase inhibitors for the treatment of people with Lewy body disease (particularly neuropsychiatric symptoms); cholinesterase inhibitors and memantine in treatment cognitive impairment associated with vascular dementia; and the effect of metal collating agents (although these should not be prescribed until more data on safety and efficacy are available). There is type 1b evidence to show that neither cholinesterase inhibitors nor vitamin E reduce the risk of developing Alzheimer's disease in people with mild cognitive impairment; and there is no evidence that there is any intervention that can prevent the onset of dementia. There is type 1b evidence for the beneficial effects of adding memantine to cholinesterase inhibitors, and type 2b evidence of positive switching outcomes from one cholinesterase inhibitor to another. There is type 2a evidence for a positive effect of reminiscence therapy, and type 2a evidence that cognitive training does not work. There is type 3 evidence to support the use of psychological interventions in dementia. There is type 2 evidence that a clinical diagnosis of dementia can be made accurately and that brain imaging increases that accuracy. Although the consensus statement dealt largely with medication, the role of dementia care in secondary services (geriatric medicine and old age psychiatry) and primary care, along with health economics, was discussed. There is ample evidence that there are effective treatments for people with dementia, and Alzheimer's disease in particular. Patients, their carers, and clinicians deserve to be optimistic in a field which often attracts therapeutic nihilism.
More Related Videos

Related Concept Videos
 01:22
Alzheimer's Disease: Treatment
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:26
Psychosis: Goals of Pharmacotherapy
 01:28
Drug Therapy
Antianxiety Medications
 01:15
Drug Dosing: Geriatric Patients
 01:28
Psychosis and Antipsychotic Drugs: Overview