Related Experiment Video
Updated: Jul 17, 2026
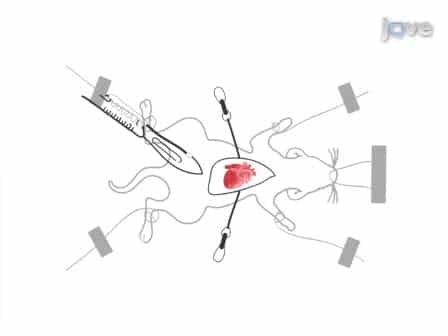
Use of a Hanging Weight System for Coronary Artery Occlusion in Mice
Published on: April 19, 2011
Myocardial infarct-sparing effect of adenosine A2A receptor activation is due to its action on CD4+ T lymphocytes
Zequan Yang1, Yuan-Ji Day, Marie-Claire Toufektsian
1Department of Biomedical Engineering, University of Virginia Health System, Box 800759, Charlottesville, VA 22903, USA. zy6b@virginia.edu

Background:
We previously used adenosine A2A receptor (A2AR) knockout (KO) mice and bone marrow transplantation to show that the infarct-sparing effect of A2AR activation at reperfusion is primarily due to effects on bone marrow-derived cells. In this study we show that CD4+ but not CD8+ T lymphocytes contribute to myocardial ischemia/reperfusion injury.
Method And Results:
After a 45-minute occlusion of the left anterior descending coronary artery and reperfusion, T cells accumulate in the infarct zone within 2 minutes. Addition of 10 microg/kg of the A2AR agonist ATL146e 5 minutes before reperfusion produces a significant reduction in T-cell accumulation and a significant reduction in infarct size (percentage of risk area) measured at 24 hours. In Rag1 KO mice lacking mature lymphocytes, infarct size is significantly smaller than in C57BL/6 mice. Infarct size in Rag1 KO mice is increased to the level of B6 mice by adoptive transfer of 50 million CD4+ T lymphocytes derived from C57BL/6 or A2AR KO but not interferon-gamma KO mice. ATL146e completely blocked the increase in infarct size in Rag1 KO mice reconstituted with B6 but not A2AR KO CD4+ T cells. The number of neutrophils in the reperfused heart at 24 hours after infarction correlated well with the number of lymphocytes and infarct size.
Conclusions:
These results strongly suggest that the infarct-sparing effect of A2AR activation is primarily due to inhibition of CD4+ T-cell accumulation and activation in the reperfused heart.
More Related Videos
 11:29
HPLC-based Assay to Monitor Extracellular Nucleotide/Nucleoside Metabolism in Human Chronic Lymphocytic Leukemia Cells
Published on: July 20, 2016
 05:41
Left Anterior Descending Coronary Artery Ligation for Ischemia-Reperfusion Research: Model Improvement via Technical Modifications and Quality Control
Published on: December 16, 2022
Related Concept Videos
 01:31
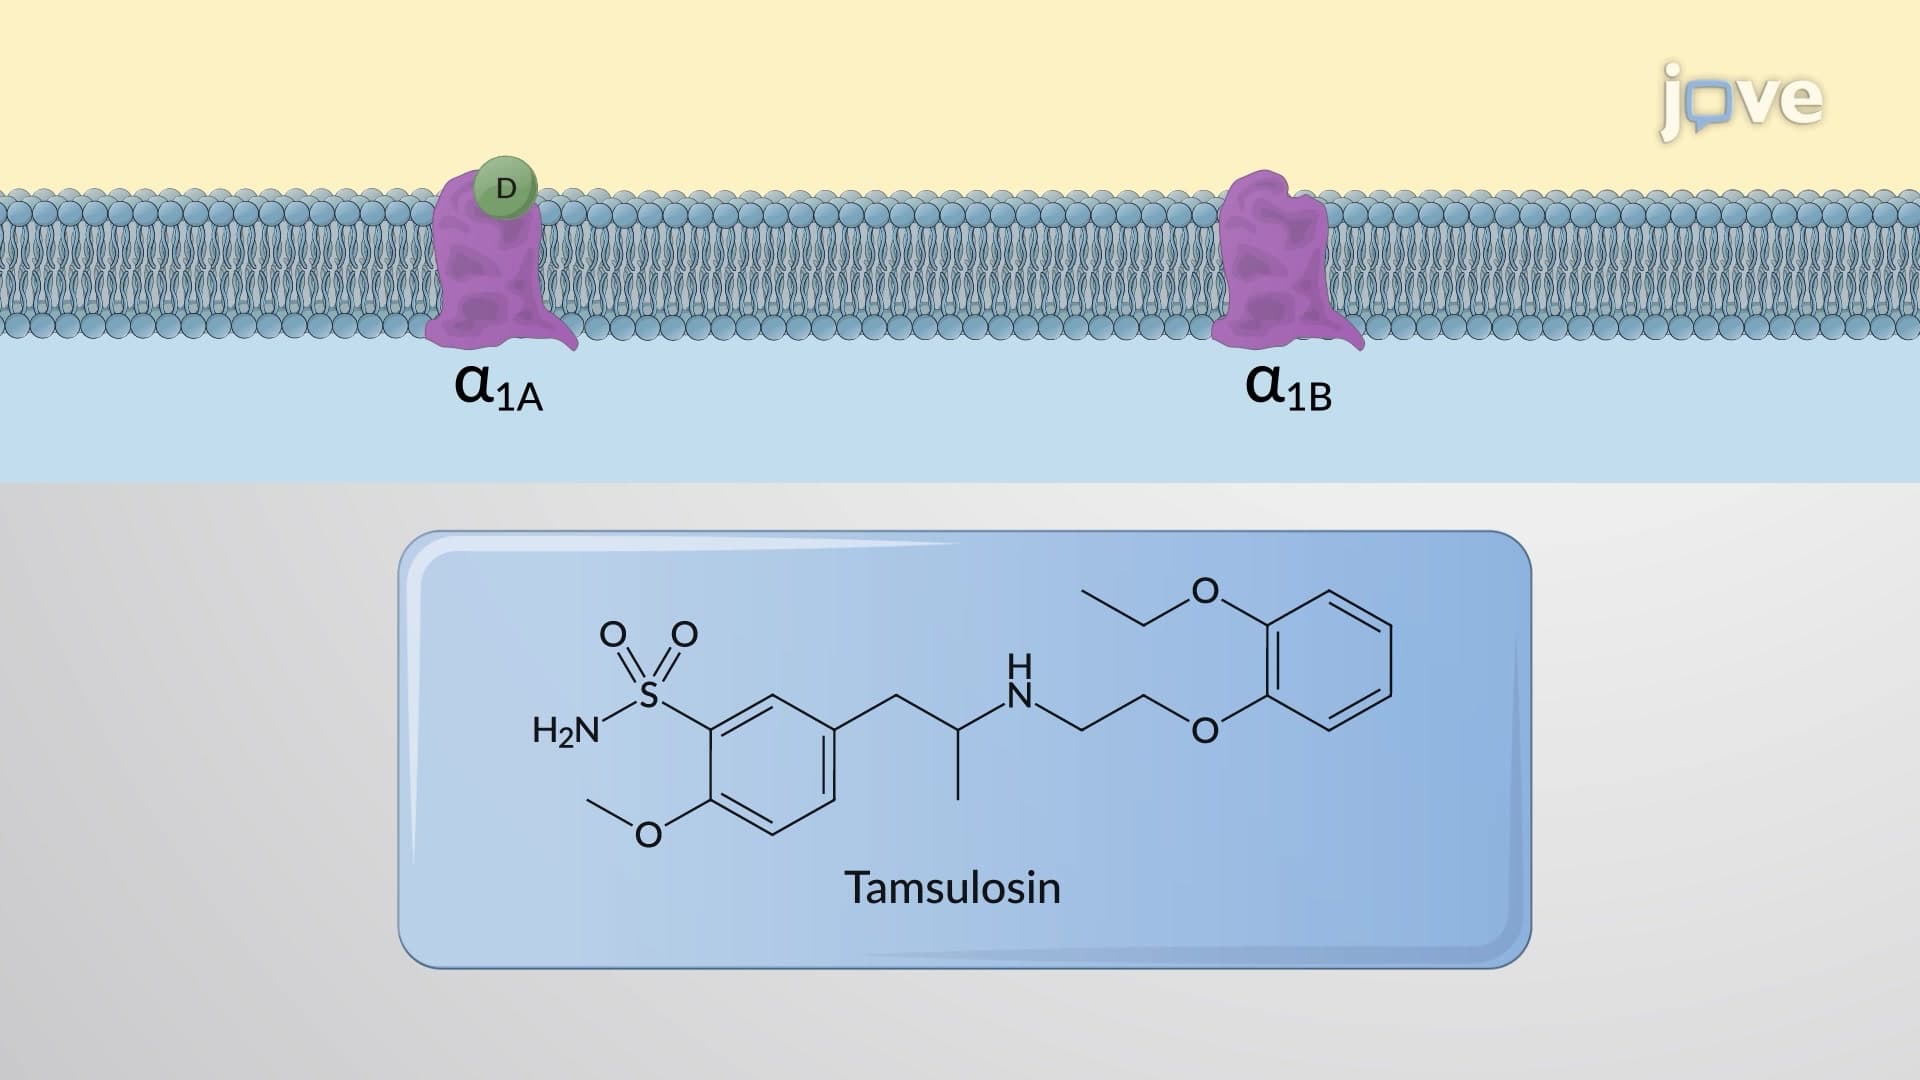
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:26
Heart Failure Drugs: Inotropic Agents