Related Experiment Video
Updated: Jul 19, 2026
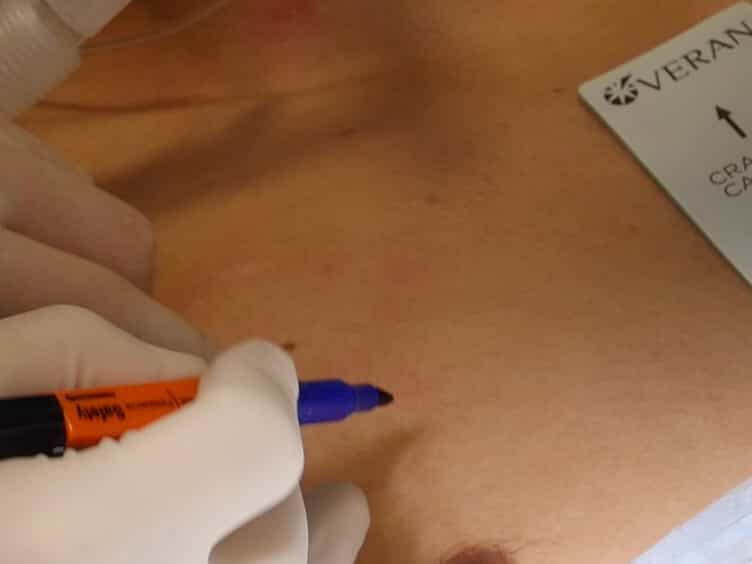
Use of Electromagnetic Navigational Transthoracic Needle Aspiration (E-TTNA) for Sampling of Lung Nodules
Published on: May 23, 2015
Satellite pulmonary nodule in the same lobe (T4N0) should not be staged as IIIB non-small cell lung cancer
Ayesha S Bryant1, Sara J Pereira, Daniel L Miller
1Department of Epidemiology, University of Alabama at Birmingham School of Public Health, Birmingham, Alabama 35294, USA.

Background:
Treatment of non-small cell lung cancer depends on stage. Patients with T4 lesions represent a heterogeneous group.
Methods:
A case-control study of patients with pathologically proven, node-negative T4 lesions (T4 N0 M0) was conducted. Patients with T4 disease were stratified as T4 from a satellite nodule (T4-satellite) or T4 from local invasion (T4-invasion). T4-satellite patients were matched 1:4 for sex and histology with resected control patients with stage IA, IB, and IIA non-small cell lung cancer and matched 1:3 with stage II non-small cell lung cancer. Survival and the maximal standardized uptake value on F-18 fluorodeoxyglucose-positron emission tomography scans were compared.
Results:
There were 337 patients, 26 patients with T4-satellite lesions, 25 with T4-invasion lesions, and 286 controls (104 patients with T1 N0 M0, 104 with T2 N0 M0, and 78 with T1 N1 M0 or T2 N1 M0 lesions). The two T4 groups were similar for age, race, sex, and neoadjuvant therapy rates. The 5-year survival was 80% for the T1 N0 M0 patients, 68% for T2 N0 M0, 57% for T4-satellite N0 M0, 45% for T1 N1 M0 or T2 N1 M0, and 30% for the T4-invasion N0 M0 patients (p = 0.016). Multivariate analysis showed that only the type of T4 impacted survival (p = 0.011). The median maximal standardized uptake values of the cancers were 4.2 for T1 N0 M0, 4.8 for T4-satellite, 5.4 for T2 N0 M0, 7.8 for T1 N1 M0 or T2 N1 M0, and 8.8 for the T4-invasion patients.
Conclusions:
Larger studies are needed; however, patients with T4-satellite non-small cell lung cancer who undergo complete resection have survival and maximal standardized uptake values similar to patients with stage IB and stage IIA lesions. Their survival is significantly better than those with T4-invasion. Patients with T4-satellite N0 M0 lesions should not be classified as stage IIIB and should not be grouped with patients with T4-invasion, and resection should be considered.
Related Concept Videos
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: