Related Experiment Video
Updated: Jul 19, 2026


Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Management of fever without source in young children presenting to an emergency room
Martial M Massin1, Jessica Montesanti, Philippe Lepage
1Department of Paediatrics, Queen Fabiola Children's University Hospital, Free University of Brussels, Brussels, Belgium. martial.massin@chrcitadelle.be

Insights
Management of fever without source in young children differs from guidelines, but this approach aids early diagnosis of serious infections without adverse outcomes.
Area of Science:
- Pediatrics
- Emergency Medicine
- Infectious Disease
Background:
- Fever without source in young children presents a management challenge with ongoing debate.
- Current practice guidelines offer recommendations for managing this condition.
Purpose of the Study:
- To analyze the management strategies for fever without source in a pediatric emergency room.
- To compare these strategies against established clinical practice guidelines.
Main Methods:
- A retrospective analysis of 2176 children aged 1-36 months presenting with fever (>= 38.5°C).
- Exclusion of patients with chronic illness, recent antibiotic use, focal infection, or viral illness, leaving 376 patients for analysis.
- Evaluation of diagnostic test ordering (blood count, chest X-ray, urinalysis, blood culture) and empirical antibiotic use.
Main Results:
- Acute febrile illness was the most common diagnosis (n=228), with bacterial infections in 120 and viral in 28.
- Physicians generally followed guidelines for ordering tests but rarely obtained blood cultures, even with antibiotics.
- Empirical antibiotic use and test ordering in low-risk patients deviated from guidelines, yet facilitated early detection of serious infections (e.g., bacteremia, pneumonia, UTI).
Conclusions:
- Significant discrepancies exist between current clinical practice and established guidelines for managing fever without source in young children.
- The observed practice patterns, while differing from guidelines, did not negatively impact patient outcomes and potentially improved early diagnosis of severe infections.
Background:
The management of fever without source in young children is controversial.
Aim:
To analyse the management approach in our paediatric emergency room, and to correlate it to existing practice guidelines.
Methods:
We indexed 2176 consecutive patients, aged 1 to 36 mo, seen in our emergency department because of fever > or = 38.5 degrees C. Patients with chronic illness, recent antibiotic use, focal bacterial infection or typical viral illness were excluded, and the management approach of the remaining 376 patients was analysed.
Results:
The most common final diagnosis was acute febrile illness (n=228), whereas bacterial and viral infections were demonstrated in 120 and 28 patients, respectively. Most of the time, our residents correctly ordered complete blood count, chest radiograph and urinalysis in children for whom those investigations are recommended. A blood culture was rarely obtained, even in patients under empirical antibiotherapy. Residents often ordered chest radiograph and urinalysis in low-risk patients, and conflicted with guidelines when considering the prescription of empirical antibiotherapy. Their management allowed the early diagnosis and treatment of two pneumococcal bacteraemias, one meningococcal bacteraemia, seven urinary tract infections and 11 pneumonias, which would have been initially missed by strict adherence to the guidelines.
Conclusion:
Significant differences exist in the management of the young febrile child between our practice patterns and guidelines, without influence on patient outcome.
Related Concept Videos
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:25
Increased Body Temperature
 01:25
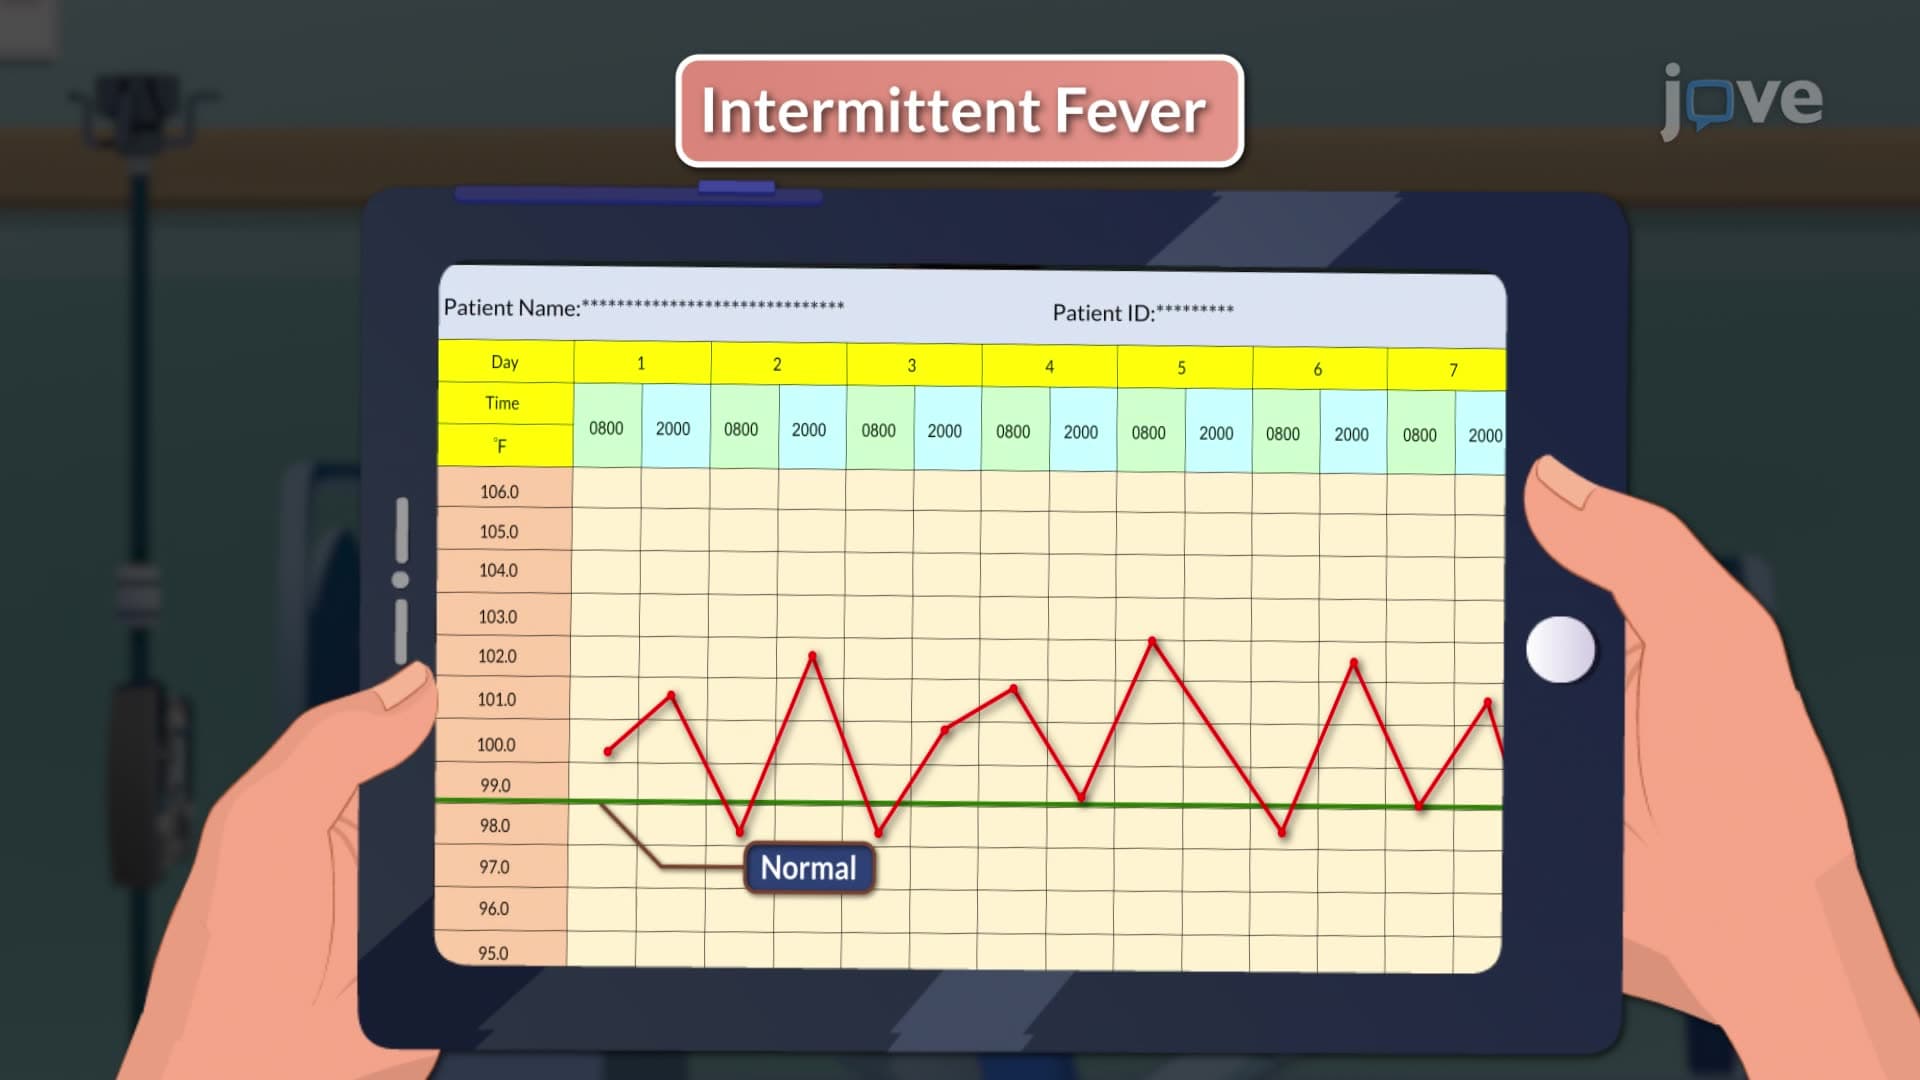
Types of Fever
Here are the different types of fever:
 01:26
Patterns of Fever
 01:26
Tonsillitis II: Management
 01:29
Decreased Body Temperature