Related Experiment Video
Updated: Jul 19, 2026
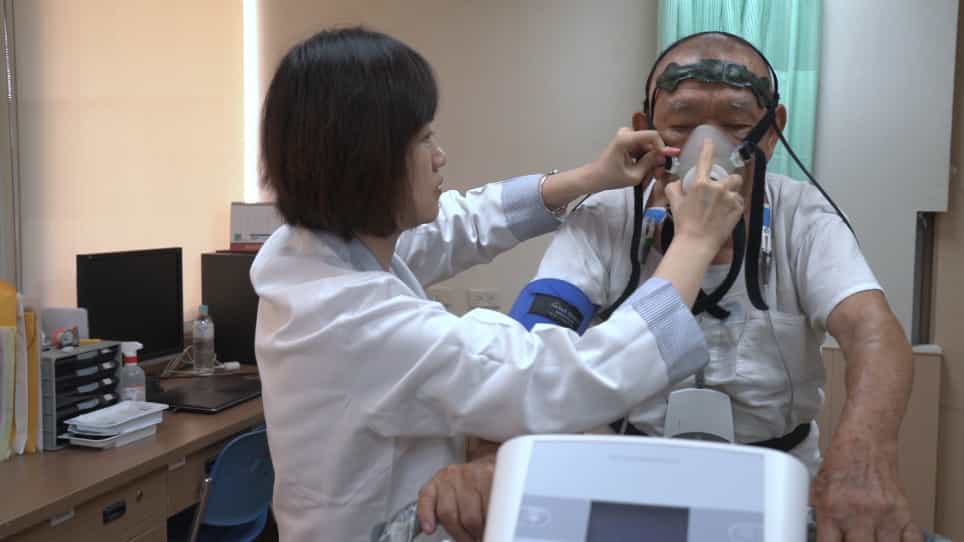
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Prognostic value of the VE/VCO2 slope calculated from different time intervals in patients with suspected heart
Lee Ingle1, Kevin Goode, Sean Carroll
1Department of Academic Cardiology, University of Hull, Castle Hill Hospital, Cottingham, Kingston-upon-Hull, United Kingdom. L.Ingle@hull.ac.uk <L.Ingle@hull.ac.uk>

Background:
Maximal exercises testing, whether involving cycling- or walking-based protocols, are often not well tolerated in patients with chronic heart failure (CHF). The peak oxygen consumption and the slope of the relation between ventilation (V(E)) and carbon dioxide production (V(CO(2))) are independent predictors of outcome and help risk stratification. The prognostic usefulness of submaximal exercise testing is not clear. The aim of the present study was to assess the prognostic value of the V(E)/V(CO(2)) slope when derived from data acquired from submaximal exercise.
Methods:
394 patients referred with breathlessness and suspected heart failure (74% male) (mean+/-S.D.) age 60+/-12 years; BMI 27+/-5 performed a CPET to determine peak V(O(2)) and the V(E)/V(CO(2)) slope. The V(E)/V(CO(2)) slope was calculated using least squares regression from data acquired from the first 25% of exercise (mean V(E)/V(CO(2)) slope+/-SD; 30.6+/-5.7), 50% (29.6+/-6.9), below the ventilatory compensation point (sub-VCP) (29.9+/-6.8), and all data points (full slope) (32.1+/-7.8). For each measure, patients were divided into quartiles and Kaplan-Meier curves were constructed to determine probability of death after 24 months. The prognostic value of the different classifications was assessed using the chi(2) statistic from the Mantel-Cox log-rank test.
Results:
During a mean follow-up period of 41+/-19 months, 48 patients died. For the V(E)/V(CO(2)) slope, the log-rank statistic was greatest for the full slope (chi(2)=53.7; P=0.0001), followed by the sub-VCP (chi(2)=45.5; P=0.0001), 50% (chi(2)=41.9; P=0.0001), and 25% (chi(2)= 26.0; P=0.01). The pair-wise log-rank statistic between the fourth and third quartiles was also greatest using the full slope (chi(2)=25.4; P=0.001) followed in order by the sub-VCP (chi(2)=20.1; P=0.001), 50% (chi(2)=19.7; P=0.001), and 25% (chi(2)=14.2; P=0.05). Using the stratified slope measurements entered into a Cox regression analysis using a forward LR stepwise elimination procedure; only the full slope remained significant (P=0.0001).
Conclusions:
The V(E)/V(CO(2)) slope should be calculated from all data points to optimise prognostic sensitivity. Data acquired from the first 50% of exercise and below the VCP provide adequate prognostic surrogates in patients who may not be able to perform maximal exercise testing (i.e. in patients with a respiratory exchange ratio<1.10).
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: