Related Experiment Video
Updated: Jul 19, 2026

Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Ritonavir-fluticasone interaction causing Cushing syndrome in HIV-infected children and adolescents
Renata Arrington-Sanders1, Nancy Hutton, George K Siberry
1Division of General Pediatrics & Adolescent Medicine, The Johns Hopkins Medical Institutions, Baltimore, MD 20724, USA. rarring3@jhmi.edu

Background:
Ritonavir, a potent inhibitor of CYP3A4 enzyme, can lead to high systemic concentrations of fluticasone when these 2 drugs are coadministered. Exogenous Cushing syndrome (CS) in HIV-infected patients receiving ritonavir and fluticasone has been reported frequently in adults but not in children. Three patients, all receiving ritonavir-fluticasone, developed weight gain and altered fat distribution concerning for either lipodystrophy or CS.
Methods:
Three patients were initially identified by their clinicians as having weight gain and altered fat distribution concerning for either lipodystrophy or CS. All 3 patients were receiving fluticasone and ritonavir, leading to concern about a potential medication interaction. After suspecting exogenous CS, all patient medication lists were reviewed to identify all children prescribed ritonavir-fluticasone. Blood adrenocorticotropic hormone (ACTH) and cortisol were obtained during routine clinic visits. Medication history, laboratory data and physical examination findings were abstracted from medical records.
Results:
Seventeen (9%) of 189 patients in this pediatric HIV clinic had been prescribed ritonavir-fluticasone. Of 7 patients still taking ritonavir-fluticasone, CS features were present in 4 (57%) patients, including the 3 patients initially suspected of CS or lipodystrophy. Five (71%) patients, including all 4 with CS features, had low serum concentrations: median cortisol <0.2 microg/dL (normal, <0.2 microg/dL). Three of these 5 had ACTH measured, all of which were low: median ACTH 3.0 pmol/L (range, 2.2-<5.0 pmol/L). One patient taking ritonavir-fluticasone had suppressed cortisol but no CS features. The 2 patients with normal serum cortisol and ACTH values had persistent HIV viremia and were suspected of medication nonadherence. Clinical and laboratory abnormalities generally normalized in affected patients within 3 months after discontinuation of fluticasone alone (2) and ritonavir-fluticasone (3).
Conclusions:
Pediatric HIV physicians frequently prescribe fluticasone and ritonavir together. The combination can cause CS and adrenal suppression in children, potentially leading to misdiagnosis of lipodystrophy syndrome and to increased risk of adrenal crisis during acute illness. Alternatives to fluticasone should be used for treating children receiving ritonavir.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:26
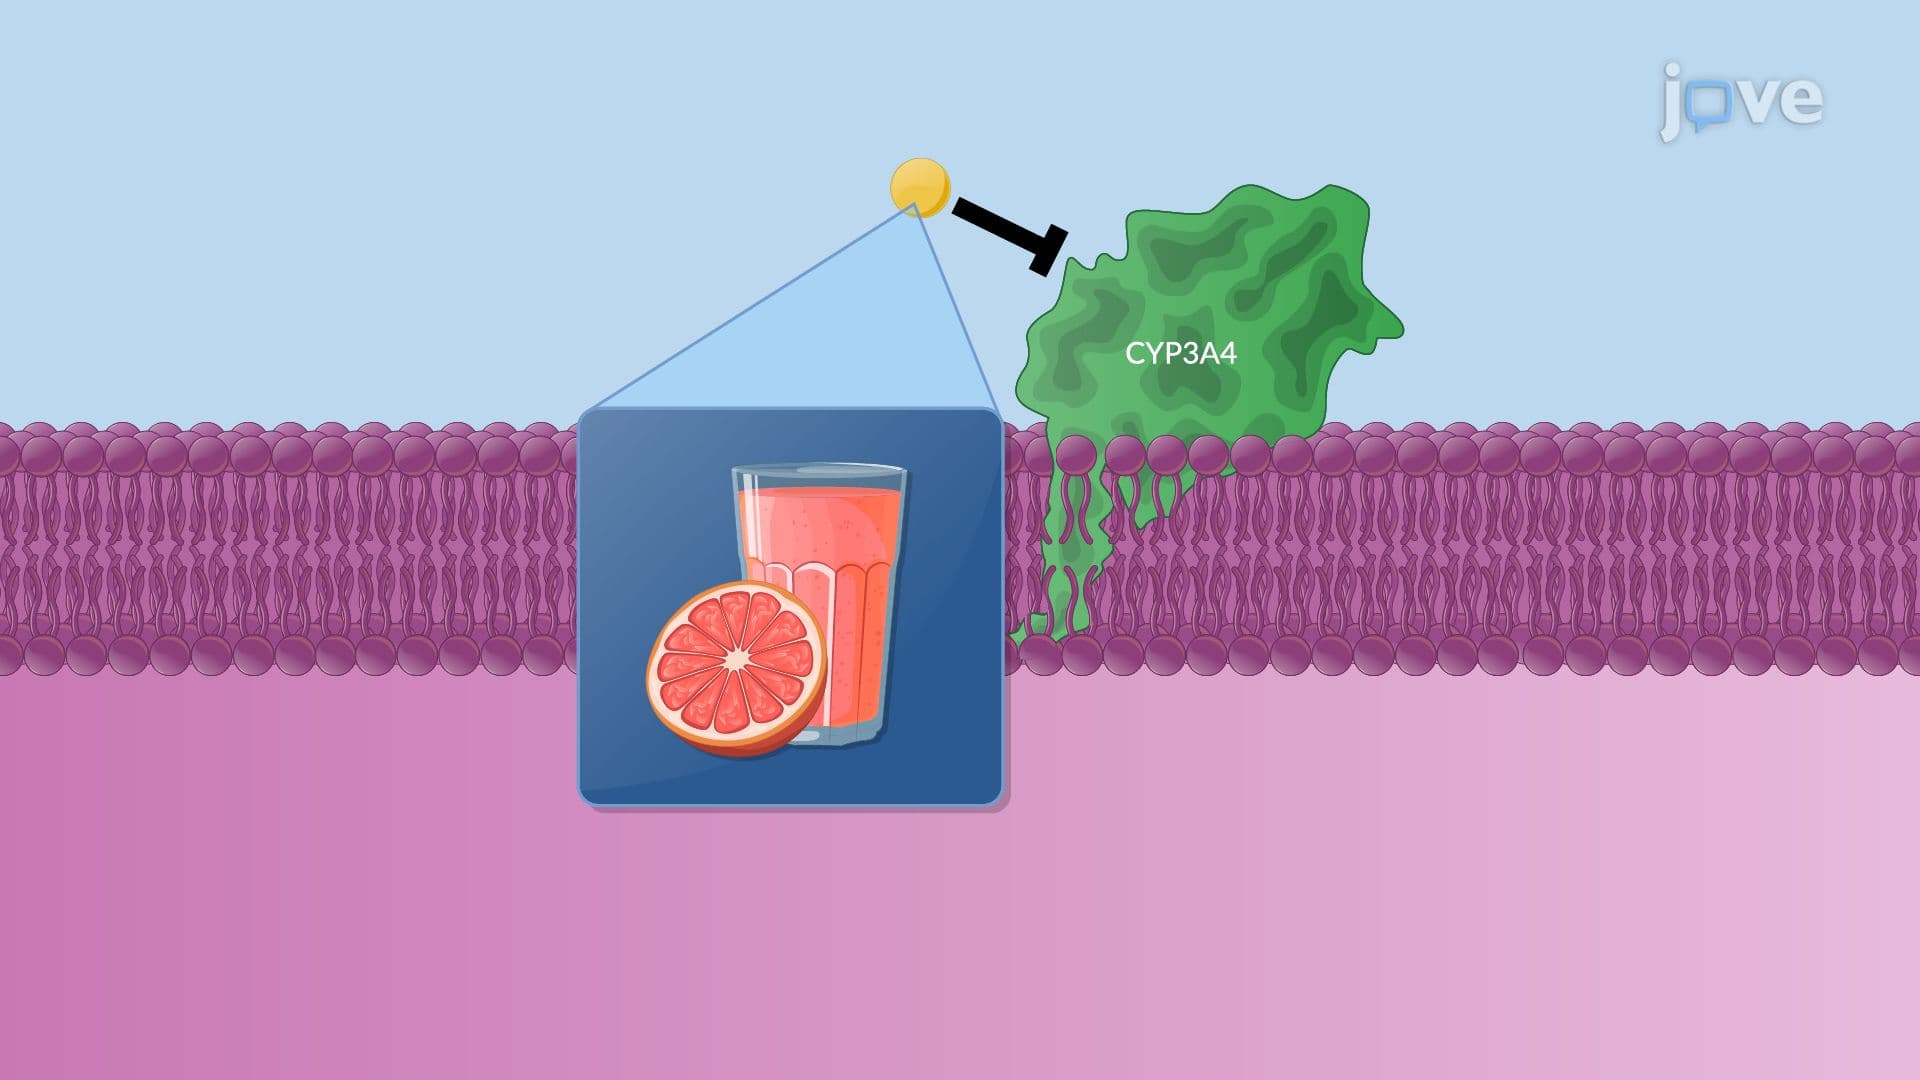
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:29
Respiratory Syncytial Virus Disease
 01:27
Cryptococcal Meningitis
 01:10
Retrovirus Life Cycles
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...