Related Experiment Video
Updated: Jul 19, 2026

Comprehensive Endovascular and Open Surgical Management of Cerebral Arteriovenous Malformations
Published on: October 20, 2017
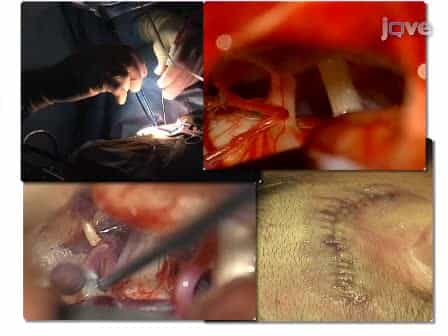
Transcranial embolization of a transverse-sigmoid sinus dural arteriovenous fistula carried out through a
1Department of Radiology, Taipei Veterans General Hospital and School of Medicine, National Yang Ming University, Taipei, Taiwan, ROC. cbluo@vghtpe.gov.tw

Insights
A rare case of dural arteriovenous fistula (DAVF) led to intraventricular hemorrhage and cerebellar infarction. Transcranial sinus puncture via decompressive craniectomy successfully treated the fistula when other methods failed.
Area of Science:
- Neurosurgery
- Interventional Neuroradiology
- Vascular Neurology
Background:
- Dural arteriovenous fistulas (DAVFs) are abnormal connections between dura mater arteries and venous sinuses.
- Transverse-sigmoid sinus DAVFs can present with severe intracranial hemorrhage.
- Standard treatment involves endovascular embolization or surgical ligation.
Observation:
- A patient presented with intraventricular hemorrhage secondary to a transverse-sigmoid sinus DAVF.
- Cerebellar infarction occurred post-transarterial embolization.
- Decompressive craniectomy was performed to manage increased intracranial pressure and mass effect.
Findings:
- A novel transcranial approach through the decompressive craniectomy bone window enabled direct puncture of the transverse sinus.
- Successful coil occlusion of the DAVF was achieved via this transcranial route.
- This technique provided an alternative treatment pathway for complex DAVFs.
Implications:
- Decompressive craniectomy can create a unique surgical corridor for treating challenging DAVFs.
- This case highlights the potential of minimally invasive transcranial techniques in neurovascular interventions.
- It expands treatment options for DAVFs refractory to conventional transarterial or transvenous approaches.
Abstract:
We report a case of dural arteriovenous fistula (DAVF) of the transverse-sigmoid sinus presenting with intraventricular hemorrhage. Cerebellar infarction developed after transarterial embolization, and decompressive craniectomy was performed to relieve the mass effect. Through the bone window of the decompressive craniectomy, transcranial puncture of the transverse sinus and coil occlusion of the fistula were successfully performed. Decompressive craniectomy may provide an opportunity to occlude DAVFs which cannot be occluded by the transarterial or transvenous approach.