Related Experiment Video
Updated: May 11, 2026


Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Obesity does not increase effects of synthetic ghrelin on human gastric motor functions
Filippo Cremonini1, Michael Camilleri, Maria Vazquez Roque
1Clinical Enteric Neuroscience Translational & Epidemiological Research (C.E.N.T.E.R.) Group, Mayo Clinic College of Medicine, Rochester, Minnesota, USA.

Background & Aims:
Ghrelin is secreted by the stomach and stimulates food intake. Obese individuals have lower fasting plasma ghrelin levels but increased appetite, suggesting greater responses to endogenous ghrelin in obesity. The aim of this study was to compare effects of exogenous ghrelin (at a dose that stimulates growth hormone [GH] release in the physiologic range) versus placebo on gastric emptying, gastric volume, and postprandial symptoms and determine whether body mass (ranging from normal weight to obesity) influences responses to ghrelin.
Methods:
After intravenous bolus synthetic human ghrelin (0.33 mug/kg) or saline, we measured plasma GH, gastric volume, and gastric emptying by combined (99m)Tc-single-photon emission computed tomography and scintigraphy ((111)In egg meal, 300 kcal) and postprandial symptoms using visual analogue scales.
Results:
In 25 obese subjects (5 men and 20 women; body mass index [BMI], 36 +/- 4 kg/m(2)) and 13 female normal-weight (BMI, 22 +/- 2 kg/m(2)) subjects of similar ages, ghrelin increased GH levels (15.0 +/- 2.4 ng/mL) at 40 minutes postinjection and tended to decrease fasting gastric volumes compared with placebo (P = .059). There were no effects of BMI on treatment response and no differences between ghrelin and saline on postprandial (P = .09) or change in (postprandial minus fasting) gastric volumes, gastric emptying, or aggregate postprandial symptoms. Effects of ghrelin did not differ between obese and normal-weight participants.
Conclusions:
At doses that stimulate physiologic GH plasma levels, synthetic ghrelin tended to decrease fasting gastric volumes without altering postprandial volumes or gastric emptying in a predominantly female cohort. The data are not consistent with the hypothesis that higher body mass is associated with increased gastric responsiveness to ghrelin.


Related Concept Videos
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists
 01:16
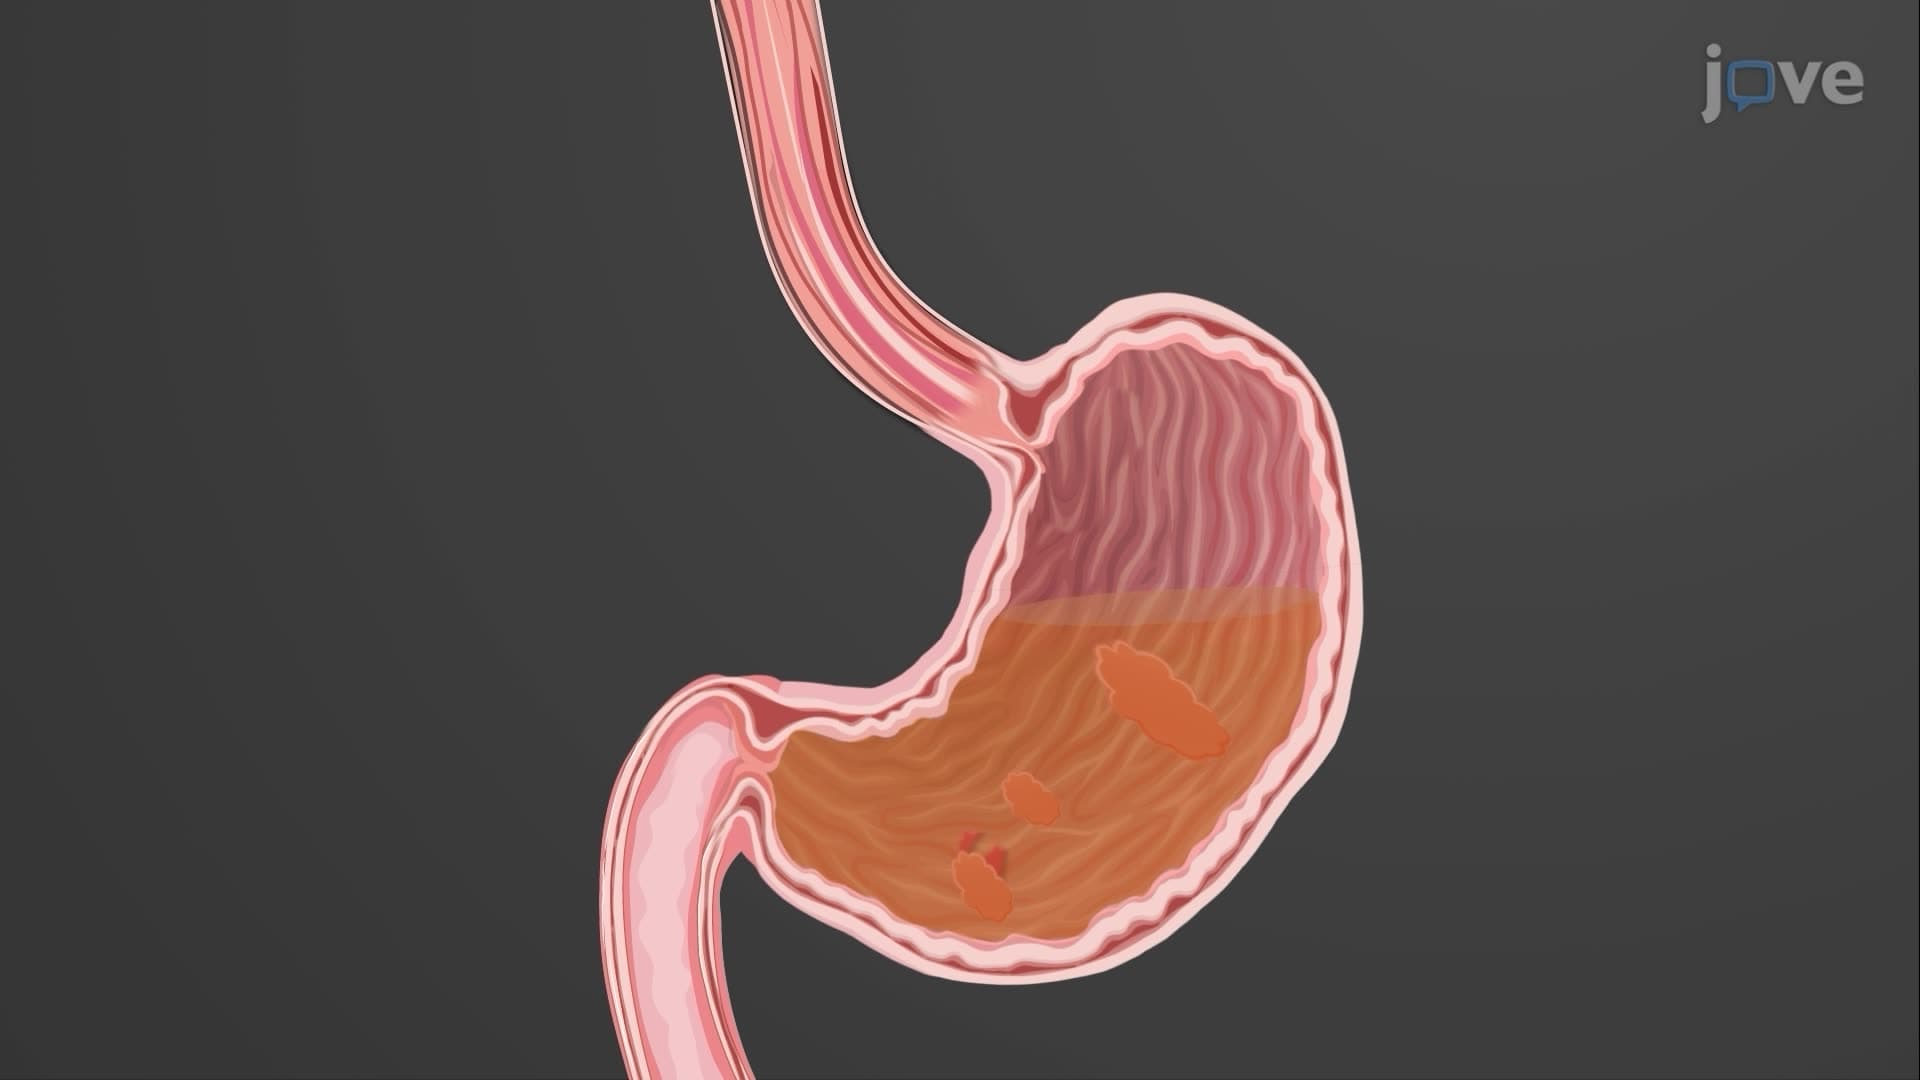
Gastric Emptying
 01:30
Regulation of Food Intake
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...