Related Experiment Video
Updated: Jul 18, 2026
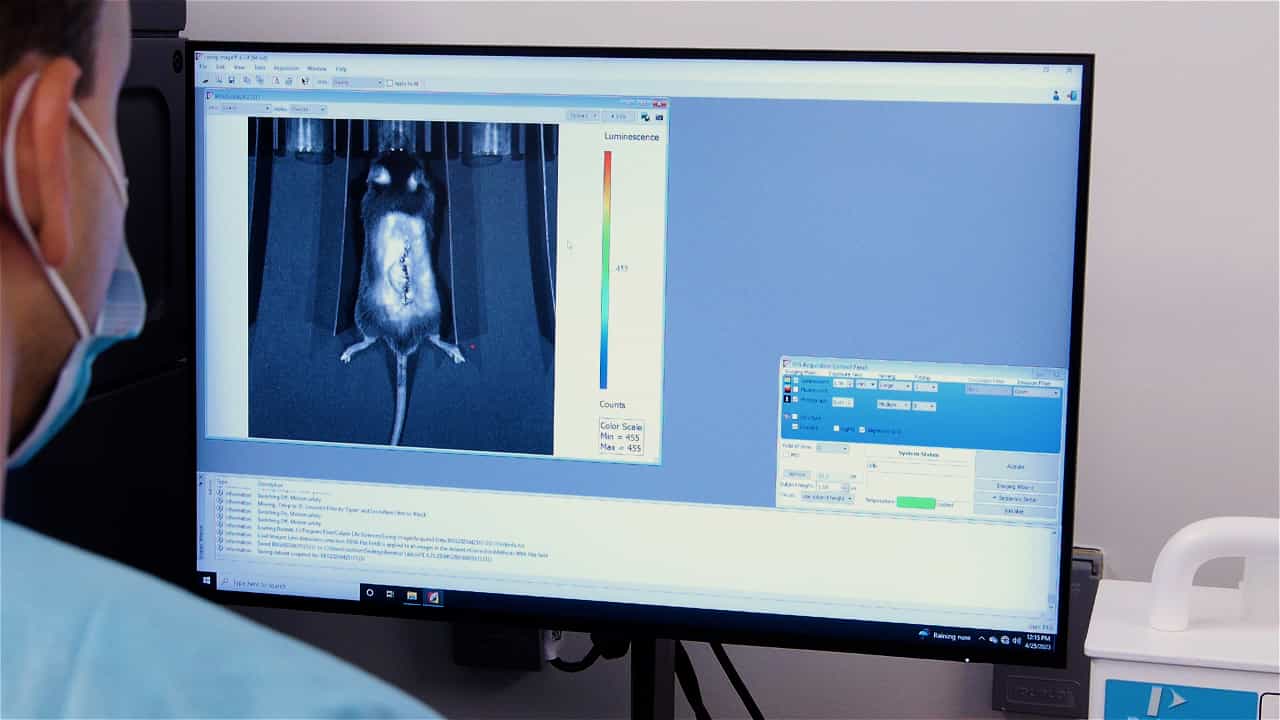

In Vivo Mouse Model of Spinal Implant Infection
Published on: June 23, 2020
Procedure-specific surgical site infection rates and postdischarge surveillance in Scotland
J Reilly1, G Allardice, J Bruce
1HAI and Infection Control, Health Protection Scotland, Glasgow, UK. jacqui.reilly@hps.scot.nhs.uk

Objective:
To investigate the impact of postdischarge surveillance (PDS) on surgical-site infection (SSI) rates for selected surgical procedures in acute care hospitals in Scotland.
Design:
Prospective surveillance of SSI after selected surgical procedures.
Setting:
The Scottish Surveillance of Healthcare Associated Infection Programme (SSHAIP), which is based on the methodology of the Centers for Disease Control and Prevention (CDC) National Nosocomial Infections Surveillance system (NNIS). Thirty-two of 46 acute care hospitals throughout Scotland contributed data to SSHAIP for this study.
Methods:
Data were from 21,710 operations that took place between April 1, 2002, and June 30, 2004; nine categories of surgical procedures were analyzed. CDC NNIS system definitions and methods were used for SSI PDS. PDS is a voluntary component of the mandatory SSI surveillance program in Scotland. PDS was categorized as none, passive, active without direct observation, and active with direct observation.
Results:
From our study information, PDS data were available for 12,885 operations (59%). A total of 2,793 procedures (13%) were associated with passive PDS and 10,092 (46%) with active PDS. The SSI rate among the 8,825 operations with no PDS was 2.61% (95% confidence interval [CI], 2.3%-3.0%), which was significantly lower than the SSI rate found among the 12,885 operations for which PDS was performed (6.34% [95% CI, 5.9%-6.8%]). For breast surgery, cesarean section, hip replacement, and abdominal hysterectomy, the rate of SSI when PDS was performed was significantly higher than that when PDS was not performed (P<.01 for each procedure). No differences in SSI rates were found for surgery to repair fractured neck of the femur or for knee replacement. SSI rates were examined according to procedure type, performance of PDS, and NNIS risk index; rates of SSI increased with NNIS risk index within procedure group and PDS group. Logistic regression analyses confirmed that procedure type, performance of PDS, and NNIS risk index were all statistically independent predictors of report of an SSI (P<.05).
Conclusions:
This Scottish national data set incorporates a substantial amount of PDS data. We recommend a procedure-specific approach to PDS, with direct observation of patients after breast surgery, cesarean section, and hysterectomy, for which the length of stay is typically short. Readmission surveillance may be adequate to detect most SSIs after orthopedic surgery or vascular surgery, for which the length of stay is typically longer.
Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:29
Endocarditis IV: Nursing Management
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin create...
 01:18
Endocarditis III: Medical Management
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...