Leukocyte-endothelial cell interactions in chronic vasospasm after subarachnoid hemorrhage
Related Experiment Video
Updated: Jul 18, 2026
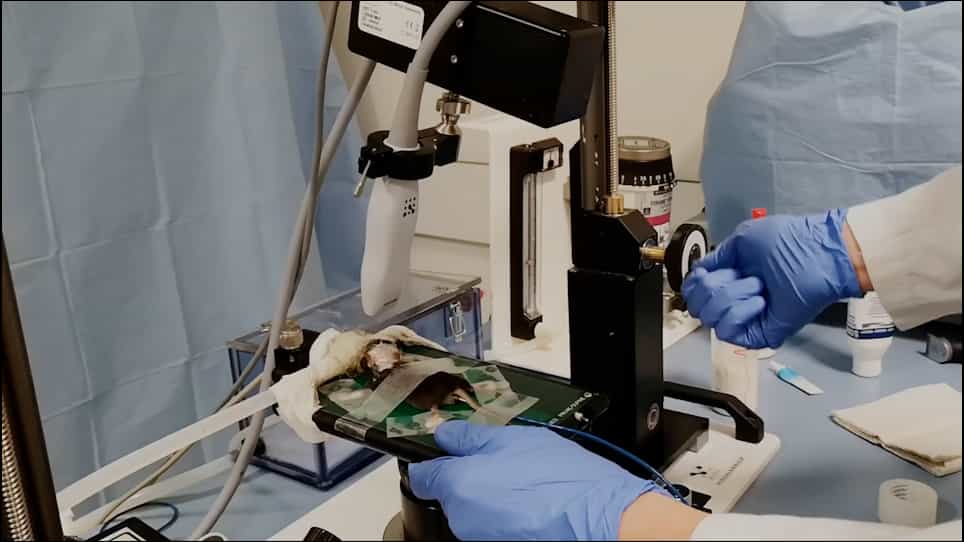
Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
Gary L Gallia1, Rafael J Tamargo
1Department of Neurosurgery, The Johns Hopkins University School of Medicine, Baltimore, MD, USA.

Leukocyte-endothelial cell interactions appear to be the root cause of chronic vasospasm after aneurysmal subarachnoid hemorrhage (aSAH). Early clinical observations and indirect experimental evidence suggested an association between inflammation and chronic vasospasm. Early clinical observations in patients with post-hemorrhagic vasospasm included pyrexia, leukocytosis and the presence of circulating immune complexes. Inflammatory infiltrates and increased levels of immunoglobulins and complement fractions within spastic cerebral arteries also provided early evidence for an inflammatory mechanism underlying chronic vasospasm. Early indirect experimental evidence included the ability to reproduce chronic vasospasm with the introduction of inflammatory agents into the subarachnoid space and the inhibition of vasospasm with anti-inflammatory agents. Currently, however, there is an increasing body of direct molecular evidence that demonstrates the pivotal role of leukocyte-endothelial cell interactions in the development of chronic vasospasm. Cell adhesion molecules such as intercellular adhesion molecule-1 (ICAM-1), lymphocyte function-associated antigen-1 (LFA-1), macrophage antigen-1 (Mac-1) and endothelial (E)-selectin mediate interactions between circulating leukocytes and cerebral endothelium. Following aSAH, ICAM-1 is up-regulated in cerebral endothelial cells and along with other cell adhesion molecules, can be detected in the serum and cerebrospinal fluid (CSF) of patients with post-hemorrhagic vasospasm. Monoclonal antibody blocking experiments have demonstrated that the prevention of leukocyte extravasation into the subarachnoid space prevents chronic vasospasm. Similarly, drugs like ibuprofen, which prevent ICAM-1 up-regulation and transendothelial cell migration of leukocytes, prevent vasospasm. In this review, we highlight early observations that suggested an association between inflammation and post-hemorrhagic vasospasm, detail the role of leukocyte-endothelial cell interactions in the development of chronic vasospasm and discuss therapeutic implications of an inflammatory etiology of post-hemorrhagic cerebral vasospasm.
Leukocyte-endothelial cell interactions appear to be the root cause of chronic vasospasm after aneurysmal subarachnoid hemorrhage (aSAH). Early clinical observations and indirect experimental evidence suggested an association between inflammation and chronic vasospasm. Early clinical observations in patients with post-hemorrhagic vasospasm included pyrexia, leukocytosis and the presence of circulating immune complexes. Inflammatory infiltrates and increased levels of immunoglobulins and complement fractions within spastic cerebral arteries also provided early evidence for an inflammatory mechanism underlying chronic vasospasm. Early indirect experimental evidence included the ability to reproduce chronic vasospasm with the introduction of inflammatory agents into the subarachnoid space and the inhibition of vasospasm with anti-inflammatory agents. Currently, however, there is an increasing body of direct molecular evidence that demonstrates the pivotal role of leukocyte-endothelial cell interactions in the development of chronic vasospasm. Cell adhesion molecules such as intercellular adhesion molecule-1 (ICAM-1), lymphocyte function-associated antigen-1 (LFA-1), macrophage antigen-1 (Mac-1) and endothelial (E)-selectin mediate interactions between circulating leukocytes and cerebral endothelium. Following aSAH, ICAM-1 is up-regulated in cerebral endothelial cells and along with other cell adhesion molecules, can be detected in the serum and cerebrospinal fluid (CSF) of patients with post-hemorrhagic vasospasm. Monoclonal antibody blocking experiments have demonstrated that the prevention of leukocyte extravasation into the subarachnoid space prevents chronic vasospasm. Similarly, drugs like ibuprofen, which prevent ICAM-1 up-regulation and transendothelial cell migration of leukocytes, prevent vasospasm. In this review, we highlight early observations that suggested an association between inflammation and post-hemorrhagic vasospasm, detail the role of leukocyte-endothelial cell interactions in the development of chronic vasospasm and discuss therapeutic implications of an inflammatory etiology of post-hemorrhagic cerebral vasospasm.

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:16
Vascular Spasm
 01:22
Cerebral Edema ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:26
Bacterial Meningitis II: Pathophysiology