Related Experiment Video
Updated: Jul 18, 2026

A Semi-Automated and Reproducible Biological-Based Method to Quantify Calcium Deposition In Vitro
Published on: June 2, 2022
Elevations in serum and urinary calcium with parathyroid hormone (1-84) with and without alendronate for osteoporosis
Diana M Antoniucci1, Deborah E Sellmeyer, John P Bilezikian
1Division of Endocrinology, Department of Medicine, University of California, San Francisco, California 94107, USA.

Context:
The effect of PTH therapy on serum and urinary calcium levels and the risk of hypercalcemia or hypercalciuria has not been formally evaluated.
Objective:
The objective was to examine changes in serum and urinary calcium associated with PTH(1-84) therapy in the PaTH trial and the extent to which a defined algorithm resolved the elevated values.
Design, Setting, Participants, And Intervention:
A total of 178 postmenopausal women were randomized to PTH(1-84) either alone or in combination with alendronate during the first year of the PaTH study.
Main Outcome Measure(S):
The main outcome measures were fasting serum calcium at baseline and 1, 3, and 12 months and 24-h urinary calcium at baseline and 3 months.
Results:
In 14% of participants, serum calcium more than 10.5 mg/dl (>2.6 mmol/liter) developed. Following the defined algorithm, 58% of elevated measurements were normal on repeat testing; 38% required discontinuation of calcium and vitamin D supplementation, and one necessitated a decrease in PTH injection frequency to normalize serum calcium. One participant developed transient hypercalcemia between study visits and required hospitalization; the episode resolved with iv hydration and PTH discontinuation. Baseline characteristics associated with the development of hypercalcemia were serum calcium [relative hazards = 1.9 per 0.5 mg/dl (0.12 mmol/liter); 95% confidence interval = 1.1-3.2] and serum 1,25-dihydroxyvitamin D [relative hazard = 1.9 per 10 pg/ml (26 pmol/liter); 95% confidence interval = 1.2-3.1]. Fifteen women (8%) developed hypercalciuria [urinary calcium > 400 mg (100 mmol)/24 h or calcium/creatinine ratio > 0.4]; 80% of cases resolved after discontinuing calcium and vitamin D, 13% without intervention, and one after PTH injection frequency was decreased. Higher baseline urinary calcium excretion was associated with development of hypercalciuria [relative hazard = 1.5 per 50 mg/d (12.5 mmol/d); 95% confidence interval = 1.2-4.0]. Proportions of patients with elevated serum and urinary calcium were similar on single and combination therapy.
Conclusions:
The frequency of episodic hypercalcemia or hypercalciuria in the PaTH trial was 21%. Episodes were generally mild, and nearly all cases resolved spontaneously or with discontinuation of calcium and vitamin D. The algorithms used to address hypercalcemia and hypercalciuria in the PaTH trial proved effective in safely resolving clinical episodes of increased urinary or serum calcium and might therefore be helpful to clinicians caring for patients on PTH.

Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 01:40
Bone Remodeling
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:27
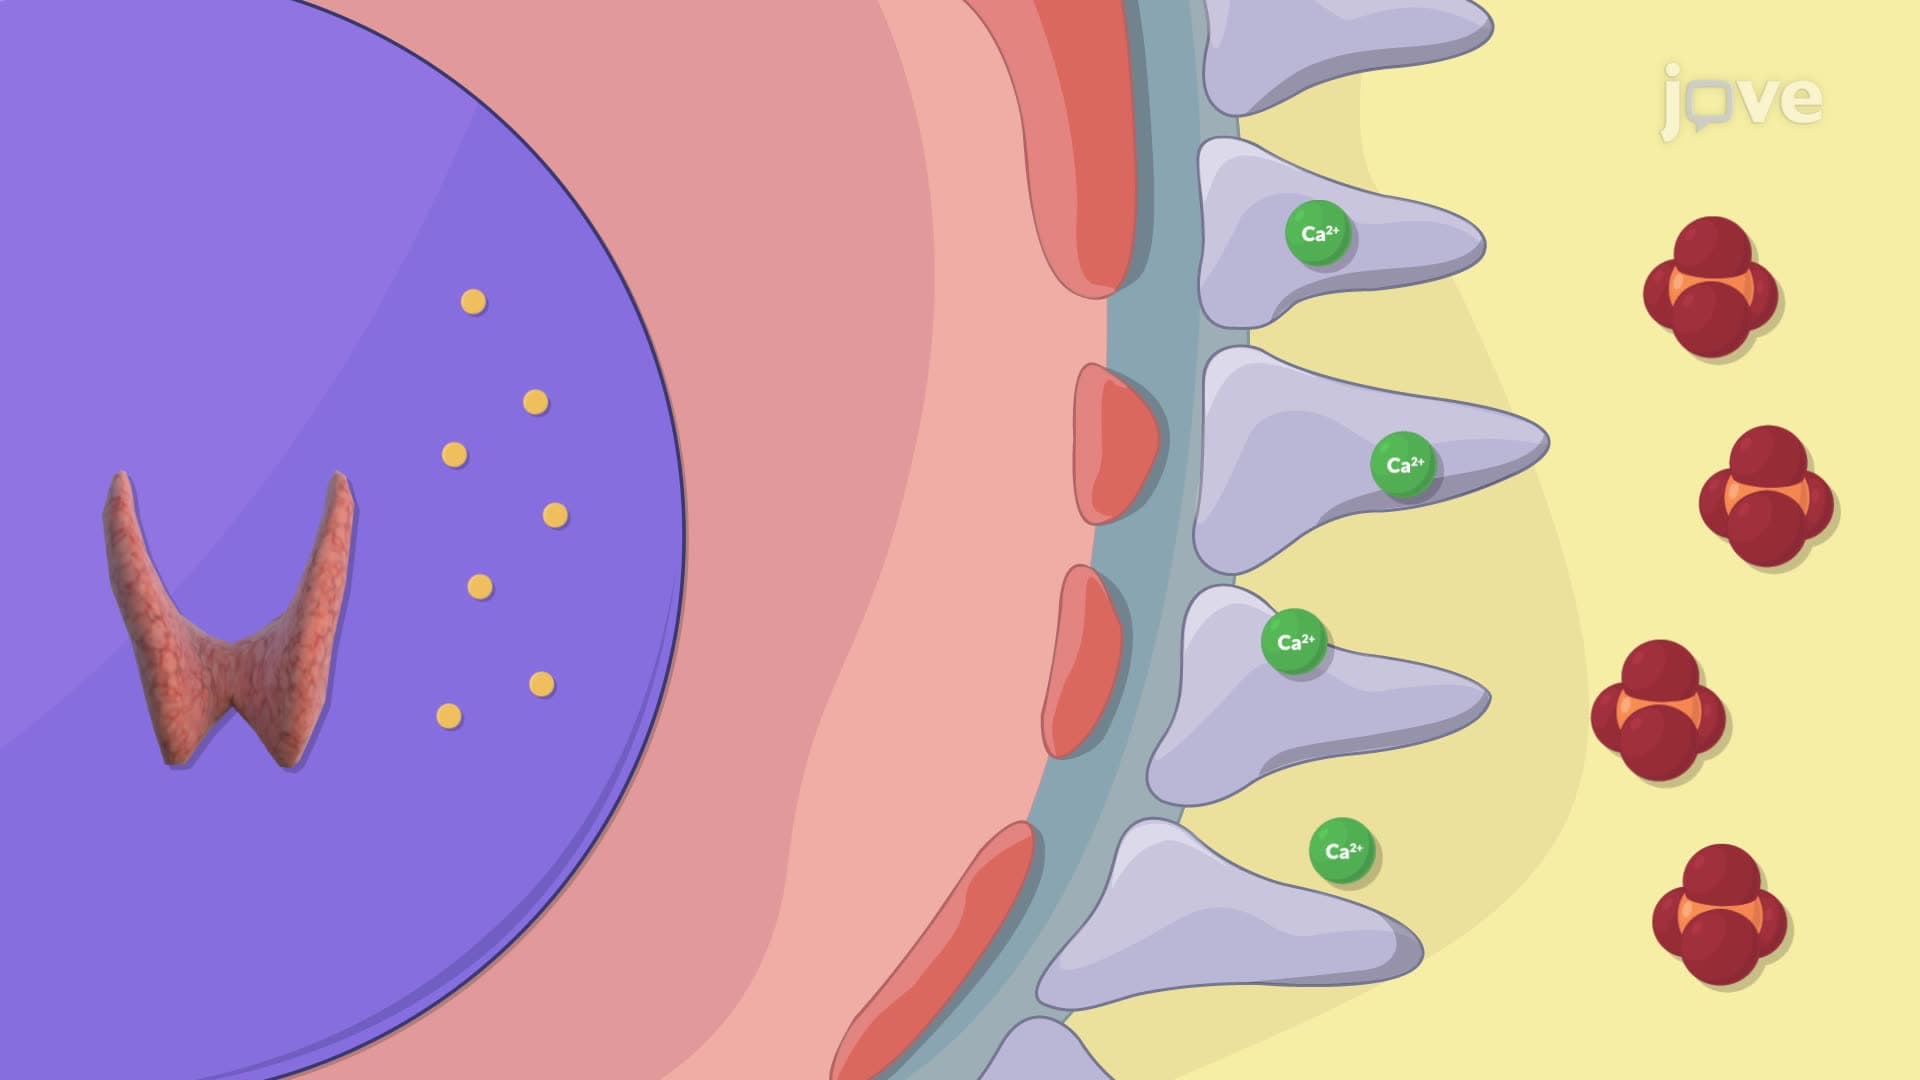
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily regulated...
 00:51
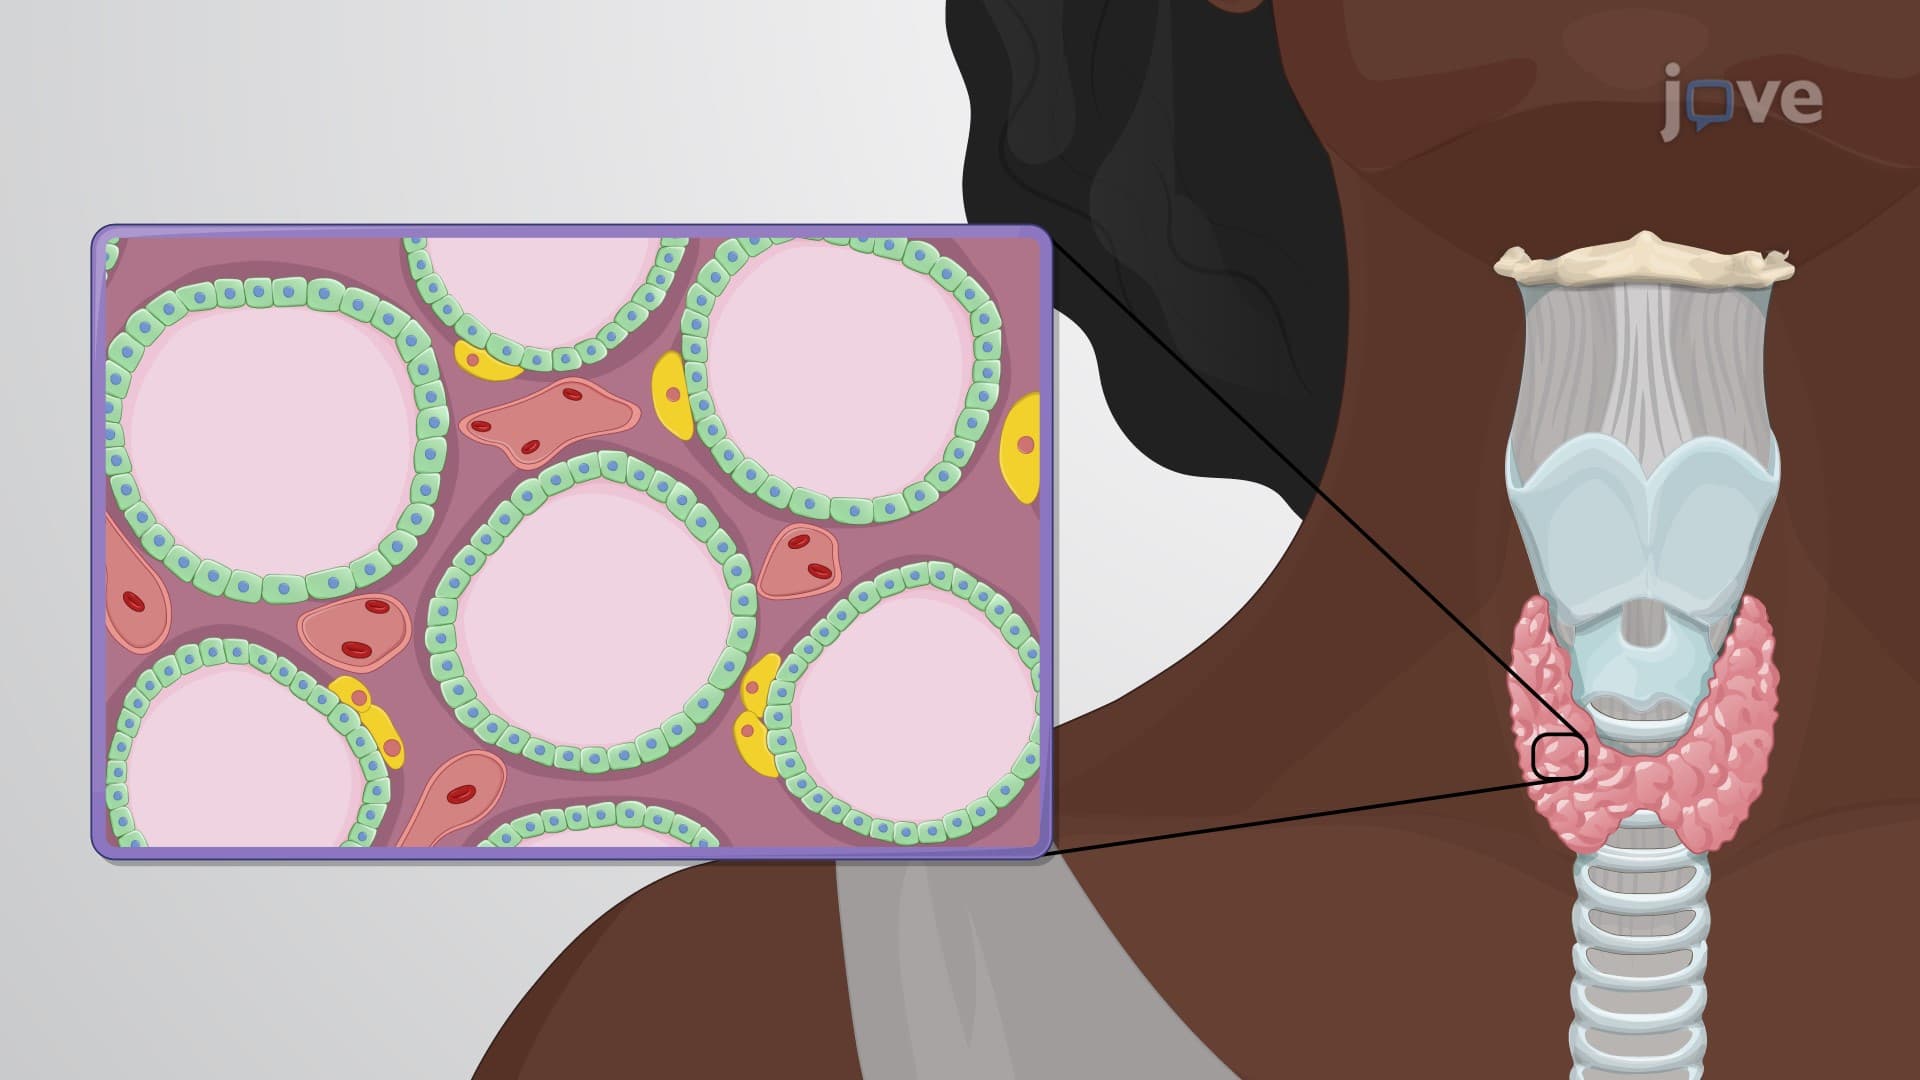
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...