Related Experiment Video
Updated: Jul 18, 2026

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Effects of an increase in time vs. frequency on cardiovascular parameters in chronic hemodialysis patients
T Weinreich1, T De los Ríos, A Gauly
1Nephrologisches Zentrum Villingen-Schwenningen, Germany. weinreich@dialyse-schwenningen.de

Insights
Intensified dialysis treatment, including long nightly intermittent (LNHD) and short daily (DHD) sessions, improved cardiac health and anemia control in hemodialysis patients. These advanced dialysis schedules offered better management of cardiovascular risk factors compared to standard hemodialysis (SHD).
Area of Science:
- Nephrology
- Cardiology
- Internal Medicine
Background:
- Cardiovascular mortality remains high in patients undergoing conventional chronic hemodialysis.
- Standard hemodialysis often inadequately controls key risk factors like hypertension and left ventricular hypertrophy.
- Intensified dialysis schedules show potential for improved patient outcomes.
Purpose of the Study:
- To compare the effects of long nightly intermittent hemodialysis (LNHD) and short daily hemodialysis (DHD) against standard hemodialysis (SHD).
- To evaluate the impact of intensified dialysis on cardiovascular parameters, phosphate, and anemia control.
- To assess changes in blood pressure, left ventricular mass index (LVMI), and fractional shortening (FS) over one year.
Main Methods:
- Observational study comparing LNHD (3x 7.5-8h), DHD (6x 2.5-3h), and SHD (3x 4-5h) in hemodialysis patients.
- Inclusion criteria: patients aged 18-80 with uncontrolled hypertension, LVH, or intradialytic hypotension.
- Primary endpoint: 24-h ambulatory blood pressure; secondary endpoints: LVMI, FS, calcium/phosphate control, anemia control.
Main Results:
- No significant change in 24-h blood pressure across all groups after one year.
- Predialysis systolic blood pressure decreased in LNHD and DHD groups, but increased in SHD.
- LVMI decreased in all groups, with greater reduction in DHD; FS improved in LNHD and DHD, worsening in SHD.
- Phosphate control and Ca x P product improved in DHD and LNHD; hemoglobin increased in intensified groups, falling in SHD.
Conclusions:
- Intensified dialysis (LNHD, DHD) positively impacts left ventricular mass and fractional shortening with reduced antihypertensive medication needs.
- Short daily hemodialysis (DHD) demonstrated more pronounced favorable effects on cardiovascular parameters.
- Standard hemodialysis (SHD) required increased antihypertensive medication and led to worsening fractional shortening.
Unlabelled:
Cardiovascular mortality is still high and many risk factors are inadequately controlled in patients on conventional chronic hemodialysis. Recent studies on intensified treatment schedules by either increasing length or frequency of dialysis sessions have shown promising results with better control of blood pressure, reduction of left ventricular hypertrophy and easier control of calcium/phosphate metabolism.
Aim:
The present observational study compared the effect of different forms of "intensified dialysis treatment" i.e. either long nightly intermittent (LNHD, 3 x 7.5 - 8 h) or short daily dialysis sessions (DHD, 6 x 2.5 - 3 h) on cardiovascular parameters, phosphate and anemia control in comparison to standard treatment schedules (SHD, 3 x 4 - 5 h).
Methods:
All patients stable on hemodialysis between 18 and 80 years of age and with either uncontrolled hypertension and/or left ventricular hypertrophy and/or frequent intradialytic hypotension, were asked to participate in intensified dialysis therapy by either LNHD or DHD. Patients not willing to change their dialysis regime were asked to participate as control group (SHD). Primary end point was 24-h ambulatory blood pressure, secondary end points were predialysis blood pressure, left ventricular mass index (LVMI) and fractional shortening (FS), control of calcium, phosphate and anemia. Patients were followed up for 1 year.
Results:
17 patients opted for LNHD, 8 for DHD, 19 patients served as control group. After 1 year of treatment 24-h blood pressure was unchanged in all groups. Predialysis systolic blood pressure decreased in LNHD and DHD, but increased in SHD. Mean LVMI decreased in all treatment groups (DHD -20.1 +/- 24.0%, SHD -13.6 +/- 33.4%, LNHD -6.1 +/- 32.2%). The mean number of antihypertensive tablets/day was reduced in DHD by 3.3 tablet units, in LNHD by 1.2 tablet units, but increased in SHD patients. FS improved in patients on LNHD and DHD, but decreased in patients on SHD. Regression of LVMI was independent of dry weight which was unchanged in LNHD and SHD but increased in DHD. In contrast to SHD, phosphate control and Ca x P product improved in DHD and LNHD with less phosphate binding tablets. Intact PTH did not change in SHD, but decreased in DHD and LNHD. Hemoglobin increased in groups on intensified treatments, but fell in SHD. EPO resistance index fell in LNHD, but increased in DHD and SHD.
Conclusion:
While reduction in 24-h blood pressure was not achieved by intensified dialysis, both schedules showed favourable effects on LVMI and FS with less antihypertensive medication. This was independent of reduction in dry weight. These effects were more pronounced in DHD patients. In contrast, in SHD patients, stable 24-h blood pressure and reduction in LVMI were achieved on the expense of an increasing amount of antihypertensive medication and with worsening of FS.

Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:15
Chronopharmacokinetics: Circadian Rhythms and Influence on Drug Response
The time of drug administration is an important factor to consider, as it can influence the toxic dose of a drug. For example, a study conducted by Prins et al. in 1997 examined the effects of the timing of...
 01:22
Heart Failure VI: Adjunct Therapies
 01:25
Hemodialysis III: Nursing Management
 01:25
Hemodialysis I: Introduction
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
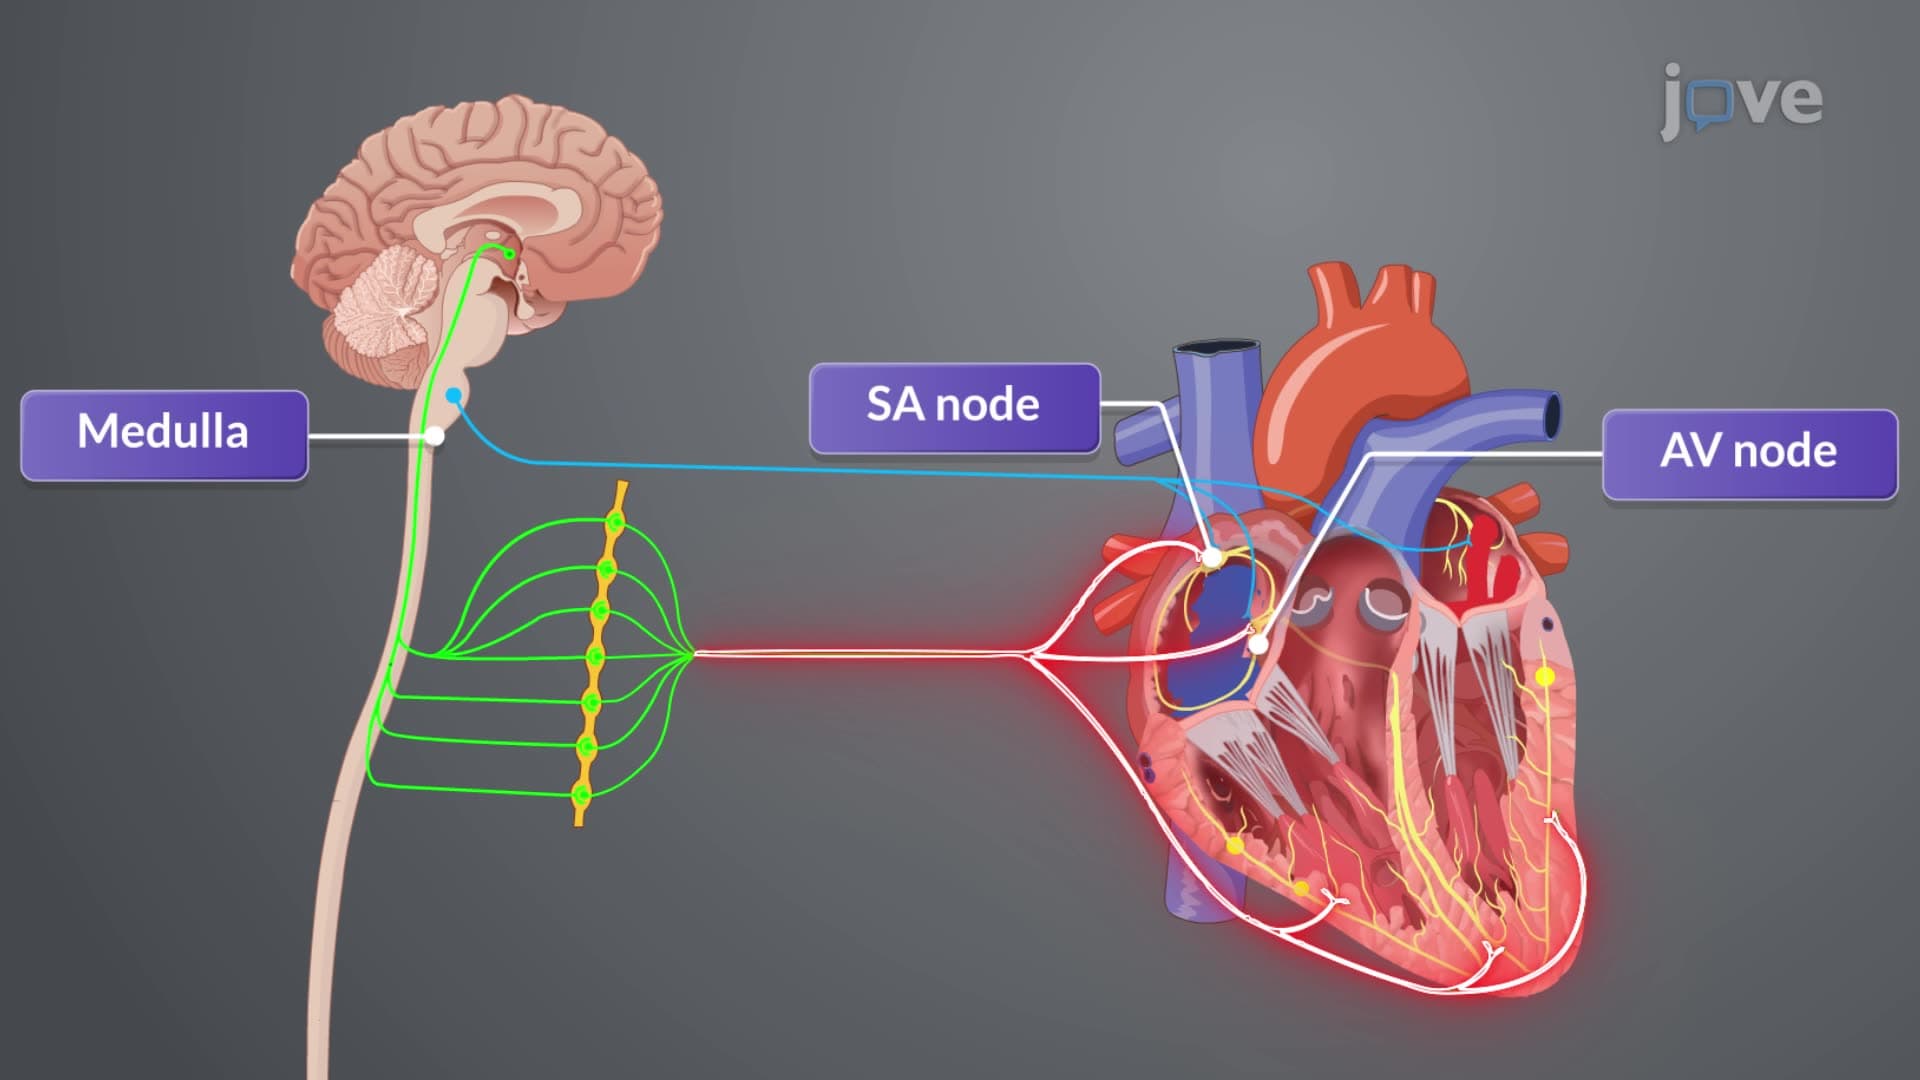
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...