Related Experiment Video
Updated: Jul 17, 2026


Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
[Recurrent varices at the groin and popliteal fossa after surgical treatment]
1Chirurgie Vasculaire, 26 chemin de Décines, 69680 Chassieu. m.perrin.chir.vasc@wanadoo.fr

Abstract:
Patients who undergo surgery involving the groin and the popliteal fossa often develop recurrent varices which require careful management. Several surveys using various classification systems have estimated the prevalence of recurrent varices after groin and popliteal surgery. Patients may seek medical care for various reasons: unsightly recurrent varicose veins, vein-related symptoms, appearance of cutaneous or subcutaneous changes, concerns about the health risk related to their veins or limitation of activity. Recurrent varices may also be found at routine follow-up examinations. An analysis of recurrence at this location reveals three main mechanisms: incomplete resection of the saphenofemoral or saphenopopliteal junctions in patients with an initially incompetent terminal valve. The persisting reflux feeds the tributaries connected at the saphenous stump; the second mechanism is related to neovascularisation that reconnects the deep venous system with the superficial network; the neo-veins are valveless. This phenomenon appears to be more frequent when the resection of the saphenous vein ending has been complete; the third mechanism is due to a tactical error; the refluxive pelvic veins that had not been diagnosed feed the varices. Duplex scanning identifies the different possible mechanisms and provides anatomical and hemodynamic data. Interventional treatment methods after varices recurrence are redosurgery, sclerotherapy and pelvic vein embolization when they are at issue. All these methods are described in details. Results provided by these treatments are analysed. Unfortunately no randomized control study enables grade A or B recommendations. Personally we suggest that ultrasound guided foam sclerotherapy should be the first-line treatment except when duplex scanning reveals an intact incompetent saphenous stump at the saphenofemoral junction or/and saphenopopliteal junction with a massive reflux filling the varicose network.
Related Concept Videos
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:15
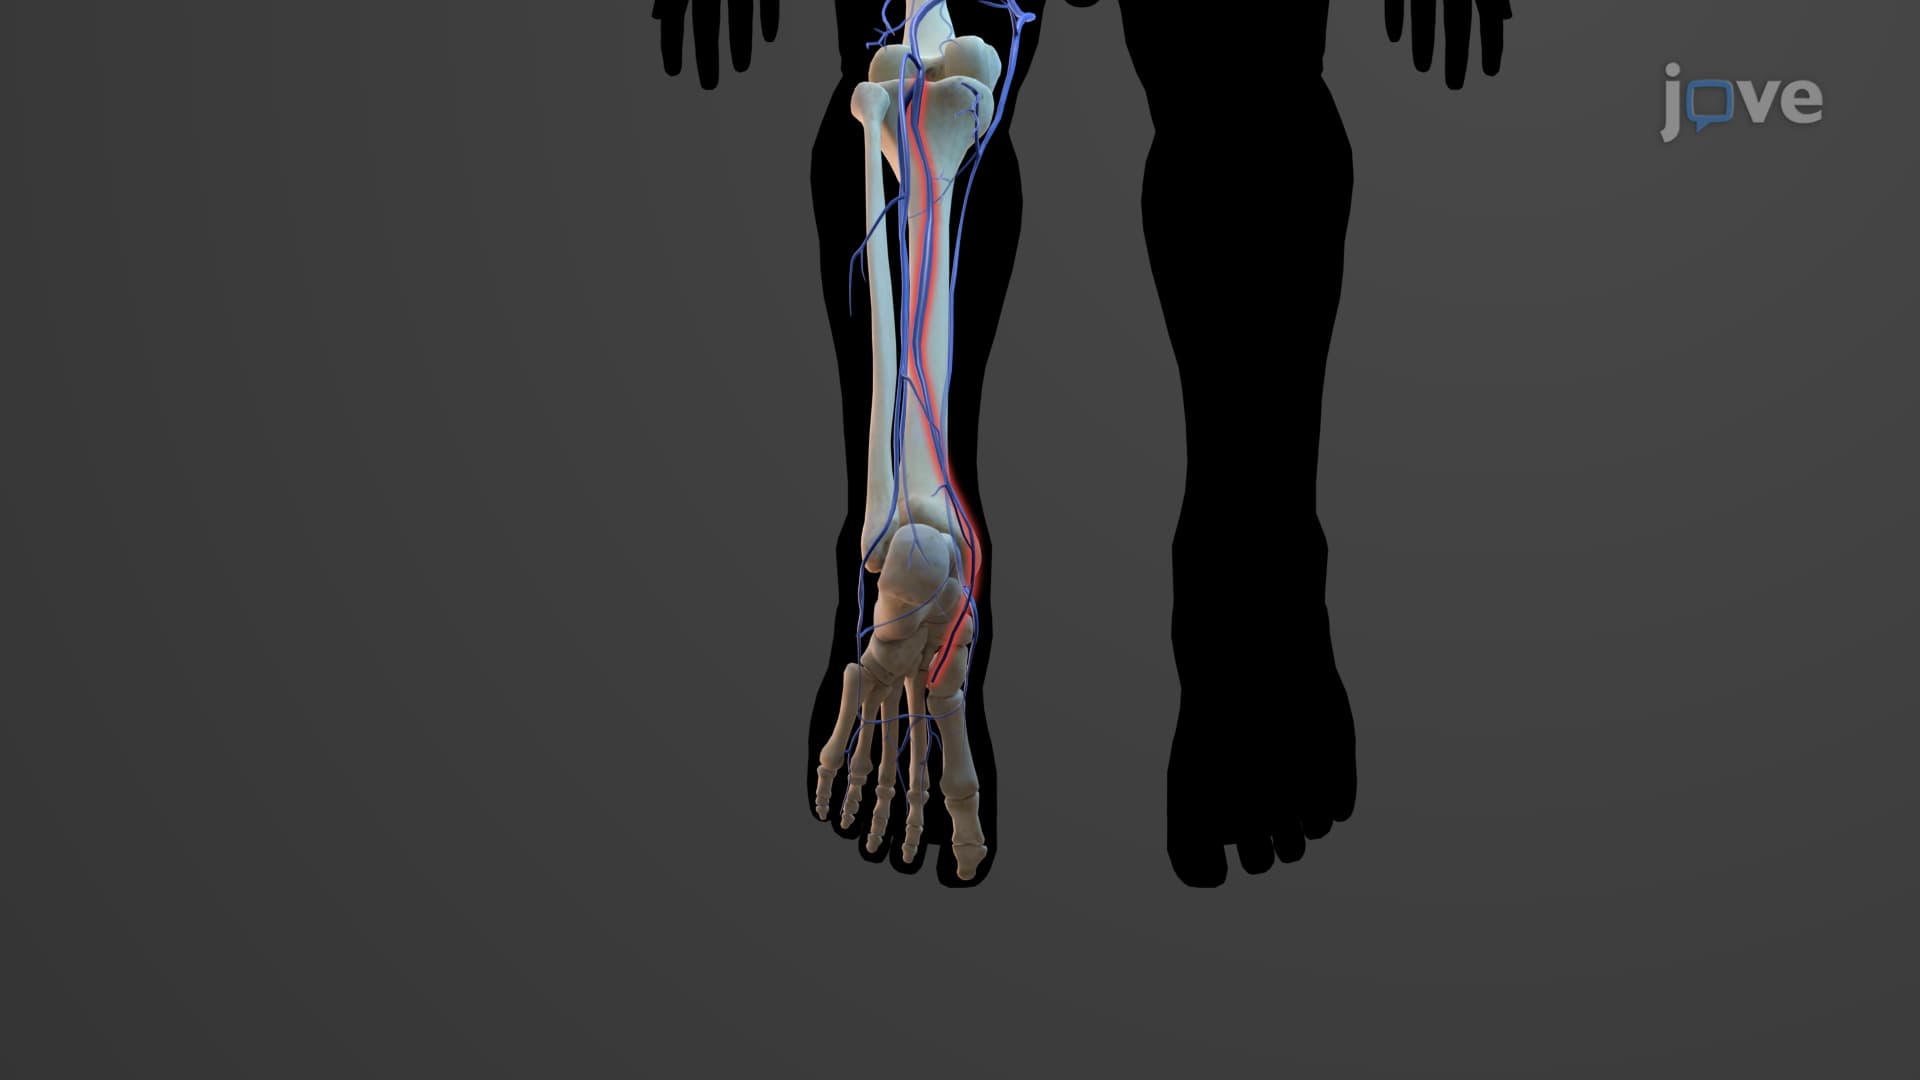
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:24
Esophageal Varices-I: Introduction
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins I: Introduction