Related Experiment Video
Updated: Jul 17, 2026
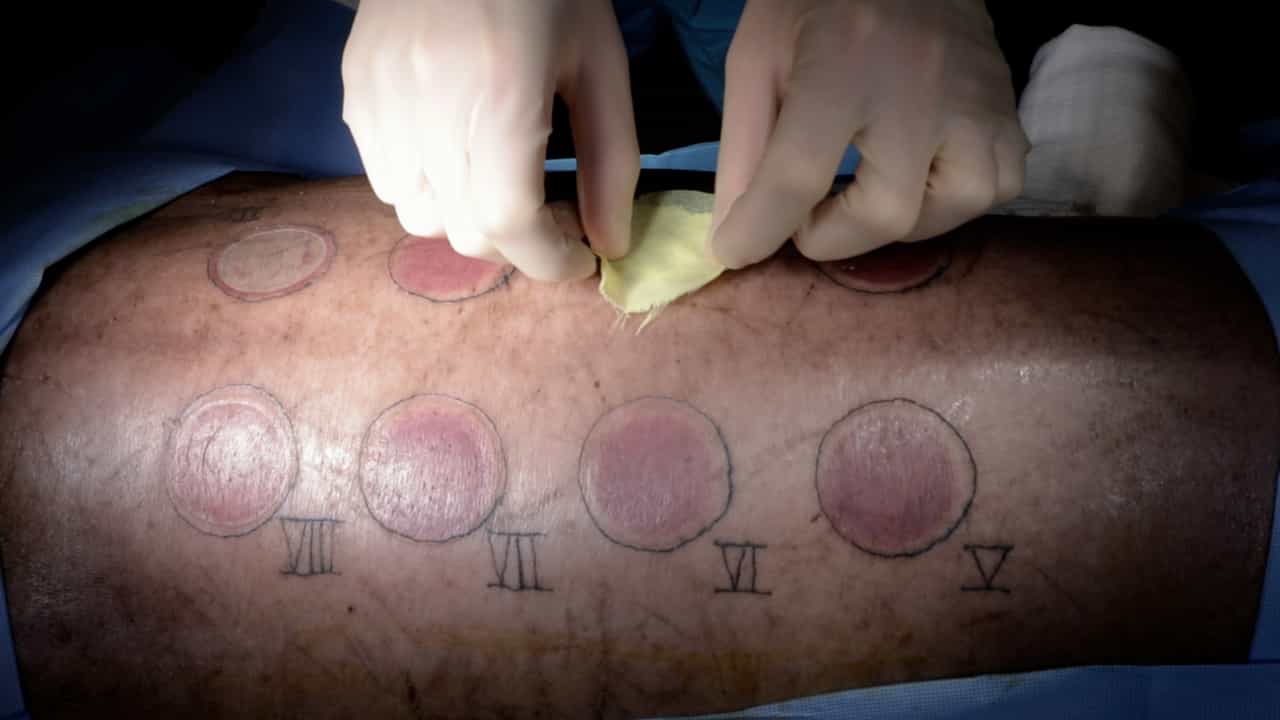

A Swine Burn Model for Investigating the Healing Process in Multiple Depth Burn Wounds
Published on: February 23, 2024
Demographics of the homeless in an urban burn unit
Areta Kowal-Vern1, Barbara A Latenser
1Sumner L. Koch Burn Center, Department of Trauma, John H. Stroger, Jr., Hospital of Cook County, Chicago, Illinois 60612, USA.

Abstract:
There are few articles about the homeless in burn literature. We sought to determine the demographic characteristics of the homeless citizens admitted to an urban burn center. This was a retrospective review from March 1999 to May 2004. Statistical analysis included chi2 and one-way analysis of variance. There were 1615 burn admissions, and 73 (4.5%) of these patients were homeless. Although the %TBSA affected was similar for the homeless and domiciled patients, the mean (+/-SD) age of the homeless was 44 +/- 10 years and their length of stay was 15 +/- 15 days, compared with 31 +/- 22 years and 9 +/- 13 days, respectively, for the domiciled. Twenty-one (29%) of the 73 homeless were admitted for frostbite, vs 21 (1.4%) of the 1542 domiciled patients (P= .000). Because of the frostbite, the majority (53%) arrived in the winter, compared with 15% in each of the other three seasons (P= .000). The homeless had a higher frequency of acute and chronic ethanol and cocaine use than the domiciled population (21% vs 6%). There was no significant difference between the homeless and the domiciled population in %TBSA affected, nutritional values, and assault frequency. More than half of the homeless patient admissions to the burn unit resulted from assault or frostbite. The homeless were mainly African-Americans and Caucasians, with a higher frequency of ethanol and cocaine use than in the domiciled burn population. Lack of discharge options for the homeless prolonged the average length of stay, leading to increased costs, often borne by the burn unit.

Related Concept Videos
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 02:16
Stereotype Content Model
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:14
Fundamental Attribution Error
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities