Related Experiment Video
Updated: Jul 17, 2026
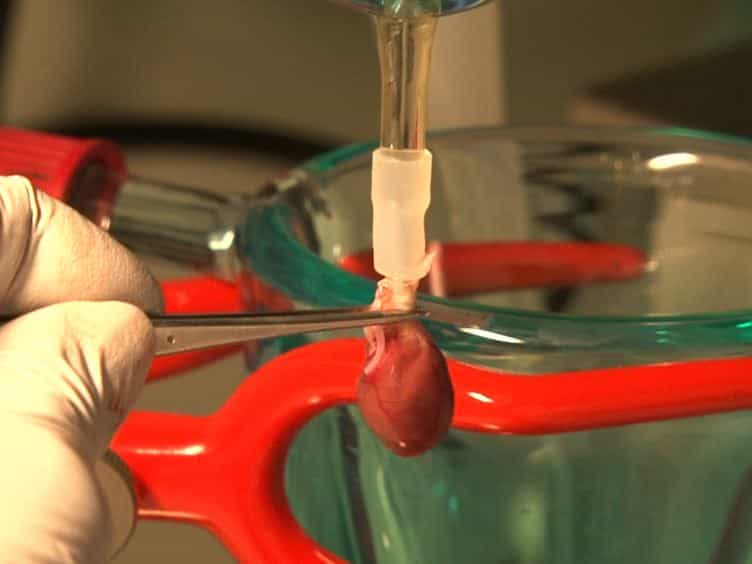

Measurement of Antibody Effects on Cellular Function of Isolated Cardiomyocytes
Published on: March 8, 2013
Antiarrhythmic effect of atorvastatin on autoimmune myocarditis is mediated by improving myocardial repolarization
Qizhu Tang1, Ji Huang, Haiyan Qian
1Department of Cardiology, Renmin Hospital of Wuhan University, 238 Jiefang Rd, Wuhan 430060, P.R. China. qzhtang@yahoo.com

Insights
Atorvastatin, a statin, reduces inflammation and improves heart electrical activity in myocarditis. It lessens inflammatory markers and normalizes ion channel function in heart cells, offering potential antiarrhythmic benefits.
Area of Science:
- Cardiology
- Immunology
- Pharmacology
Background:
- Myocarditis involves inflammation and oxidative stress, impacting cardiac function.
- HMG-CoA reductase inhibitors (statins) are known for anti-inflammatory and antioxidant properties.
Purpose of the Study:
- To investigate the effects of atorvastatin on inflammatory progression in experimental autoimmune myocarditis (EAM).
- To assess atorvastatin's impact on cardiac electrophysiological changes, specifically action potential duration (APD) and ion channel currents in ventricular myocytes.
Main Methods:
- Utilized an animal model of EAM in BALB/c mice.
- Administered atorvastatin and evaluated inflammatory markers (TNF-alpha, IFN-gamma).
- Performed whole-cell patch-clamp experiments to measure ventricular cardiomyocyte APD and potassium currents.
Main Results:
- Atorvastatin treatment attenuated inflammatory infiltration and reduced TNF-alpha and IFN-gamma levels in EAM hearts.
- Ventricular cardiomyocyte APD, prolonged in EAM, was normalized by atorvastatin.
- Atorvastatin mitigated the decrease in outward potassium currents observed in EAM myocytes.
Conclusions:
- Atorvastatin ameliorates EAM progression by suppressing inflammatory cytokine levels.
- The drug exhibits antiarrhythmic effects by modulating cardiomyocyte ion channel activity, thereby improving myocardial repolarization.
Abstract:
3-Hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase inhibitors, or statins, are known to inhibit cholesterol biosynthesis and prevent inflammation and oxidative stress. To explore the effects of atorvastatin on inflammatory progression and major cardiac electrophysiological changes in myocarditis, we used an animal model of experimental autoimmune myocarditis (EAM). In this model, BALB/c mice were treated with atorvastatin and we evaluated the levels of inflammation markers and currents of ionic channels that contribute to the duration of action potential (APD) of ventricular myocytes. We demonstrated that atorvastatin treatment attenuated inflammatory infiltration and suppressed the increase in TNF-alpha and IFN-gamma levels in EAM mouse hearts. In the whole-cell patch-clamp experiment, ventricular cardiomyocyte APD was prolonged in EAM group, and atorvastatin blocked this change. We further found that atorvastatin attenuated the significant decrease in outward potassium currents in EAM myocytes. Our results suggested that atorvastatin may ameliorate EAM progression by reducing inflammatory cytokine level. Atorvastatin exerted the antiarrhythmic effects by selectively affecting cardiomyocyte ion channel activity and therefore improves myocardial repolarization.
Related Concept Videos
 01:14
Myocarditis III: Medical Management
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:21
Myocarditis I: Introduction
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:22
Myocarditis IV: Nursing Management
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...