Related Experiment Video
Updated: Jul 17, 2026
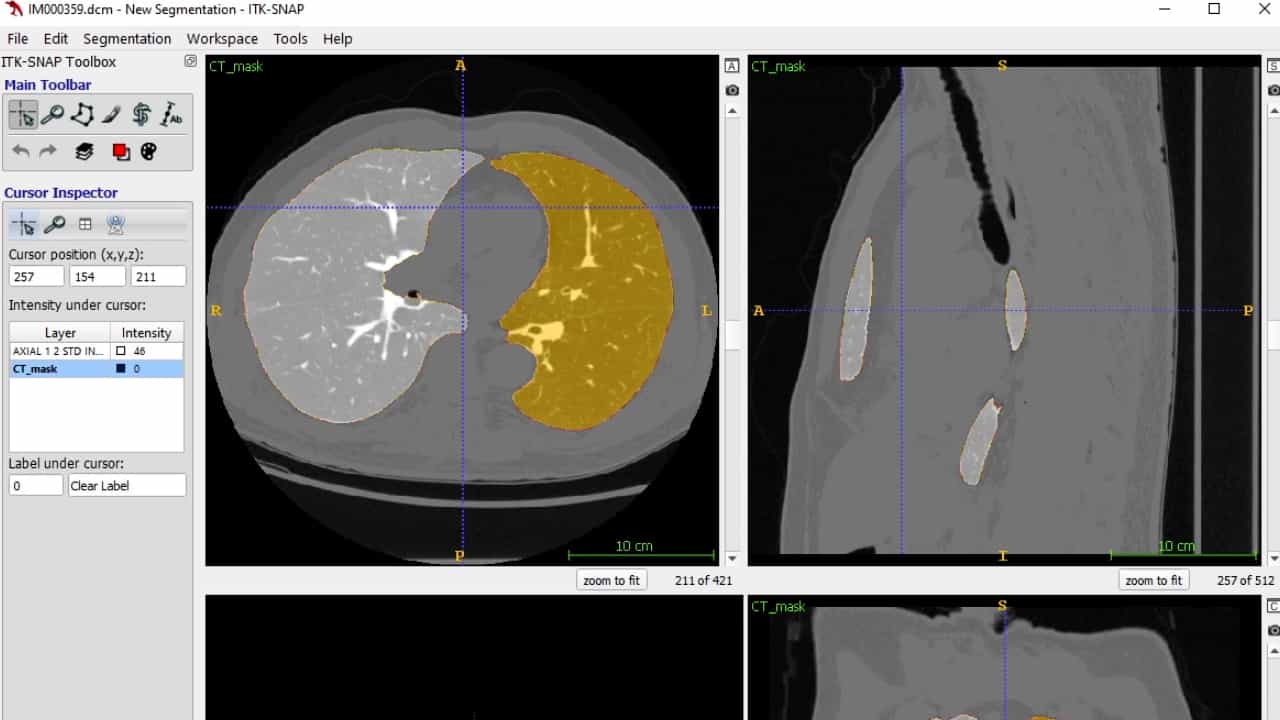

Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Characteristics of trapped lung: pleural fluid analysis, manometry, and air-contrast chest CT
John T Huggins1, Steven A Sahn, Jay Heidecker
1Division of Pulmonary, Critical Care,, Allergy and Sleep Medicine, Medical University of South Carolina, PO Box 250625, Charleston, SC 29425, USA.

Study Objectives:
To review the pleural fluid characteristics, pleural manometry, and radiographic data of patients who received a diagnosis of trapped lung in our pleural diseases service.
Design:
Retrospective case series.
Methods:
The procedure records of 247 consecutive patients who underwent pleural manometry at the Medical University of South Carolina between October 2002 and November 2005 were reviewed. Eleven patients in whom a diagnostic pneumothorax was introduced were identified. Manometry data, radiographic findings, pleural fluid analysis, final clinical diagnosis, and information regarding the initial pleural insult were retrieved from the medical record.
Results:
All 11 patients had a clinical diagnosis of trapped lung. The causes of trapped lung were attributed to coronary artery bypass graft surgery, uremia, thoracic radiation, pericardiotomy, spontaneous bacterial pleuritis and repeated thoracentesis, and complicated parapneumonic effusion. Mean pleural fluid pH was 7.30, pleural fluid lactate dehydrogenase (LDH) was 124 IU/L, and pleural fluid total protein was 2.9 g/dL. Pleural fluid was paucicellular with mononuclear cell predominance. Pleural space elastance was increased in all cases and ranged from 19 to 149 cm H(2)O/L of pleural fluid removed. All demonstrated abnormal visceral pleural thickness on air-contrast chest CT.
Conclusions:
Trapped lung is a clinical entity characterized by the presence of a restrictive visceral pleural peel that was first described in 1967. The pleural fluid is paucicellular, LDH is low, and protein may be in the exudative range. The elevated total pleural fluid protein may be related to factors other than active pleural inflammation or malignancy and does not exclude the diagnosis.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:08
Pneumothorax II: Pathophysiology
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Pleural Disorders: Types and Brief Description
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...