Related Experiment Video
Updated: Aug 17, 2026


Surgical Treatment for Benign Prostatic Hyperplasia: Holmium Laser Enucleation of the Prostate (HoLEP).
Published on: March 6, 2018
The emerging role of alpha antagonists in the therapy of benign prostatic hyperplasia
1Department of Urology, Medical College of Wisconsin, Milwaukee 53226.

Abstract:
The rationale for using alpha blockade to treat benign prostatic hyperplasia (BPH) is based on the physiology and pharmacology of prostate smooth muscle. Approximately 20% of the area density of the prostate adenoma is smooth muscle. In vitro isometric tension studies have demonstrated that the contractile properties of the human prostate adenoma are mediated primarily by alpha 1 adrenoceptors. Alpha blockers presumably decrease the resistance along the prostatic urethra by relaxing the smooth muscle component of the prostate. Over the past 14 years, at least 16 clinical trials have confirmed the efficacy of alpha blockade in the treatment of BPH. The primary advantage of terazosin over all other commercially available alpha blockers is that its longer half-life allows for a once-daily dosage regimen. Two Phase II studies conducted in the United States, a multicenter dose titration randomized withdrawal study and the author's personal experience with terazosin, are summarized in this report. Overall, the peak urinary flow rate increased 50% and the mean urinary flow rate increased 46% following terazosin therapy. The mean obstructive and irritative scores improved 67% and 35%, respectively. The adverse reactions occurring with an incidence greater than 5% included headache (10%), asthenia (7%), and dizziness (14%). All adverse events were reversible on termination of therapy. The preliminary experiences with alpha blockers for the treatment of BPH has been very encouraging. Yet, the definitive role of alpha blockade in BPH awaits the reporting of multicenter, randomized placebo-controlled studies.

Related Concept Videos
 01:31
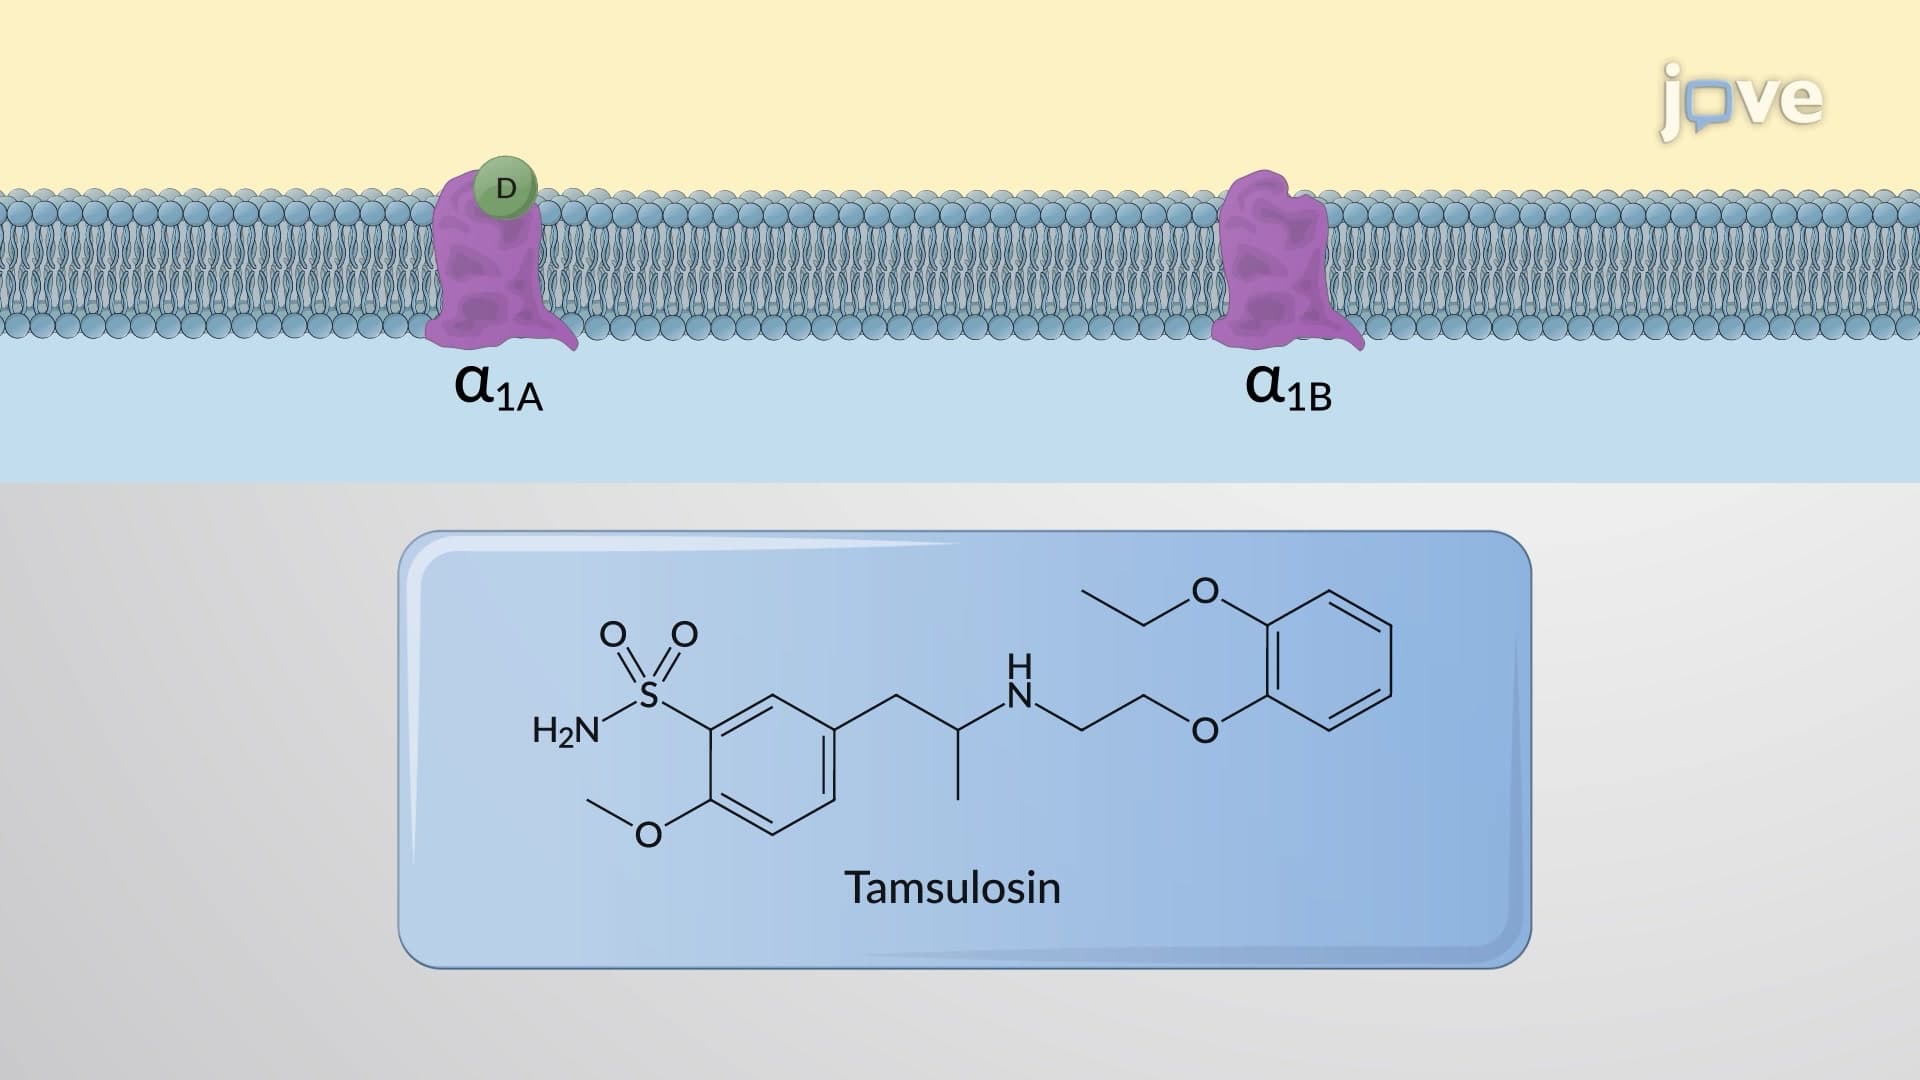
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:17
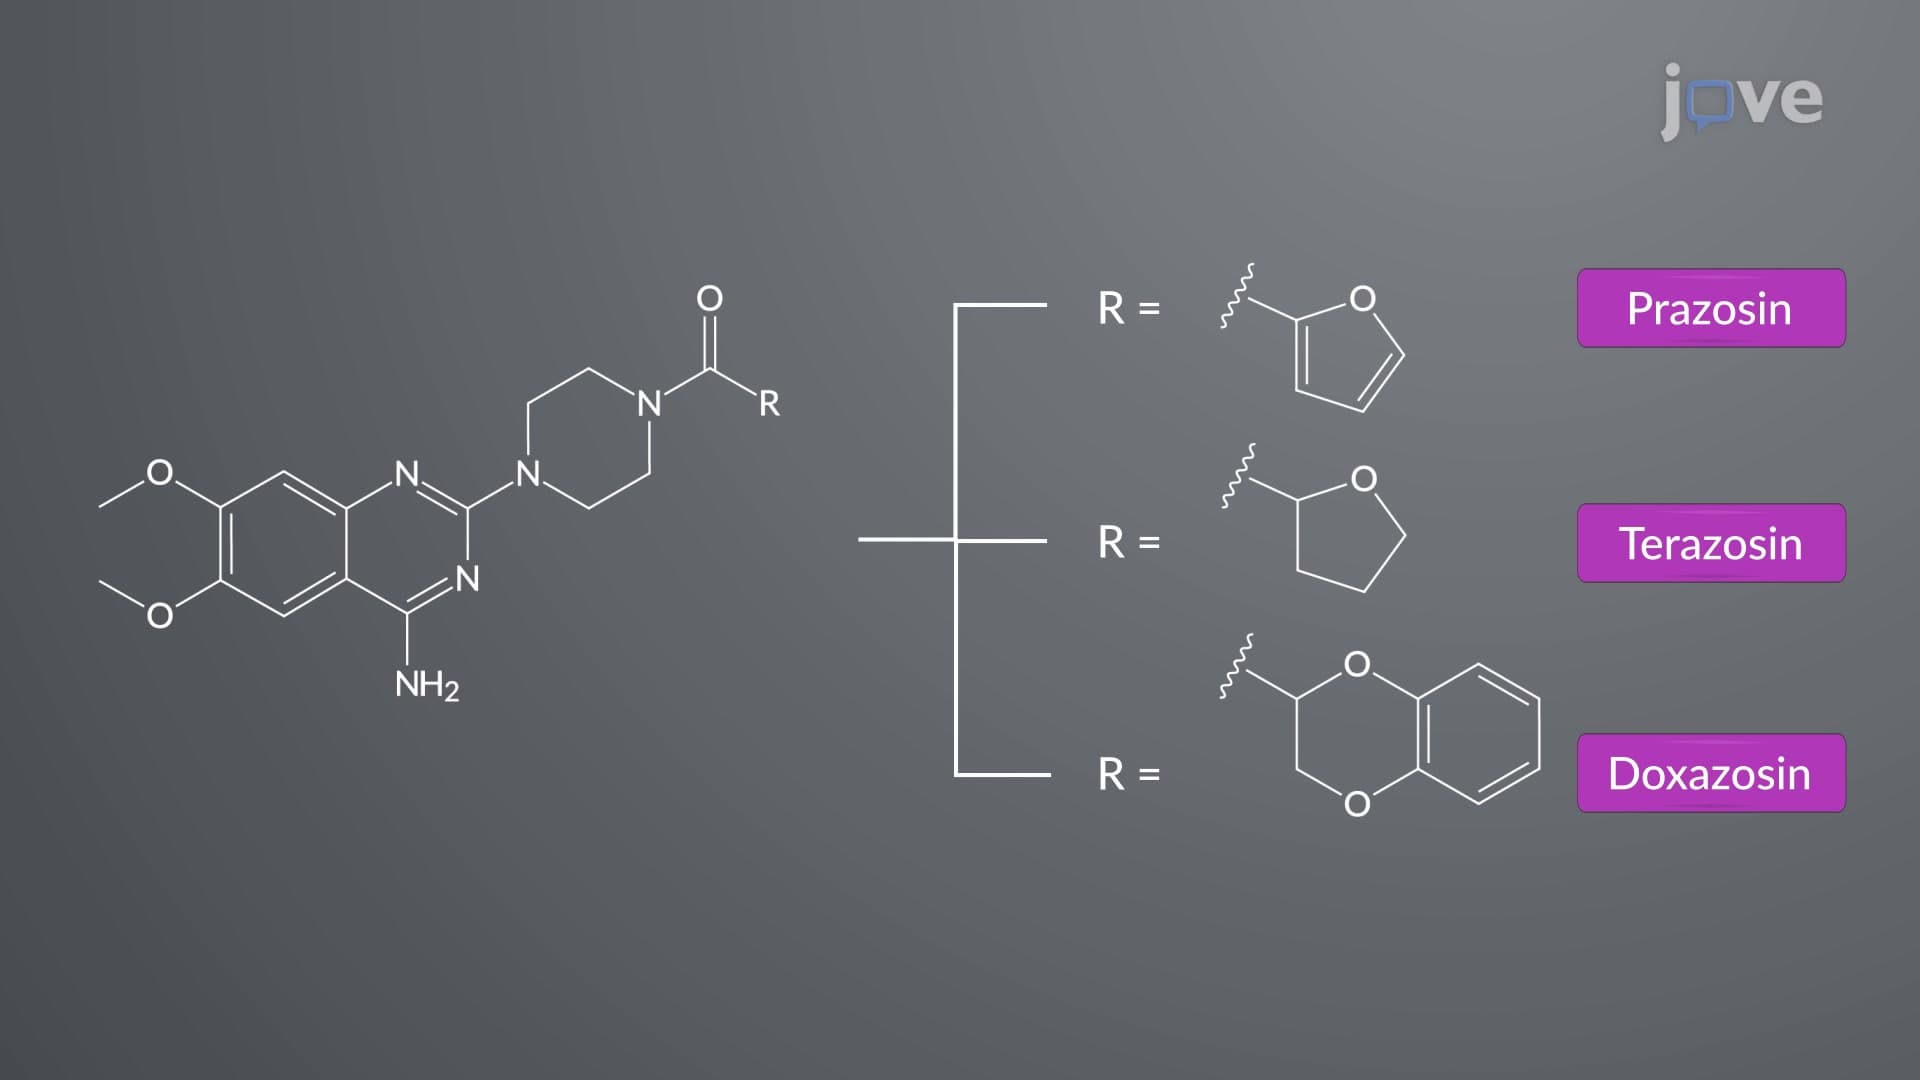
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
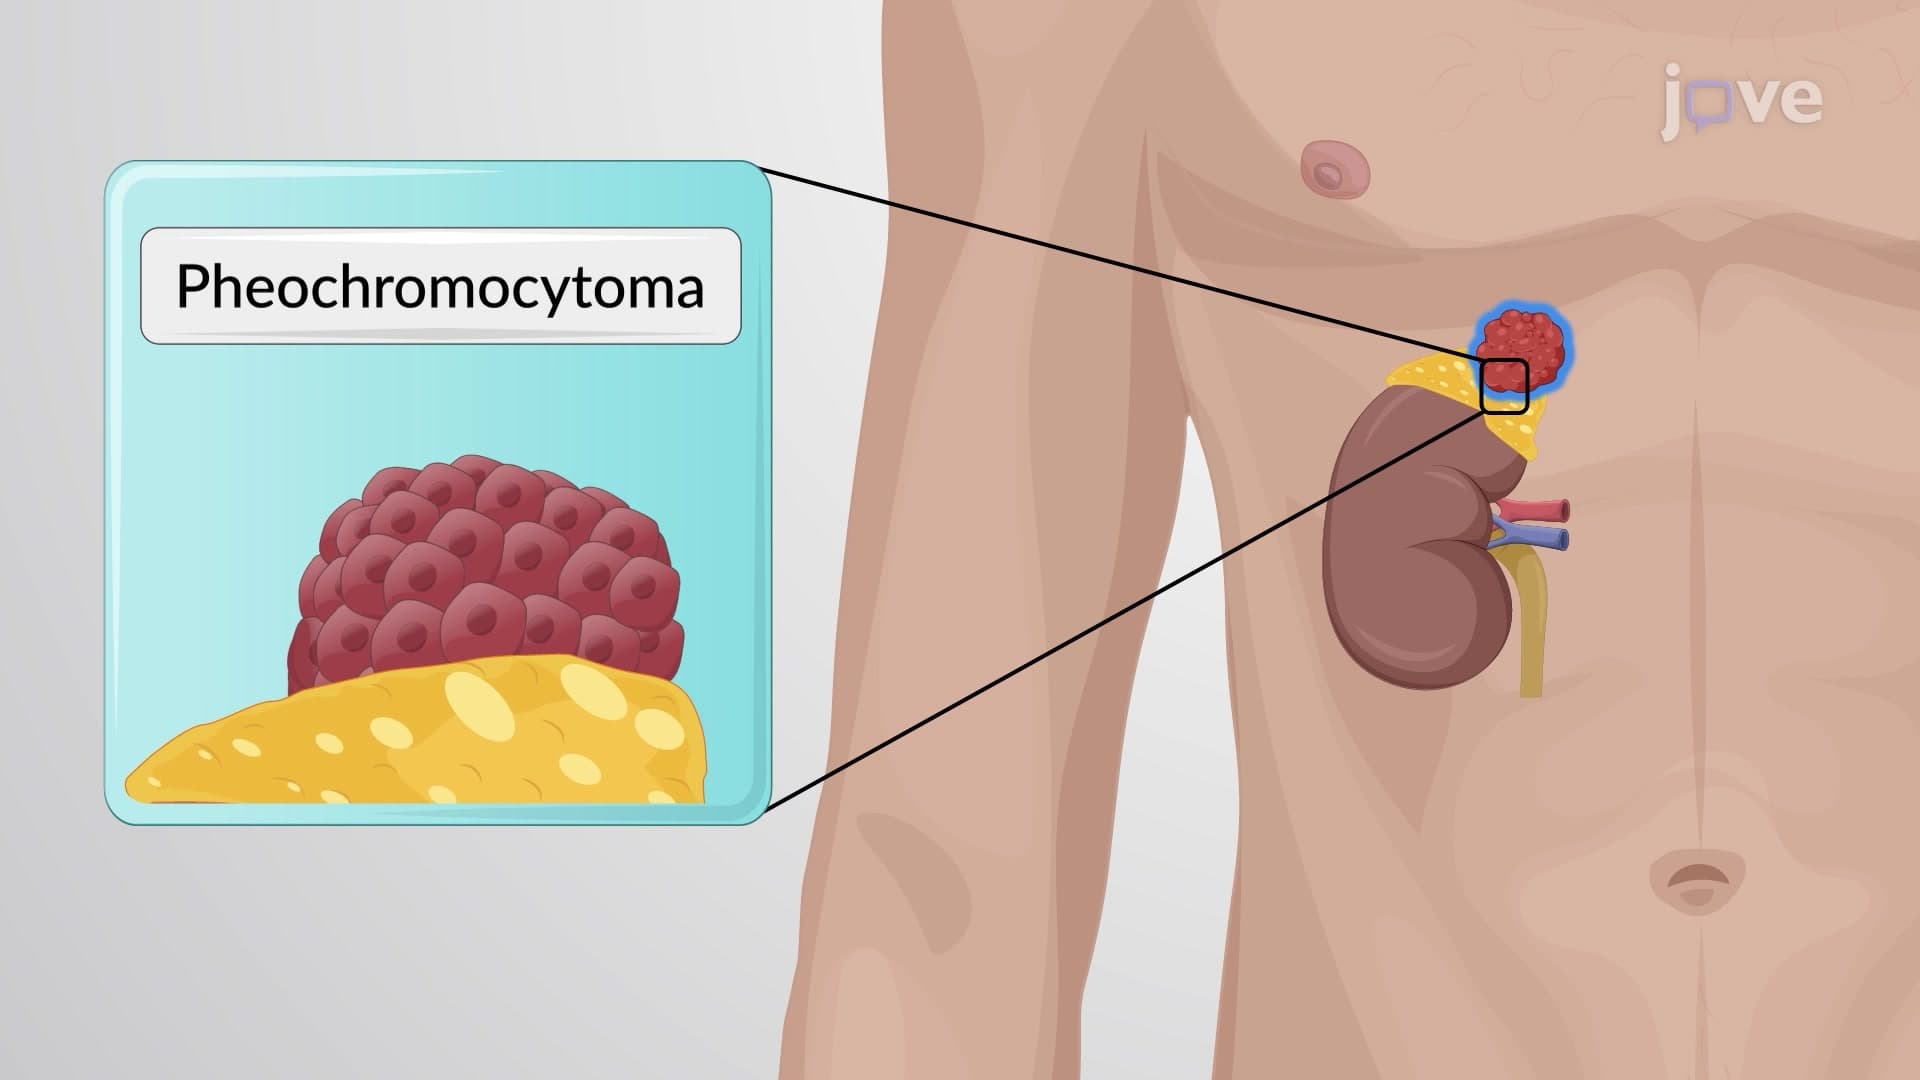
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers