Related Experiment Video
Updated: Jul 17, 2026

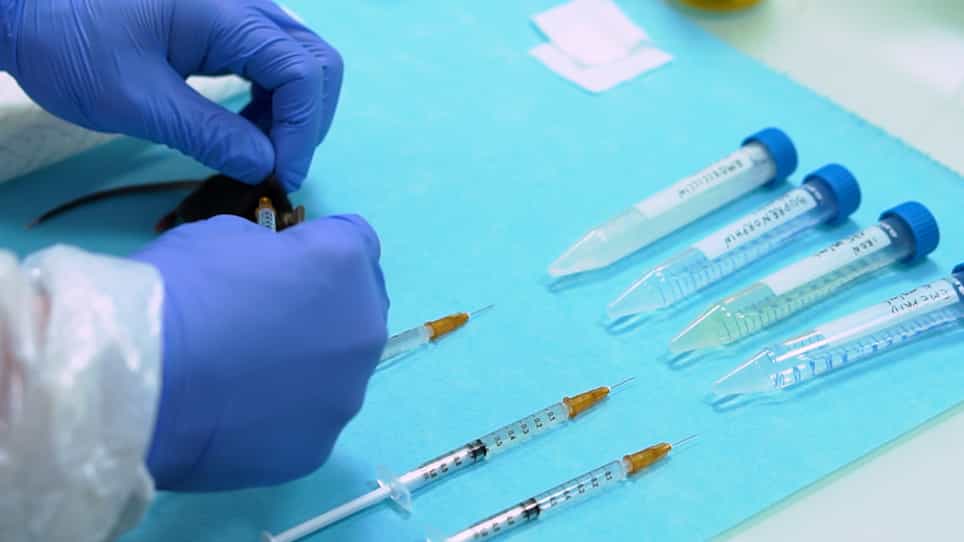
Tissue Engineering of the Intestine in a Murine Model
Published on: December 1, 2012
[Nutritional and surgical management of short bowel syndrome. Our last 6 patients' experience]
1Unitat Integrada Hospital Sant Joan de Déu-Clínic. mcastanon@hsjdbcn.org

Background:
Children cause of intestinal failure is short-bowel syndrome. It provokes an altered absorption of nutrients and makes patients to be dependent on parenteral nutrition (PN) while they wait or not for an intestinal transplantation, with its side effects. It is crucial to achieve the maximum efficiency of remaining intestine. Many surgical techniques have been led to reduce stasis of dilated small intestine and improve the mucosal surface area for absorption.
Methods:
Six patients have presented intestinal failure because of a surgical resection during newborn period. 2 gastroschisis, 2 intestinal atresias (Apple-peel), 1 necrotizing enterocolitis (NEC) and 1 midgut volvulus. 4 preserve ileocecal valve (ICV): 2 Apple-peel, 1 NEC and the midgut volvulus. The shortest length of bowel after resection were 12cm without ICV (gastroschisis) and 18cm with ICV in a preterm newborn of 24 weeks of gestational age (midgut volvulus). Tapering and plication have been done in Apple-peel cases. No complementary surgical techniques have been necessary in NEC and volvulus. Gastroschisis cases had 12 and 40 cm of small bowel without ICV. In the first one, during newborn period an intestinal lengthening according to Bianchi was done, followed by sequential transversal enteroplasty (STEP), partial gastrectomy and plication of 1st and 2nd duodenal portion. In the second, an STEP was done. All patients have received cycled and optimized PN (COPN) in our centre, only one case (gastroschisis) proceeding from another centre had received standard PN and developed a great hepatic affectation.
Results:
2 Apple-peel have been adapted to normal enteral nutrition after 3 and 18 months of COPN, such as NEC and volvulus (3-6 months). One gastroschisis (12cm) has a normal hepatic function with free oral nutrition and home COPN at 23 months. The other one (40cm) has COPN and started enteral nutrition 1 month after surgery, although its hepatic function remains altered.
Conclusions:
Parenteral nutrition is essential for these patients to survive. We would like to enhance the importance of COPN in order to preserve hepatic function. Surgical procedures aim to avoid stasis and bacterial overgrowth and improve intestinal motility. Different techniques may be used alone or sequentially. The purpose of this management is to achieve nutritional autonomy or increase waiting time before intestinal transplantation.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...