Related Experiment Video
Updated: Jul 17, 2026

5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
Correction of chronic metabolic acidosis for chronic kidney disease patients
P Roderick1, N S Willis, S Blakeley
1University of Southampton, School of Medicine, Community Clinical Sciences, Level C, South Academic Block, Southampton General Hospital, Southampton, UK, S016 6YD. pjr@soton.ac.uk

Background:
Metabolic acidosis is a feature of chronic kidney disease (CKD) due to the reduced capacity of the kidney to synthesise ammonia and excrete hydrogen ions. It has adverse consequences on protein and muscle metabolism, bone turnover and the development of renal osteodystrophy. Metabolic acidosis may be corrected by oral bicarbonate supplementation or in dialysis patients by increasing the bicarbonate concentration in dialysate fluid.
Objectives:
To examine the benefits and harms of treating metabolic acidosis in patients with CKD, both prior to reaching end-stage renal disease (ESRD) or whilst on renal replacement therapy (RRT), with sodium bicarbonate or increasing the bicarbonate concentration of dialysate.
Search Strategy:
We searched CENTRAL (The Cochrane Library, issue 4 2005), Cochrane Renal Group's specialised register (October 2005), MEDLINE (1966 - October 2005) and EMBASE (1980 - October 2005).
Selection Criteria:
Randomised controlled trials (RCTs), crossover RCTs and quasi-RCTs investigating the correction of chronic metabolic acidosis in adults or children with CKD.
Data Collection And Analysis:
Outcomes were analysed using relative risk (RR) and weighted mean difference (MD) for continuous measures.
Main Results:
We identified three trials in adult dialysis patients (n = 117). There were insufficient data for most outcomes for meta-analysis. In all three trials acidosis improved in the intervention group though there was variation in achieved bicarbonate level. There was no evidence of effect on blood pressure or sodium levels. Some measures of nutritional status/protein metabolism (e.g. SGA, NP NA) were significantly improved by correction in the one trial that looked in these in detail. There was heterogeneity of the effect on serum albumin in two trials. Serum PTH fell significantly in the two trials that estimated this, there was no significant effect on calcium or phosphate though both fell after correction. Complex bone markers were assessed in one study, with some evidence for a reduction in bone turnover in those with initial high bone turnover and an increase in low turnover patients. The studies were underpowered to assess clinical outcomes, in the one study that did there was some evidence for a reduction in hospitalisation after correction.
Authors' Conclusions:
The evidence for the benefits and risks of correcting metabolic acidosis is very limited with no RCTs in pre-ESRD patients, none in children, and only three small trials in dialysis patients. These trials suggest there may be some beneficial effects on both protein and bone metabolism but the trials were underpowered to provide robust evidence.

Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:29
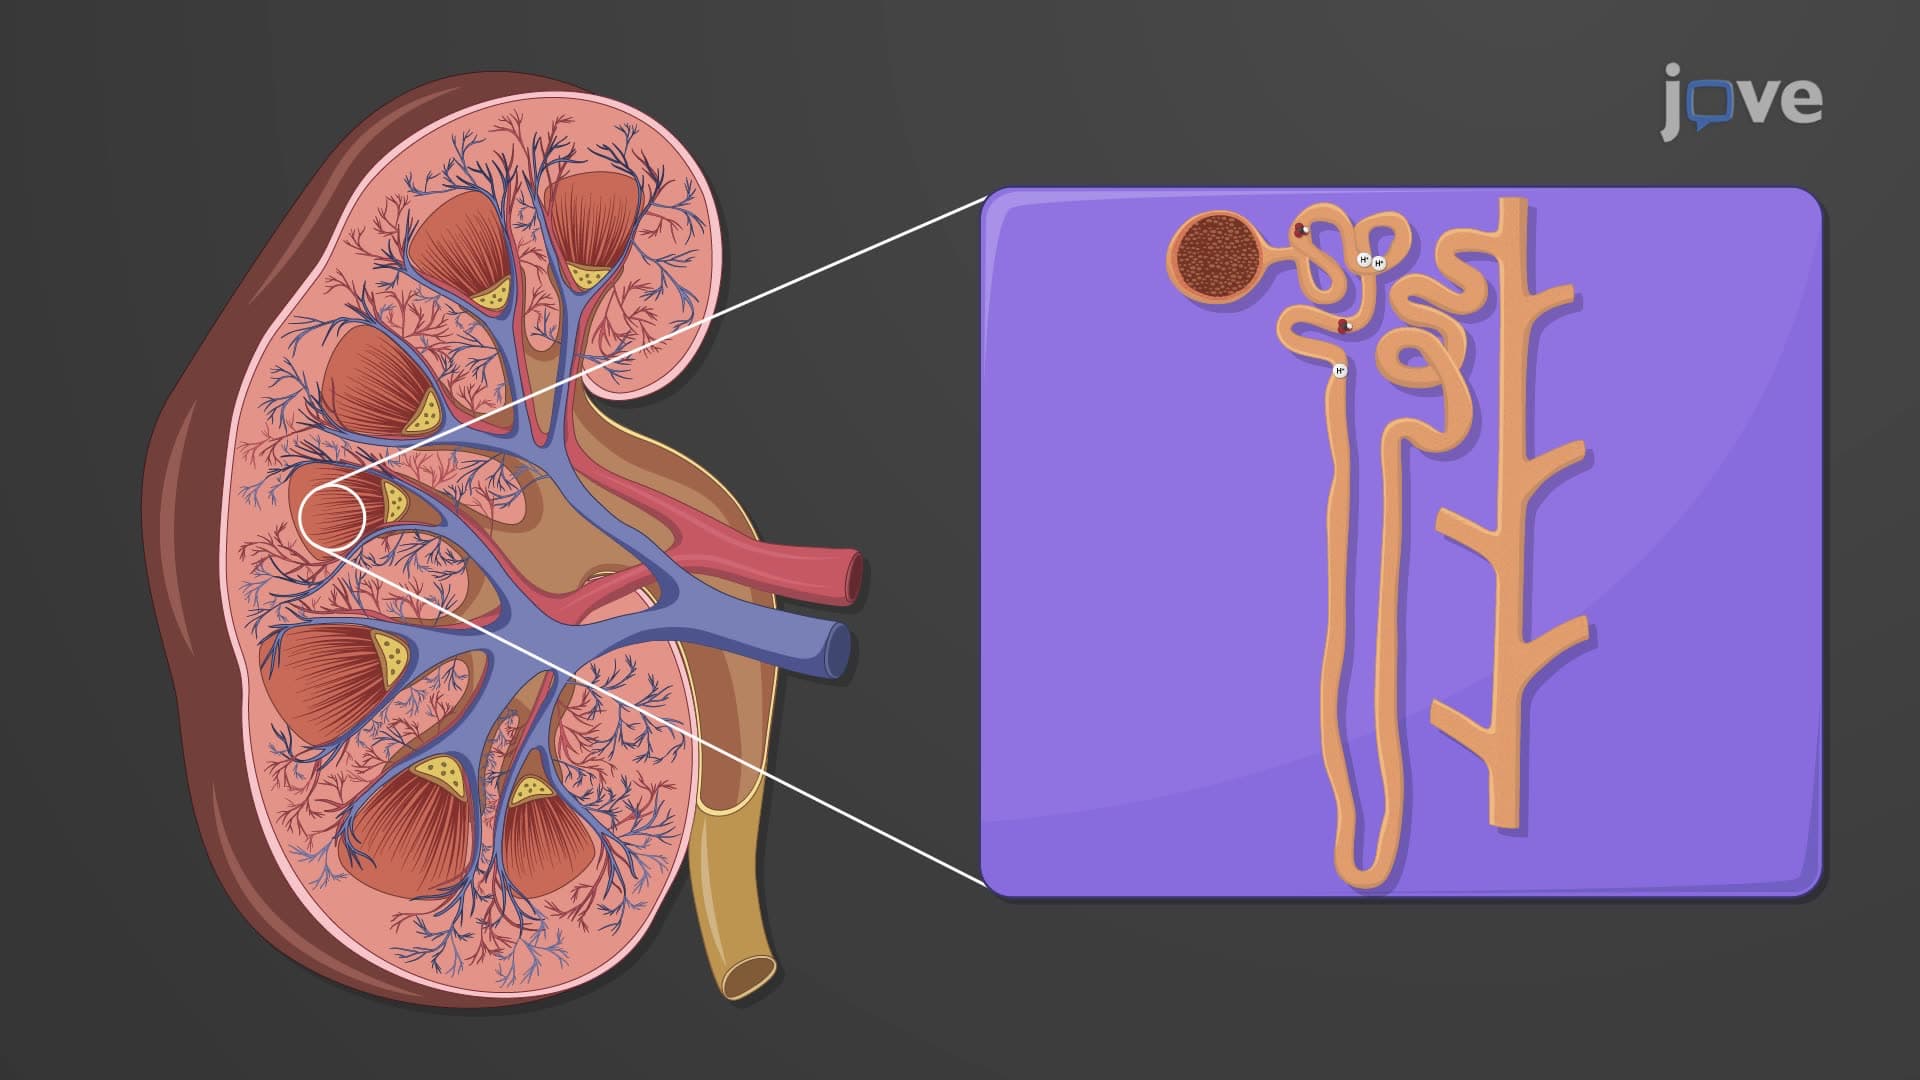
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...