The effect of inotropes on morbidity and mortality in preterm infants with low systemic or organ blood flow
Related Experiment Video
Updated: Jul 17, 2026
Transcutaneous Microcirculatory Imaging in Preterm Neonates
Published on: December 31, 2015
D A Osborn1, M Paradisis, N Evans
1Royal Prince Alfred Hospital, RPA Newborn Care, Missenden Road, Camperdown, New South Wales, Australia, 2050. david.osborn@email.cs.nsw.gov.au

Background:
Low systemic blood flow (SBF) is common in extremely premature infants in the first day after birth and has been associated with peri / intraventricular haemorrhage (PIVH), necrotising enterocolitis (NEC), mortality and developmental impairment.
Objectives:
To determine the effect of specific inotropes on morbidity and mortality in preterm infants with low systemic blood flow
Search Strategy:
Searches were made of The Cochrane Central Register of Controlled Trials (CENTRAL, The Cochrane Library, Issue 1, 2006 ), MEDLINE (1966 - April 2006), EMBASE (1980 - April 2006) and CINAHL (1982 - April 2006), supplemented by searches of abstracts of conference proceedings, citations of reviews and expert informants.
Selection Criteria:
Random and quasi-random controlled trials of inotropes enrolling preterm infants with low systemic or organ blood flow in the neonatal period.
Data Collection And Analysis:
Independent assessment of trial eligibility, quality and data extraction by each review author. Synthesis of data using relative risk (RR) and weighted mean difference (WMD) using standard methods of the Cochrane Collaboration.
Main Results:
No studies that compared an inotrope to no treatment in preterm infants with low SBF were found. One study (Osborn 2002a) was found that compared dobutamine versus dopamine. The study was of adequate methodology. It enrolled 42 infants < 30 weeks gestation and < 12 hours after birth with low SVC flow. The trial compared the effect of dobutamine versus dopamine titrated 10 to 20 mug/kg/min with the goal of increasing and maintaining SVC flow > 40 ml/kg/min. No significant difference was reported in mortality to discharge (RR 1.41, 95% CI 0.79, 2.52), PIVH (RR 1.01, 95% 0.52, 1.97), grade 3 or 4 PIVH (RR 0.39, 95% CI 0.12, 1.31) or NEC. At three years, there was no significant difference in cerebral palsy, deafness, Developmental quotient > 2 sd below norm or combined disability (RR 0.10, 95% CI 0.01, 1.56). Surviving infants treated with dobutamine had a significantly higher development quotient (MD 35.00, 95% CI 17.68, 52.32). There was no significant difference in death or disability at the latest time reported (RR 0.95, 95% CI 0.66, 1.38). For secondary outcomes, there was no significant difference in periventricular leucomalacia, renal impairment, pulmonary haemorrhage, retinopathy of prematurity or CLD at 36 weeks. There was no significant difference in treatment failure. Dobutamine produced a significantly greater increase in SVC flow at the highest dose reached (MD 13.10, 95% CI 2.87, 23.33), whereas dopamine produced a significantly greater increase in mean BP at 10 and 20 mug/kg/min and at the highest dose reached (MD -7.20, 95% CI -11.41, -2.99).
Authors' Conclusions:
In preterm infants with low systemic blood flow, there is some evidence that dobutamine is better than dopamine at increasing and maintaining systemic blood flow. The only eligible trial did not demonstrate any consistent differences in clinical outcomes. However, this study was not sufficiently powered to prove or disprove effects on clinical outcomes. It is unclear what is the most effective strategy for improving the cardiovascular status of immature infants in the first day. Further trials are needed to determine effective strategies for preventing and improving low systemic and organ blood flow.

Related Concept Videos
 01:26
Heart Failure Drugs: Inotropic Agents
 01:19
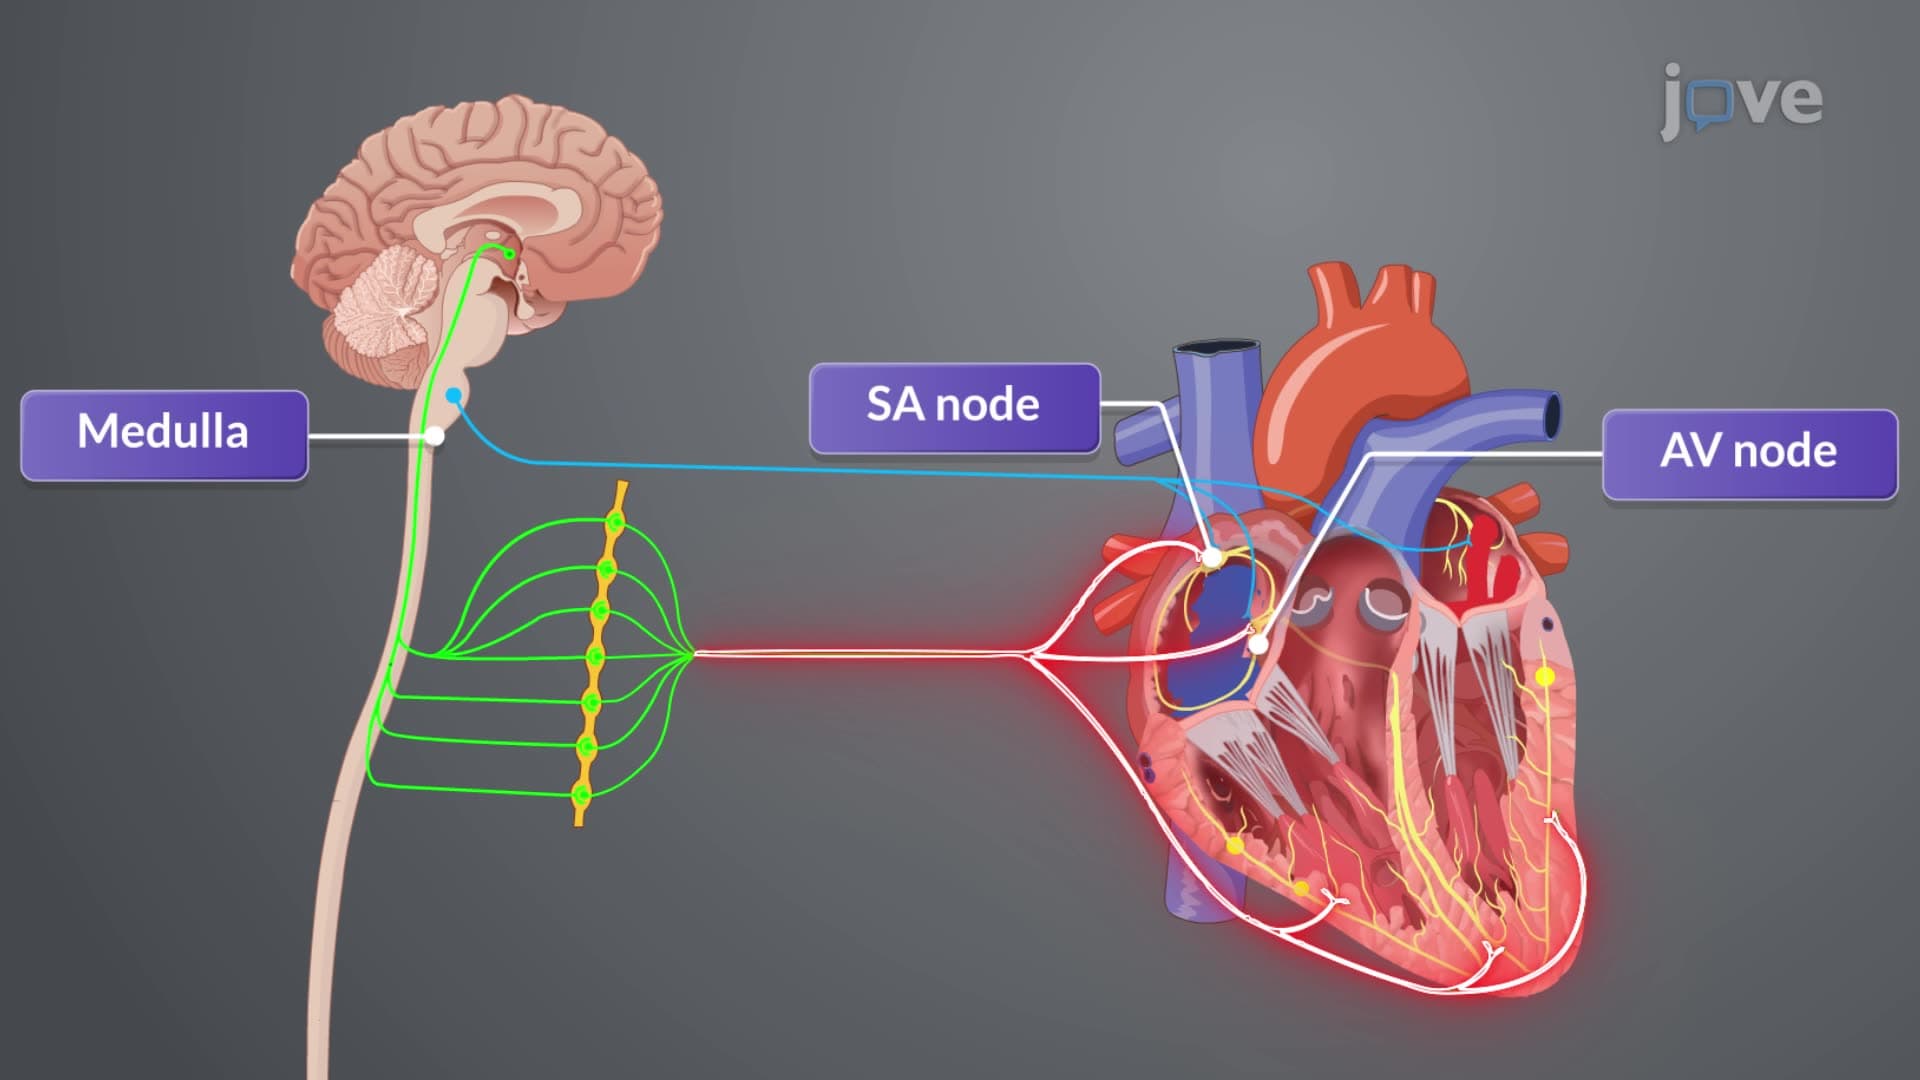
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
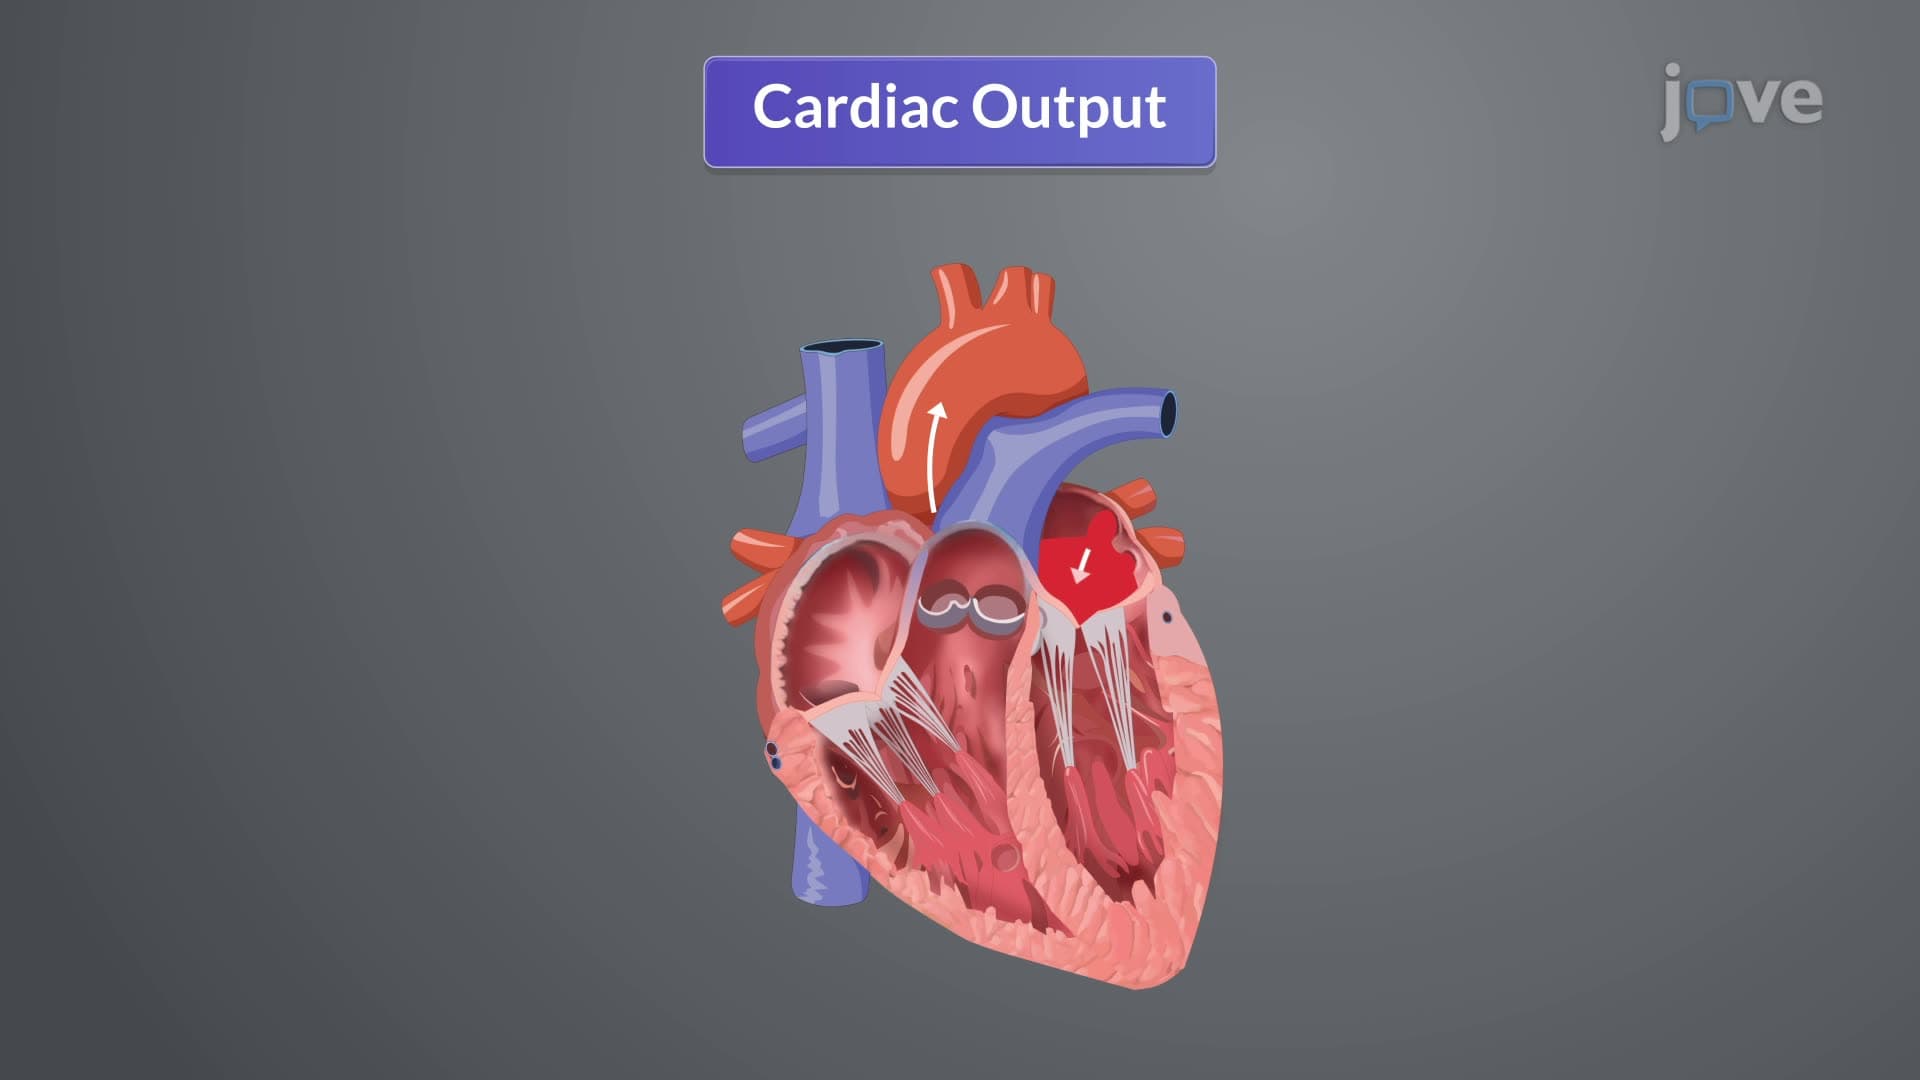
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:22
Heart Failure Drugs: β-Blockers
 01:22
Mitral Stenosis I: Introduction
 01:30
Heart Failure V: Medical Management