Hindfoot instability in cavovarus deformity: static and dynamic balancing
Related Experiment Video
Updated: Jul 17, 2026
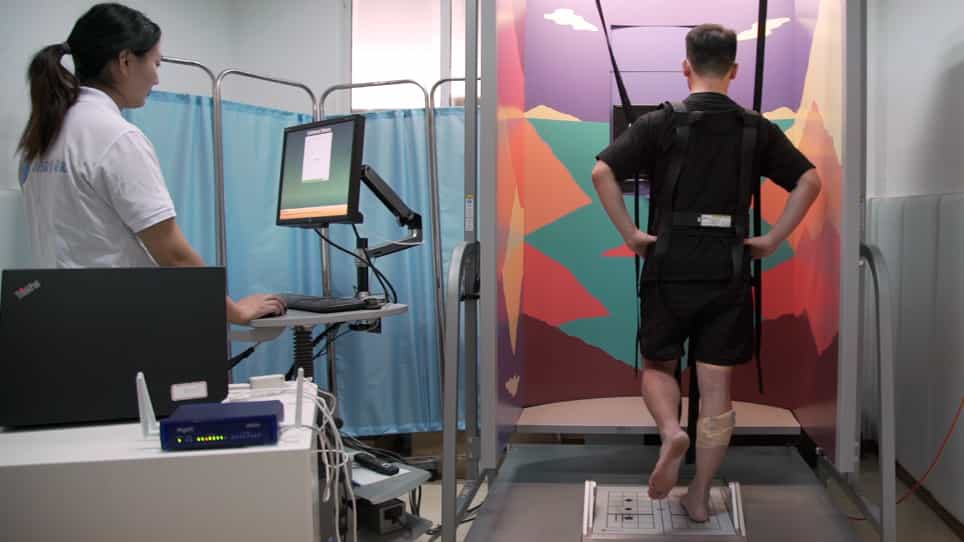
Evaluating Postural Control and Lower-extremity Muscle Activation in Individuals with Chronic Ankle Instability
Published on: September 18, 2020
Patrick Vienne1, Ralph Schöniger, Naeder Helmy
1Uniklinik Balgrist, Orthopaedics, Forchstrasse 340, Zurich, 8008, Switzerland. patrick.vienne@balgrist.ch

Background:
Chronic lateral ankle instability has been associated with varus deformity of the hindfoot, hyperactivity of the peroneus longus muscle, and insufficiency of the lateral ligaments. Many operative procedures have been described to correct this problem, but instability can recur if all contributing components are not treated. The purpose of this study was to offer an approach in the diagnosis and treatment of recurrent lateral ankle instability.
Methods:
Eight consecutive patients (nine feet) were treated for recurrent chronic lateral ankle instability. The average age at surgery was 25 (range 8 to 37) years. All patients had prior operative procedures that failed and had persistent pain and functional instability of the ankle joint. After clinical and radiographic examination, lateralizing calcaneal osteotomy to correct the structured varus deformity and peroneus longus to peroneus brevis tendon transfer to add dynamic correction were done in all patients. A Broström ligament reconstruction was added in four feet. All patients were evaluated clinically and radiographically at an average followup of 37 months. Preoperatively and postoperatively patients were evaluated by means of the American Orthopaedic Foot and Ankle Society (AOFAS) Score.
Results:
All patients were satisfied with the operation. The overall AOFAS-Score improved from 57 points preoperatively to 87 points postoperatively. Hindfoot alignment was restored to a valgus position at final evaluation.
Conclusions:
Recurrent chronic lateral ankle instability often is associated with chronic hindfoot malalignment and leads to functional impairment and patient discomfort. Clinical examination should determine the causes of instability. Varus malalignment of the hindfoot, hyperactivity of the peroneus longus muscle, and insufficiency of the lateral ligaments should be assessed and treated in a combined operative procedure to correct structured, static and dynamic components of the instability. The preliminary results of this particular approach are encouraging.
Related Concept Videos
 01:10
Ankle Joint
 00:49
Rigid Body Equilibrium Problems - I
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:28
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:21
Rigid Body Equilibrium Problems - II
Consider two children sitting on a seesaw, which has negligible mass. The first child has a mass (m1) of 26 kg and sits at point A, which is 1.6 meters (r1) from the pivot point B; the second child has a mass (m2) of 32 kg and sits at point C. How far from the pivot point B should the second child sit (r2) to balance the seesaw?