Related Experiment Video
Updated: Jul 17, 2026
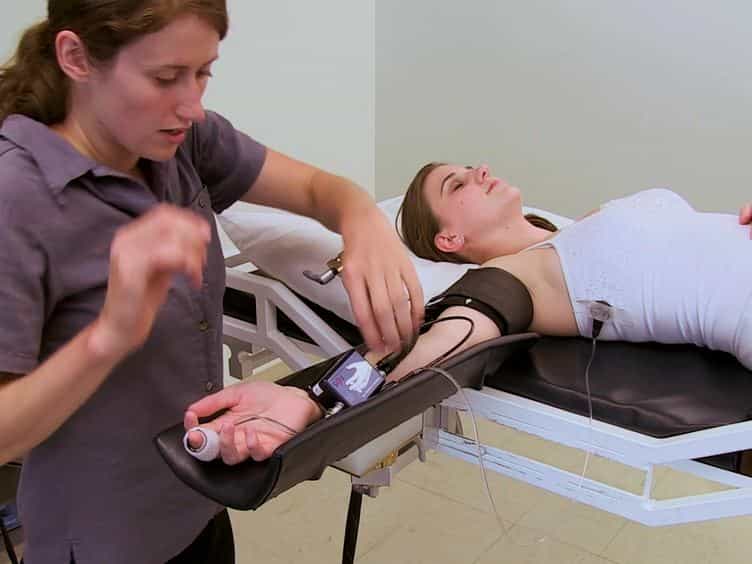
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
The clinical significance of the caloric second phase provoked by positional change in vertiginous patients
Sachiko Aoki1, Yasuko Arai, Natsumi Ide
1Department of Otolaryngology, Tokyo Women's Medical University, Medical Center East, Tokyo, Japan, USA. takekazu@vt.ms246.net

Abstract:
The reversal phase of caloric nystagmus is provoked when the lateral semicircular canal in a patient is reoriented from a vertical to a horizontal plane at the cessation of the caloric first phase, which we called the provoked caloric second phase. In investigating the clinical significance of the provoked caloric second phase, we recruited 102 vertiginous patients who had measurable caloric responses in both ears but no disorders of the central nervous system. We recorded the provoked caloric second phase in 188 (92%) of 204 ears in 102 patients. The average maximum slow-phase velocity of the caloric first phase was 26.9 degrees per second, and that of the provoked caloric second phase was 5.0 degrees per second. The maximum slow-phase velocity of the provoked caloric second phase correlated with that of the foregoing caloric first phase (r = -.84). Thus, we consider that the provoked caloric second phase is influenced largely by the foregoing caloric first phase. Furthermore, in the patients who responded normally to caloric stimulation, the directional preponderance of the provoked caloric second phase correlated with the directional preponderance of optokinetic after-nystagmus (r = .64). Hence, we conclude that the provoked caloric second phase reflects central vestibular asymmetry in patients with normal peripheral vestibular function.

Related Concept Videos
 01:15
Equilibrium and Balance
 01:29
Decreased Body Temperature
 01:22
Pathophysiology of Vomiting
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction