Related Experiment Video
Updated: Jul 17, 2026
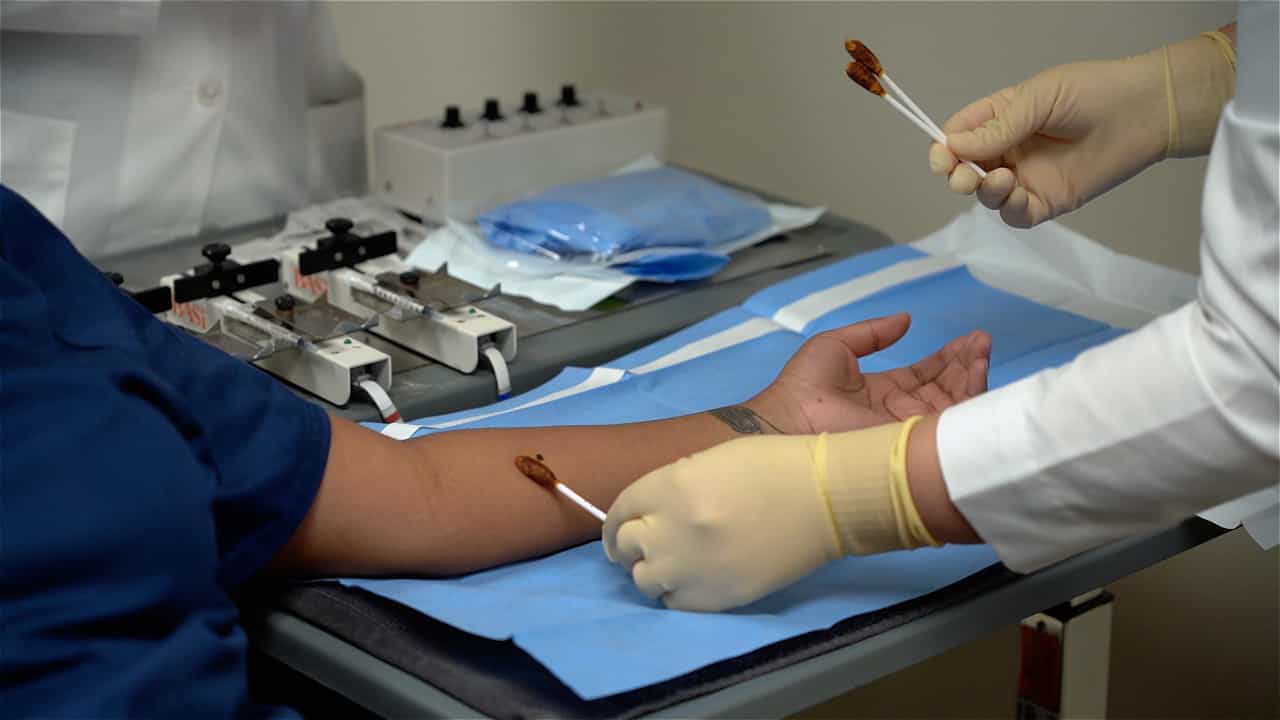

Intradermal Microdialysis: An Approach to Investigating Novel Mechanisms of Microvascular Dysfunction in Humans
Published on: July 21, 2023
Cutaneous postural vasoconstriction is modified by exogenous but not endogenous female hormones in young women
Gemma D Bishop1, Margaret D Brown
1School of Sport and Exercise Sciences, University of Birmingham, Birmingham, UK. gxb014@bham.ac.uk

Previously reported attenuation of skin postural vasoconstriction in women during the luteal menstrual cycle phase may be due to a progesterone-mediated decrease in myogenic or veno-arteriolar (VAR) mechanisms. Skin perfusion was measured in the shin and foot dorsum by Laser Doppler Fluxometry during leg dependency that increased vascular transmural pressure below (myogenic constriction only) and above (myogenic and VAR) the 25 mmHg threshold for activation of the VAR, and during venous distension to activate the VAR alone (cuff inflation to 50 mmHg). In six young women with normal menstrual cycles, vasoconstrictor responses to all interventions did not differ between days 7-13 (follicular) and 18-23 (luteal) of the normal menstrual cycle when progesterone levels were low and at their peak respectively. In eight women taking combined oral contraceptives (OC) and tested during pill consumption days, reductions in foot skin perfusion were smaller (P = 0.05) than in the luteal phase of the normal cycle for leg dependency below (-36.9 +/- 5.2% OC vs. -52.5 +/- 7.8% luteal, mean +/- S.E.M.) and above (-43.7 +/- 3.4% OC vs. -55.1 +/- 4.8% luteal) the VAR threshold, and for venous distension (-53.1 +/- 2.6% OC vs. 66.4 +/- 5.5% luteal). In women with normal menstrual cycles, impaired postural vasoconstriction may be confined to those who experience pre-menstrual symptoms rather than a direct effect of endogenous hormones. Reduced vasoconstriction in the dependent foot during OC use is consistent with the known vasodilator action of exogenous hormones and its long-term effects.
Previously reported attenuation of skin postural vasoconstriction in women during the luteal menstrual cycle phase may be due to a progesterone-mediated decrease in myogenic or veno-arteriolar (VAR) mechanisms. Skin perfusion was measured in the shin and foot dorsum by Laser Doppler Fluxometry during leg dependency that increased vascular transmural pressure below (myogenic constriction only) and above (myogenic and VAR) the 25 mmHg threshold for activation of the VAR, and during venous distension to activate the VAR alone (cuff inflation to 50 mmHg). In six young women with normal menstrual cycles, vasoconstrictor responses to all interventions did not differ between days 7-13 (follicular) and 18-23 (luteal) of the normal menstrual cycle when progesterone levels were low and at their peak respectively. In eight women taking combined oral contraceptives (OC) and tested during pill consumption days, reductions in foot skin perfusion were smaller (P = 0.05) than in the luteal phase of the normal cycle for leg dependency below (-36.9 +/- 5.2% OC vs. -52.5 +/- 7.8% luteal, mean +/- S.E.M.) and above (-43.7 +/- 3.4% OC vs. -55.1 +/- 4.8% luteal) the VAR threshold, and for venous distension (-53.1 +/- 2.6% OC vs. 66.4 +/- 5.5% luteal). In women with normal menstrual cycles, impaired postural vasoconstriction may be confined to those who experience pre-menstrual symptoms rather than a direct effect of endogenous hormones. Reduced vasoconstriction in the dependent foot during OC use is consistent with the known vasodilator action of exogenous hormones and its long-term effects.
More Related Videos
 08:41
Assessment of Vascular Tone Responsiveness using Isolated Mesenteric Arteries with a Focus on Modulation by Perivascular Adipose Tissues
Published on: June 3, 2019
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction while...
 01:40
Hormonal Regulation
 01:33
Hormonal Regulation
 01:26
Varicose Veins I: Introduction
 01:28
Menopause