Optimising antimicrobial therapy in diabetic foot infections
Related Experiment Videos
Nalini Rao1, Benjamin A Lipsky
1Division of Infectious Disease, Department of Medicine, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania 15232-1381, USA. raon@upmc.edu

Abstract:
Foot infections are common and the most serious lower extremity complication contributing to amputations, particularly in patients with diabetes mellitus. Infection is most often a consequence of foot ulcerations, which typically follows trauma to a neuropathic foot. Foot infections may be classified as mild, moderate and severe; this largely determines the approach to therapy. Gram-positive bacteria are the sole causative pathogens for most mild and moderate infections. These infections can usually be treated with culture-based narrow-spectrum antibacterials along with appropriate surgical debridement in an outpatient setting. In contrast, severe infections are often polymicrobial, requiring hospitalisation and treatment with broad-spectrum antibacterials along with appropriate medical and surgical interventions. The initial empirical antibacterial regimen may be tailored based on the results of culture and sensitivity tests from properly obtained specimens. Several antibacterial regimens have demonstrated effectiveness in randomised controlled trials, but no single regimen has shown superiority. Managing diabetic foot osteomyelitis is particularly controversial and requires reliable cultures to select an appropriate antibacterial regimen. Surgical resection of the infected and necrotic bone favours a good outcome in chronic osteomyelitis. The recommended duration of antibacterial therapy ranges from 1 to 4 weeks for soft tissue infection, to >6 weeks for unresected osteomyelitis. The incidence of meticillin-resistant Staphylococcus aureus infection is increasing in both the healthcare setting and the community. This should be considered when selecting an antibacterial, especially if the patient does not improve with initial antibacterial therapy. Certain other organisms, such as Pseudomonas aeruginosa and Enterococcus spp., while potentially pathogenic, are often colonisers that do not require targeted therapy.
Insights
Diabetic foot infections, often from ulcers, require tailored treatments based on severity. Prompt diagnosis and appropriate antibiotic therapy are crucial for preventing lower extremity amputations.
Area of Science:
- Infectious Diseases
- Diabetology
- Podiatry
Background:
- Foot infections are a severe complication of diabetes mellitus, frequently leading to lower extremity amputations.
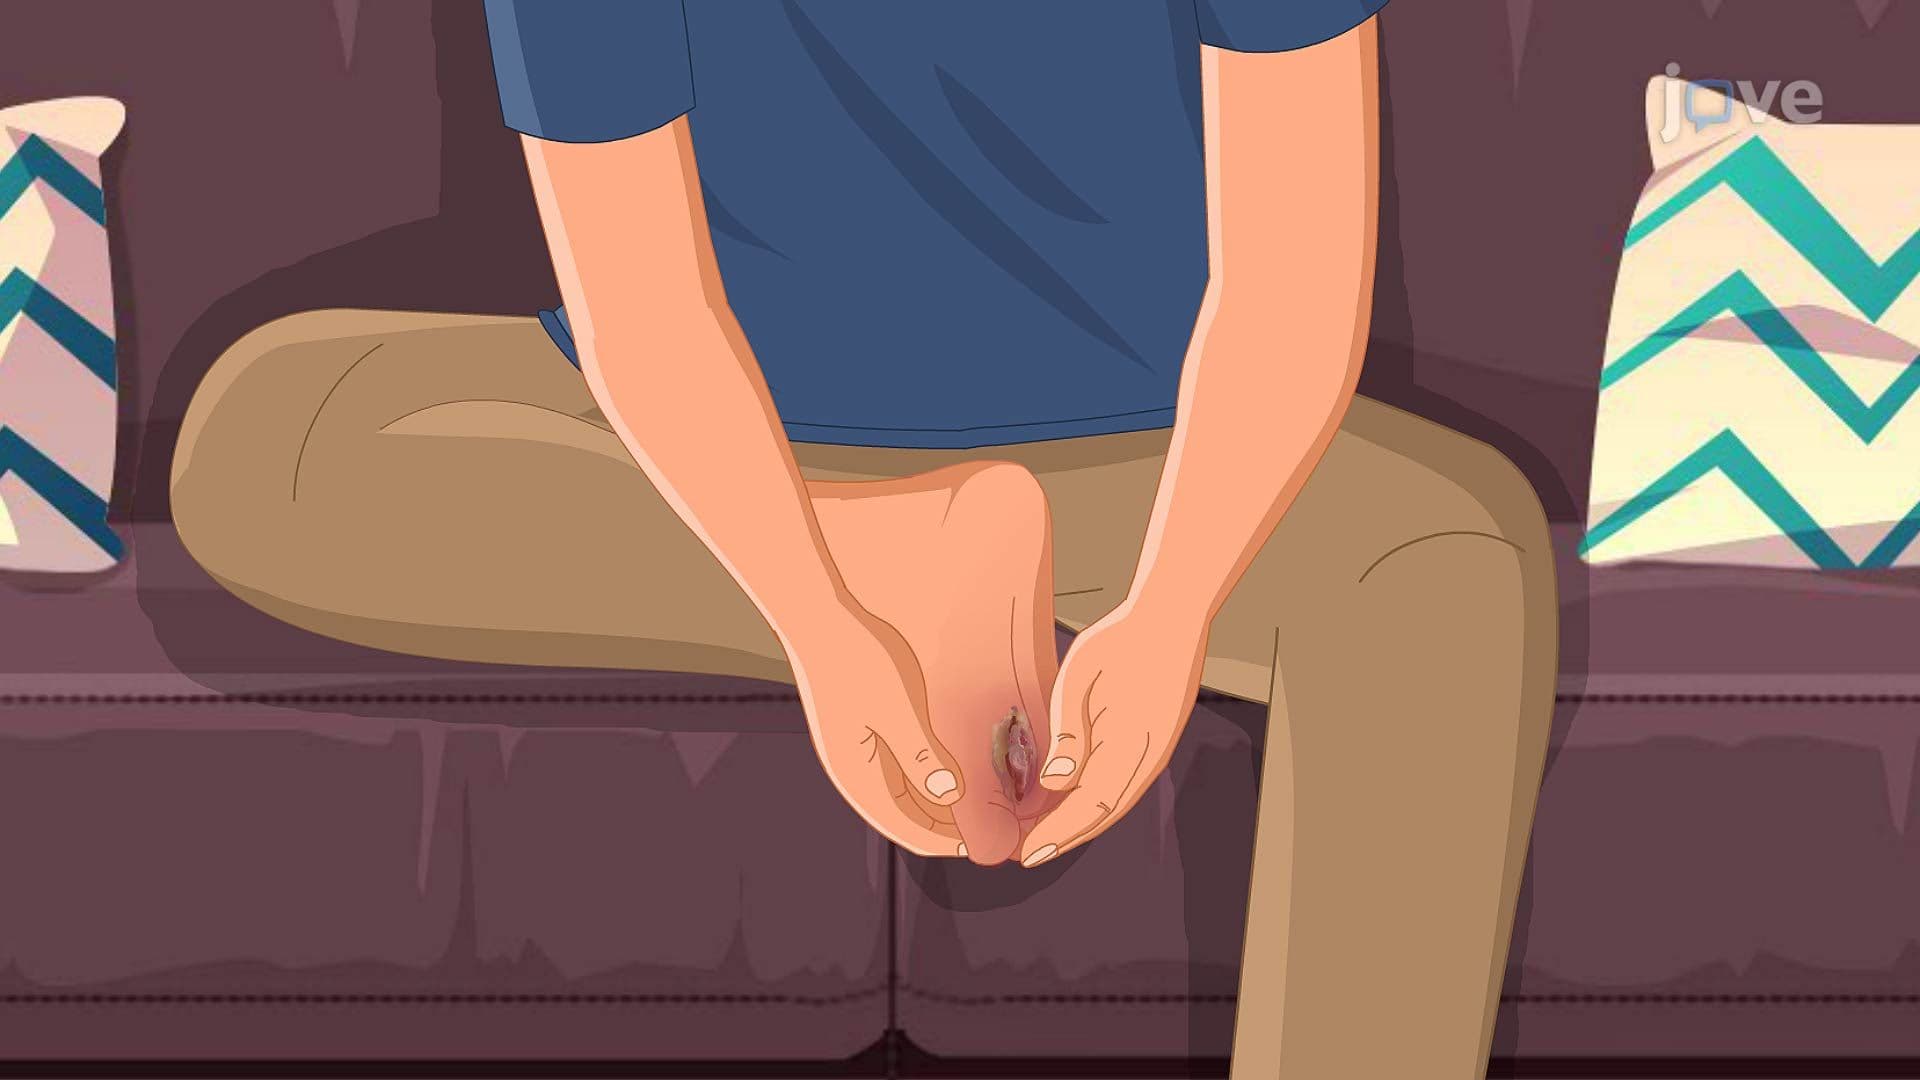
- Infections often arise from foot ulcerations, typically following trauma to a neuropathic foot in diabetic patients.
- Infection severity (mild, moderate, severe) dictates therapeutic strategies.
Purpose of the Study:
- To outline the classification and management of diabetic foot infections.
- To discuss appropriate antibacterial therapy selection based on infection characteristics and causative pathogens.
- To highlight the challenges in managing diabetic foot osteomyelitis and the role of surgical intervention.
Main Methods:
- Review of current literature and clinical guidelines for diabetic foot infections.
- Analysis of causative pathogens, differentiating between Gram-positive and polymicrobial infections.
- Evaluation of treatment approaches including antibiotic selection, surgical debridement, and duration of therapy.
Main Results:
- Mild to moderate infections are typically Gram-positive and treatable with narrow-spectrum antibiotics and debridement.
- Severe infections are often polymicrobial, necessitating broad-spectrum antibiotics, hospitalization, and comprehensive interventions.
- No single antibacterial regimen has demonstrated superiority; treatment should be guided by culture and sensitivity results.
Conclusions:
- Effective management of diabetic foot infections requires accurate diagnosis, appropriate antimicrobial selection, and timely surgical intervention.
- Addressing the increasing incidence of methicillin-resistant Staphylococcus aureus is critical.
- Duration of antibiotic therapy varies significantly, from weeks for soft tissue infections to over six weeks for osteomyelitis.
Related Concept Videos
 01:31
Diabetic Foot Ulcer
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
Antimicrobial Effectiveness
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care