Related Experiment Video
Updated: Jul 17, 2026
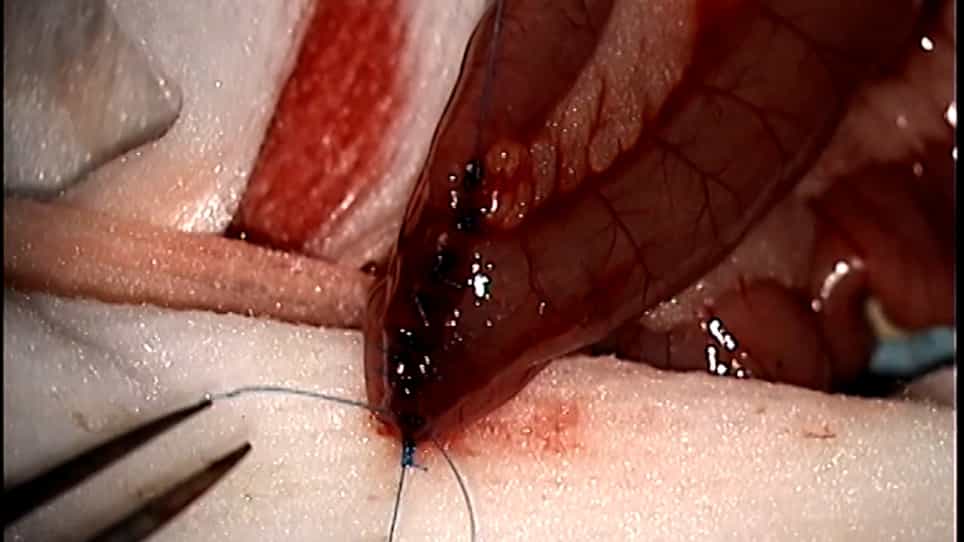

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Gastrojejunal anastomotic stricture after Roux-en-Y gastric bypass: ambulatory management with the Savary-Gilliard
1Departamento de Cirugía Digestiva, Pontificia Universidad Católica de Chile, Marcoleta 367, Santiago, Chile. aescalon@puc.cl

Background:
Roux-en-Y gastric bypass (RYGBP) is currently one of the most frequently performed procedures for the surgical treatment of morbid obesity. The success of this procedure's restrictive component requires a small gastrojejunostomy (GJ), which occasionally results in stenosis. The treatment of choice for this complication is balloon dilation. This study aimed to evaluate the feasibility and safety of ambulatory management for stenosis of the GJ using endoscopically guided Savary-Gilliard dilators.
Methods:
Between January 1998 and October 2003, 769 patients underwent RYGBP. The mean age of these patients was 38 +/- 12 years, and their mean body mass index (BMI) was 43 +/- 6 kg/m2. Of these 769 patients, 520 (68%) underwent open surgery and 249 (32%) underwent laparoscopic RYGBP. Patients suspected of GJ stenosis were referred for upper gastrointestinal endoscopy. Those who presented with stenosis were managed endoscopically with Savary-Gilliard dilators.
Results:
Stenosis at the GJ was confirmed in 53 patients (6.9%). A total of 71 dilations were performed for these patients, resulting in a mean of 1.3 dilations per patient. One dilation was needed for 41 patients (75.5%), two dilations for 9 patients (16.9%), three dilations for 3 patients (5.7%), and four dilations 1 patient (1.9%). The patients subjected to open RYGBP required a mean of 1.57 dilations, and those who had laparoscopic RYGBP required mean of 1.08 dilations. The mean time for the first dilation was 51 +/- 28 days after surgery (range, 20-178 days). All the dilations were performed in ambulatory settings. One patient (1.9%) was admitted after GJ dilation for pain. He was discharged without symptoms after 2 days with no need for invasive procedures.
Conclusions:
The management and treatment of GJ stenosis after RYGBP can be effectively accomplished in ambulatory settings using endoscopically guided Savary-Gilliard dilators, with good and safe results.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...