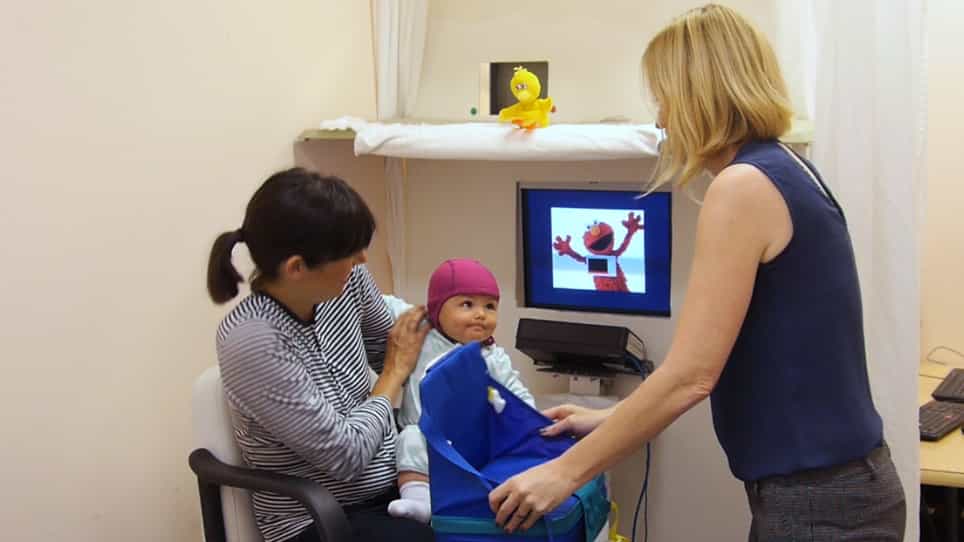
Related Experiment Video
Updated: Jul 17, 2026


Using an Automated Hirschberg Test App to Evaluate Ocular Alignment
Published on: March 24, 2020
Infant hyperopia: detection, distribution, changes and correlates-outcomes from the cambridge infant screening
Janette Atkinson1, Oliver Braddick, Marko Nardini
1Visual Development Unit, University College London, London, United Kingdom. j.atkinson@ucl.ac.uk

Insights
Infant refractive screening using photo/videorefraction detects hyperopia, improving visual outcomes with early correction. This screening may also identify developmental delays in infants.
Area of Science:
- Ophthalmology
- Developmental Pediatrics
Background:
- Population screening programs for infants aged 8-9 months were conducted to detect significant refractive errors.
- The sequelae of infant hyperopia and the impact of early partial spectacle correction on visual outcomes were examined.
Purpose of the Study:
- To evaluate the effectiveness of infant refractive screening programs.
- To investigate the association between infant hyperopia and developmental differences up to age 7 years.
- To assess the cost-effectiveness of infant refractive screening.
Main Methods:
- Two population screening programs involving orthoptic examination and isotropic photorefraction (with and without cycloplegia) were implemented.
- Hyperopic infants were followed up with visual and developmental measures, and a controlled trial of partial spectacle correction was conducted.
- Linked programs in six European countries assessed the costs of infant refractive screening.
Main Results:
- Photo/videorefraction identified significant hyperopia (approx. 5% prevalence) and manifest strabismus (0.3% at 9 months, 1.5-2.0% by school age).
- Infant hyperopia was linked to increased strabismus and poorer acuity by age 4, with early spectacle correction showing improved visual outcomes.
- Hyperopic children exhibited poorer visuoperceptual, cognitive, motor, and attention skills from ages 1-7, but not in early language development.
Conclusions:
- Photo/videorefraction is effective for infant refractive error screening, and early correction improves visual outcomes.
- Infant hyperopia is associated with mild delays in visuocognitive and visuomotor development.
- Infant refractive screening may identify potential visual, developmental, and learning difficulties.
Purpose:
To report on two population screening programs designed to detect significant refractive errors in 8308 8- to 9-month-old infants, examine the sequelae of infant hyperopia, and test whether early partial spectacle correction improved visual outcome (strabismus and acuity). The second program also examined whether infant hyperopia was associated with developmental differences across various domains such as language, cognition, attention, and visuomotor competences up to age 7 years. Linked programs in six European countries assessed costs of infant refractive screening.
Method:
In the first program, screening included an orthoptic examination and isotropic photorefraction, with cycloplegia. In the second program we carried out the same screening procedure without cycloplegia. Hyperopic infants (> or = +4 D) were followed up alongside an emmetropic control group, with visual and developmental measures up to age 7 years, and entered a controlled trial of partial spectacle correction.
Results:
The second program showed that accommodative lag during photorefraction with a target at 75 cm (focus > or = +1.5 D) was a marker for significant hyperopia. In each program, prevalence of significant hyperopia at 9 to 11 months was around 5%; manifest strabismus was 0.3% at 9 months and 1.5 to 2.0% by school age. Infant hyperopia was associated with increased strabismus and poor acuity at 4 years. Spectacle wear by infant hyperopes produced better visual outcome than in uncorrected infants, although an improvement in strabismus was found in the first program only. The corrections did not affect emmetropization to 3.5 years; however, both corrected and uncorrected groups remained more hyperopic than controls in the preschool years. The hyperopic group showed poorer overall performance than controls between 1 and 7 years on visuoperceptual, cognitive, motor, and attention tests, but showed no consistent differences in early language or phonological awareness. Relative cost estimates suggest that refractive screening programs can detect visual problems in infancy at lower overall cost than surveillance in primary care.
Conclusions:
Photo/videorefraction can successfully screen infants for refractive errors, with visual outcomes improved through early refractive correction. Infant hyperopia is associated with mild delays across many aspects of visuocognitive and visuomotor development. These studies raise the possibility that infant refractive screening can identify not only visual problems, but also potential developmental and learning difficulties.