Related Experiment Video
Updated: Jul 16, 2026
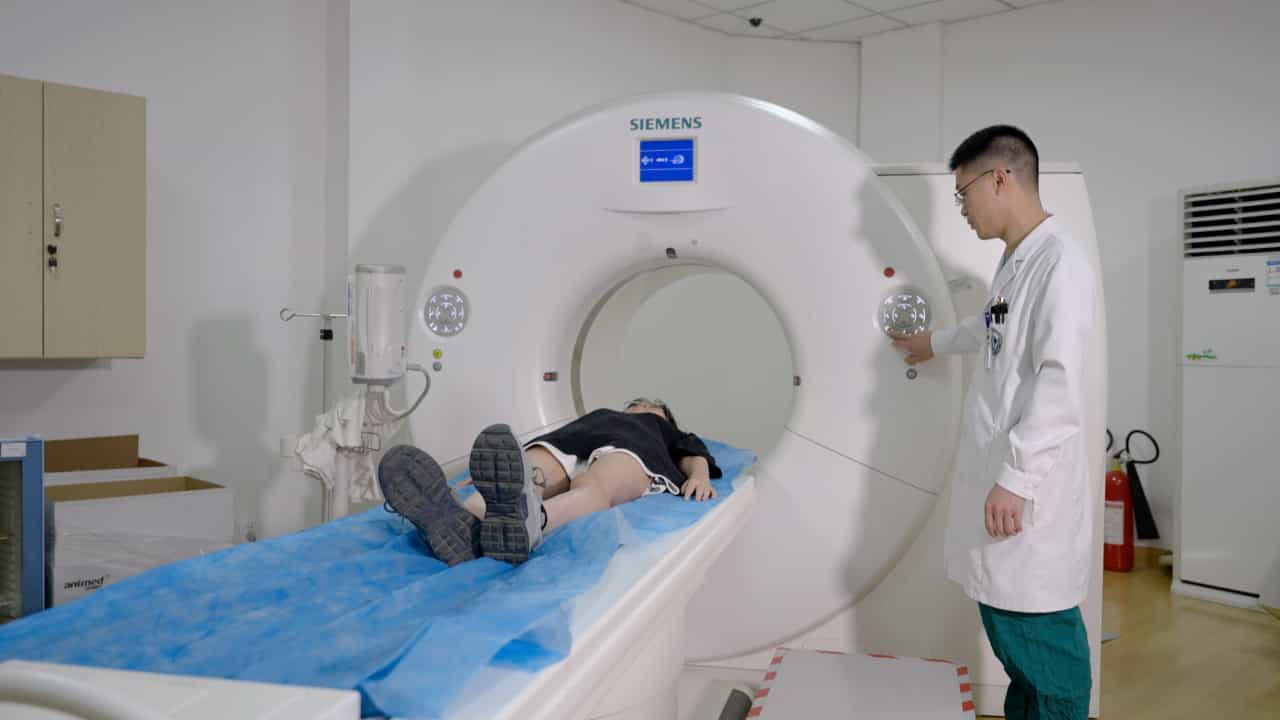

Computer-Aided Three-Dimensional Visualization in the Treatment of Locally Advanced Thyroid Cancer
Published on: June 9, 2023
Should 'low-risk' thyroid cancer patients with residual thyroglobulin be re-treated with iodine 131?
Elif Hindié1, Paolo Zanotti-Fregonara, Françoise Duron
1Department of Nuclear Medicine, Hôpital Saint-Antoine, Assistance Publique Hopitaux de Paris, Paris, France. elif.hindie@sls.aphp.fr

Objective:
The American consensus statement on patients with low-risk thyroid cancer, published in 2003, suggests repeat (131)I therapy if the thyroglobulin value is elevated at first follow-up. We evaluated this strategy in our practice.
Methods:
Among 407 patients with thyroid cancer who had total thyroidectomy and (131)I ablation between January 2000 and December 2003, 12 patients with stage I thyroid cancer (any tumour (T), any node (N), metastasis (M)0 if < 45 years or T1, N0, M0 if > 45 years), were re-treated on the basis of their thyroglobulin level at first follow-up. Mean patient age was 32.8 years. None of them had a T4 tumour. Thyroglobulin levels after thyroid hormone withdrawal 'off-T4' ranged between 4.5 and 251 ng/ml (median 8). One to four courses of 3.7 GBq (131)I were given.
Results:
Three patients had a negative (131)I therapy scan and an uneventful course. Two patients had slight residual uptake only in the thyroid bed and negative ultrasound examination. Four patients had isolated (131)I uptake in the mediastinal region. No abnormalities were found on complementary mediastinal imaging. This finding was interpreted as benign (131)I thymic uptake. The last three patients also had mediastinal thymic uptake associated with a slight thyroid bed uptake. One patient had a gradual increase in the thyroglobulin level, and underwent resection of nonfunctioning neck lymph nodes. Thyroglobulin levels declined in all other patients.
Conclusions:
No distant lesions were found in a group of young 'low-risk' thyroid cancer patients given empirical (131)I therapy for residual thyroglobulin. When blind (131)I therapy shows no uptake, or uptake limited to the thymus, (131)I therapy should not be repeated. The authors also briefly discuss the hypothesis that enhanced thymus might be a source of benign thyroglobulin secretion.
Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:27
Goiter
 01:30
Radiological Investigation I: X-ray and CT
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology