Related Experiment Video
Updated: Jul 16, 2026

Micro-Colony Forming Unit Assay for Efficacy Evaluation of Vaccines Against Tuberculosis
Published on: July 28, 2023
[Application and problems of quantiFERON TB-2G for tuberculosis control programs--(2) clinical use of quantiFERON
1Division of Respiratory Disease, National Hospital Organization Tokyo National Hospital, 3-1-1, Takeoka, Kiyose-shi, Tokyo 204-8585 Japan. kawabe-in@tokyo-hosp.jp

Background:
QuantiFERON TB-2nd Generation (QFT) is an accurate tool for detecting tuberculosis infection regardless of past history of BCG vaccination. In Japan, QFT test was recognized for diagnostic tool on April 2005, and adopted officially on January 2006. Tuberculosis Society issued Guideline for using QFT-2G on May 2006.
Purpose:
This article describe the usefulness and remarks in clinical use on diagnosis and system for detection of tuberculosis infection among staff in NHO Tokyo Hospital that has 100 beds for tuberculosis.
Method:
(1) QFT test for 403 definite diagnosed tuberculosis patient before tuberculosis treatment or within 7 days chemotherapy in NHO Tokyo Hospital. Seventy-four patients have immunosuppressive diseases such as diabetes mellitus, malignant disease, using corticosteroid or immunosuppressor and HIV+ including overlap diseases. QFT result was analyzed by immunosuppressive diseases and by age for 329 patients who have no immunosuppressive diseases. (2) For control of tuberculosis infection of staff, QFT test is used in 3 situation. One is baseline QFT for staff who are shifted to tuberculosis ward from non-tuberculosis ward and new employee, 2nd is following up for staff who work at tuberculosis ward, and 3rd is contact investigation for staff who work at non-tuberculosis ward. Tuberculin skin testing and baseline QFT were done for 92 staff on April 2006, 2 were shifted to tuberculosis ward from non-tuberculosis ward and 90 were new employee.
Result:
(1) Among 403 definite diagnosed tuberculosis patient before tuberculosis treatment or within 7 days chemotherapy, QFT positive rate was 78.7%. Among 74 patients who have immunosuppressive diseases such as diabetes mellitus, malignant disease, using corticosteroid or immunosuppressor and HIV+ including overlap diseases, QFT positive rate was 58-70%. Among 329 patients who have no immunosuppressive diseases, QFT positive rate was 88-89% in thirties and forties, 69% in sixties and 63% in nineties. QFT-2G test for 134 previously treated tuberculosis cases who are not suffered from active tuberculosis, 49 cases (37%) were positive, 27 cases (20%) were intermediate and 58 cases (43%) were negative. Instructive three cases were reviewed. Suspicion of tuberculosis relapse with QFT negative case was M. avium-intracellulare disease. Suspicion of M. avium-intracellulare disease rather than tuberculosis by X-ray and CT with QFT positive case was tuberculosis. A case with small nodule on CT with QFT positive was adenocarcinoma. (2) Tuberculin Skin Testing and baseline QFT for 92 staff, 4 were QFT positive. Compared with Tuberculin Skin Testing more than 29 mm in erythema, QFT positive rate was 9% and more than 9 mm in induration, QFT positive rate was 7%. By following up QFT test for staff working at tuberculosis ward, 2 staff, one nurse and one helper, were diagnosed tuberculosis infection. As to contact investigation, one nurse was diagnosed tuberculosis infection.
Conclusion:
Although QFT is a very excellent tool for detecting tuberculosis infection, on clinical diagnosis, it is important to mind that QFT depends on clinical condition especially immunosuppressive diseases, aging and past infection. We cannot diagnose or exclude active tuberculosis by QFT result. This is a useful assistant tool on clinical diagnosis.
Related Concept Videos
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 02:57
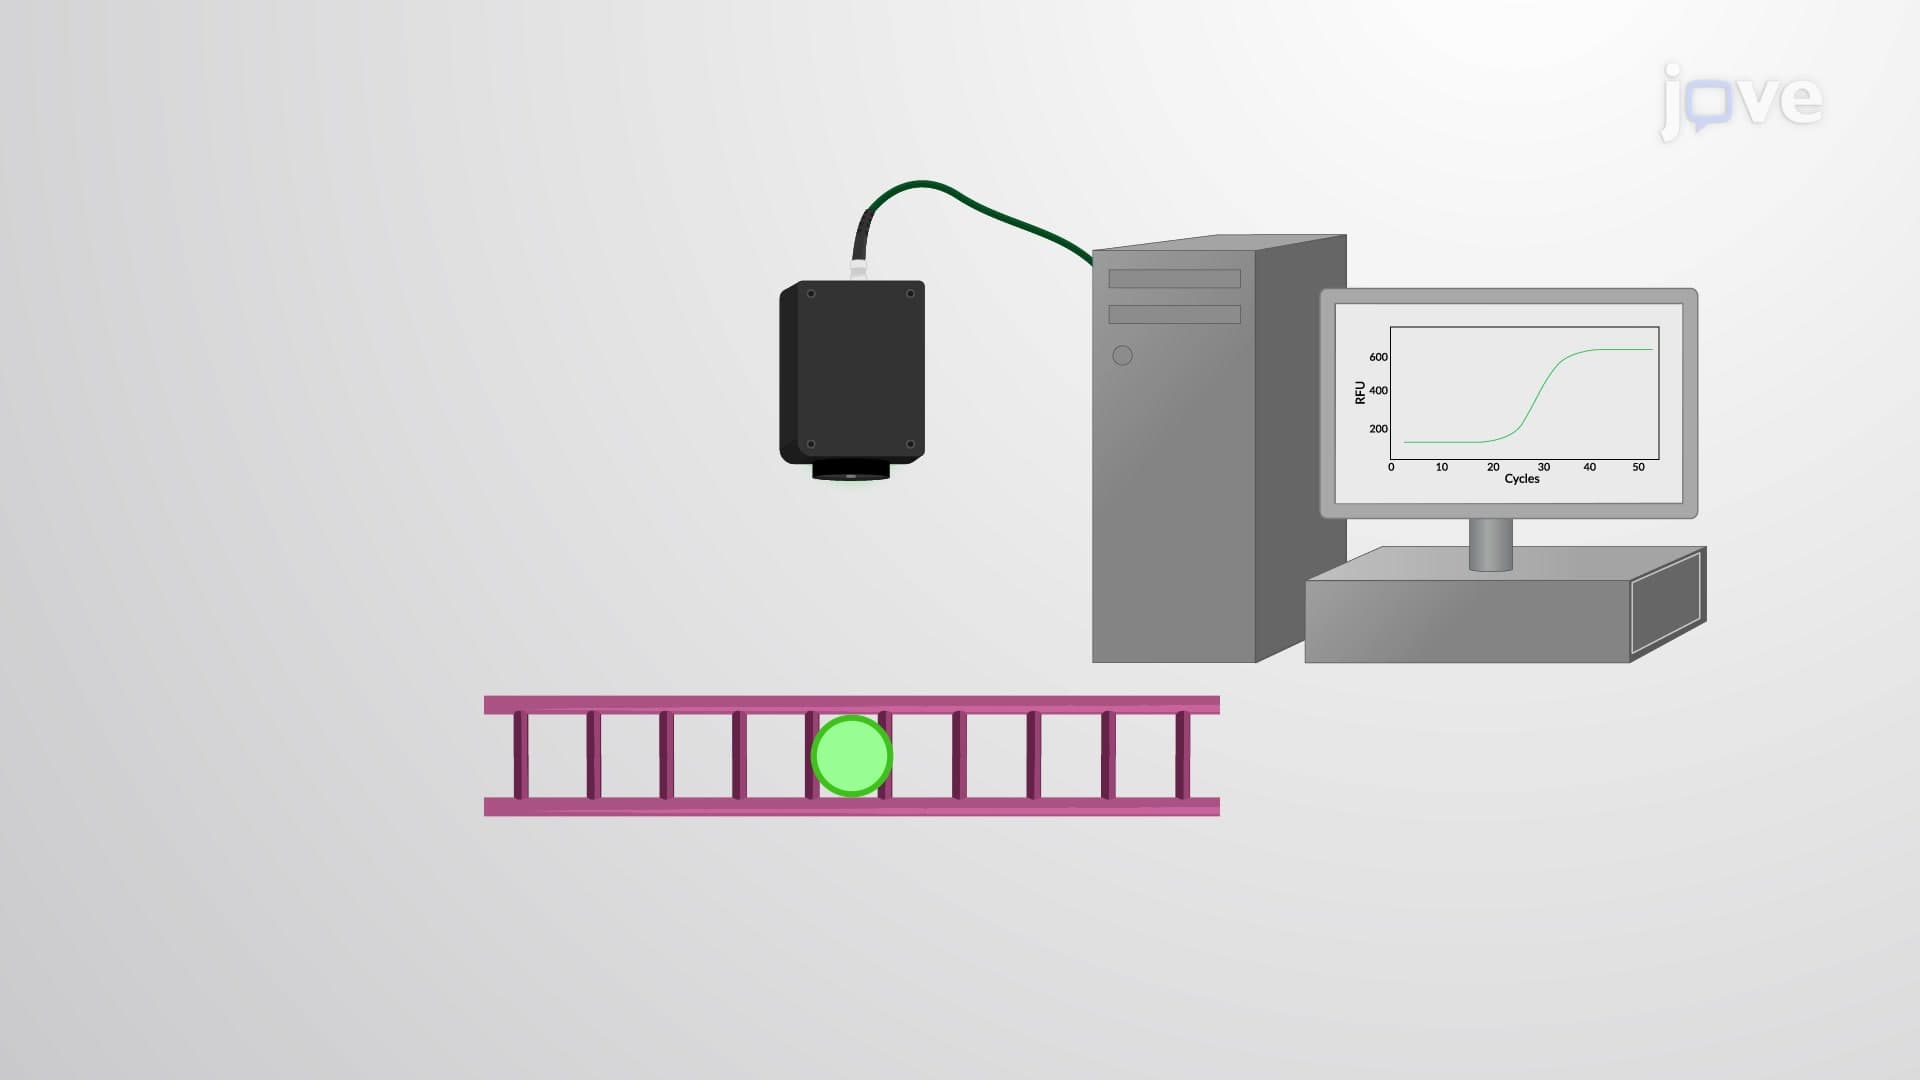
Real Time RT-PCR
The real-time quantification of the number of amplified products is...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...