Related Experiment Video
Updated: Jul 16, 2026
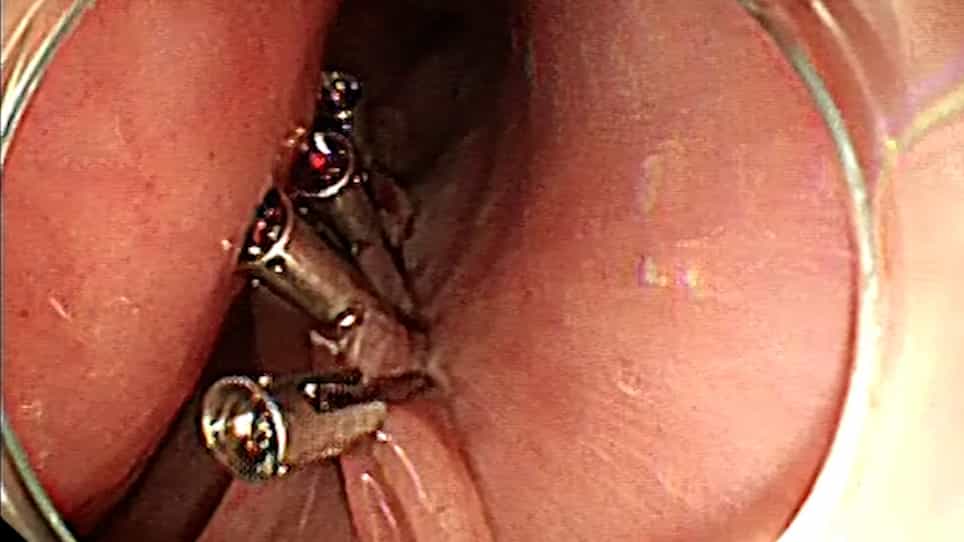

Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Maintenance therapy for erosive esophagitis in children after healing by omeprazole: is it advisable?
Gabriella Boccia1, Francesco Manguso, Erasmo Miele
1Department of Pediatrics, University Frederico II, Naples, Italy.

Insights
Acid-suppressive therapy for pediatric gastroesophageal reflux disease (GERD) showed low relapse rates. Maintenance therapy with omeprazole or ranitidine was not superior to no treatment after healing reflux esophagitis.
Area of Science:
- Pediatric Gastroenterology
- Gastrointestinal Motility Disorders
- Pharmacology
Background:
- Gastroesophageal reflux disease (GERD) is common in children.
- Reflux esophagitis requires effective treatment and maintenance strategies.
- Acid-suppressive therapy is a cornerstone in managing GERD.
Purpose of the Study:
- To assess the efficacy of maintenance therapy for pediatric GERD after healing reflux esophagitis.
- To compare omeprazole, ranitidine, and no treatment for maintenance therapy.
- To evaluate long-term relapse and symptom recurrence rates.
Main Methods:
- 48 children with erosive reflux esophagitis received omeprazole for healing.
- Remission patients were randomized to omeprazole, ranitidine, or no treatment for 6 months.
- Endoscopic, histological, and symptomatic scores were assessed, with long-term follow-up.
Main Results:
- 94% of patients healed and entered the maintenance phase.
- No significant differences in scores were observed between maintenance groups (omeprazole, ranitidine, none).
- A low relapse rate (1 patient) and mild long-term symptoms were reported.
Conclusions:
- Pediatric GERD patients exhibit low relapse rates after healing with omeprazole.
- Maintenance therapy efficacy was similar across omeprazole, ranitidine, and no treatment groups.
- Long-term outcomes suggest favorable prognosis irrespective of maintenance strategy.
Objectives:
To evaluate the efficacy of acid-suppressive maintenance therapy for gastroesophageal reflux disease (GERD) in children, after the healing of reflux esophagitis.
Methods:
Forty-eight children (median age 105 months, range 32-170) with erosive reflux esophagitis were initially treated with omeprazole 1.4 mg/kg/day for 3 months. Patients in endoscopic remission were assigned in a randomized, blinded manner by means of a computer-generated list to three groups of 6-month maintenance treatment: group A (omeprazole at half the starting dose, once daily before breakfast), group B (ranitidine 10 mg/kg/day, divided in two doses), and group C (no treatment). Endoscopic, histological, and symptomatic scores were evaluated at: T0, enrollment; T1, assessment for remission at 3 months after enrollment (healing phase); T2, assessment for effective maintenance at 12 months after T0 (3 months after the completion of the maintenance phase). Relapse was defined as the recurrence of macroscopic esophageal lesions. After the completion of the maintenance phase, patients without macroscopic esophagitis relapse were followed up for GERD symptoms for a further period of 30 months.
Results:
Of 48 initially treated patients, 46 (94%) healed and entered the maintenance study. For all patients, in comparison to T0, the histological, endoscopic, and symptomatic scores were significantly reduced both at T1 and T2 (P<0.0001, for each). No significant difference was found in these three scores, comparing group A, B, and C at T1 and T2. A relapse occurred in one patient only, who presented with macroscopic esophageal lesions at T2. Three months after the completion of the maintenance phase, 12 (26%) patients complained of symptoms sufficiently mild to discontinue GERD therapy, excluding the patient who showed macroscopic esophagitis relapse. Three of 44 (6.8%) patients reported very mild GERD symptoms within a period of 30 months after maintenance discontinuation.
Conclusions:
Our pediatric population showed a low rate of erosive esophagitis relapse and GERD symptom recurrence long term after healing with omeprazole, irrespective of the maintenance therapy.
Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:13
Acid Suppressive Drugs for Peptic Ulcer Disease: Proton Pump Inhibitors
Gastric acid, a potent cocktail of hydrogen and chloride ions, is produced in specialized parietal cells within the...
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...