Related Experiment Video
Updated: Jul 16, 2026

Flow Cytometry-Based Quantification and Analysis of Myocardial B-Cells
Published on: August 17, 2022
[Anti-beta 1 adrenoreceptor antibody is frequently elevated in patients with muscular dystrophy]
Tsuyoshi Matsumura1, Taku Yoshio, Keiji Yamamoto
1Department of Neurology, National Hospital Organization Toneyama National Hospital.

Insights
Anti-beta 1 adrenoreceptor antibody (ARAb) is present in progressive muscular dystrophy (PMD) patients, suggesting immune system involvement in cardiac impairment. ARAb elevation correlated with cardiac dysfunction in PMD and dilated cardiomyopathy (DCM).
Area of Science:
- Immunology
- Cardiology
- Genetics
Context:
- Dilated cardiomyopathy (DCM) is associated with various autoantibodies, including anti-beta 1 adrenoreceptor antibody (ARAb).
- Progressive muscular dystrophy (PMD) patients experience significant cardiac dysfunction, with variable severity suggesting potential modifier factors.
- The role of immune system in cardiac impairment in PMD remains unclear.
Purpose:
- To measure anti-beta 1 adrenoreceptor antibody (ARAb) titers in patients with progressive muscular dystrophy (PMD) and dilated cardiomyopathy (DCM).
- To investigate the potential role of immune function, specifically ARAb, in cardiac impairment associated with PMD.
- To explore the correlation between ARAb levels and cardiac function parameters in PMD and DCM patients.
Summary:
- Anti-beta 1 adrenoreceptor antibody (ARAb) titers were elevated in 30.1% of PMD patients and 72.7% of DCM patients.
- In PMD patients with symptomatic cardiac failure, 75% had elevated ARAb.
- ARAb levels showed weak correlations with fractional shortening, brain natriuretic peptide, noradrenalin, and premature ventricular contractions severity. Four PMD patients who developed cardiac failure showed increased ARAb.
- Duchenne muscular dystrophy (DMD) patients on beta-blocker therapy showed decreased ARAb levels.
Impact:
- This study highlights the presence of autoantibodies in PMD, similar to DCM, suggesting the immune system's role in cardiac dysfunction.
- Findings emphasize the need for further investigation into immune system involvement to understand cardiac dysfunction mechanisms in PMD.
- Results may inform refined cardiac treatment strategies for PMD patients, potentially including immunomodulatory approaches.
Abstract:
Various autoantibodies had been detected in patients with dilated cardiomyopathy (DCM). Among them, anti-beta 1 adrenoreceptor antibody (ARAb) had been proven to act as agonist on beta 1 adrenoreceptor and cause DCM. Cardiomyopathy is also serious problem in progressive muscular dystrophy (PMD). Because cardiac dysfunction is quite variable even in siblings sharing identical mutations, it is highly possible that there are some modifier factors. Thus, we measured ARAb in 93 patients with PMD and 11 patients with DCM to clarify immune function for cardiac impairment of PMD. The titer was abnormally elevated in 30.1% of PMD, 72.7% of DCM and 75.0% (9/12) of PMD patients with symptomatic cardiac failure. ARAb was weakly correlated to fractional shortening, brain natriuretic peptide, noradrenalin and severity of premature ventricular contractions (Lown grade). During the study period, four patients developed cardiac failure and ARAb was increased in all these patients. In DMD, although the patients receiving both beta blocker and angiotensin converting enzyme inhibitor showed worst cardiac function, the titers were rather low compared to patients with angiotensin converting enzyme inhibitor alone. Four of five patients initiating beta blocker showed decrease of ARAb. Autoantibodies for myocardium actually exist in PMD in certain ratio as is the case with DCM. It is highly possible that immune system plays some role in cardiac impairment even in PMD. We should pay enough attention to immune system to elucidate the mechanism of cardiac dysfunction and refine strategy of cardiac treatments.
Related Concept Videos
 01:26
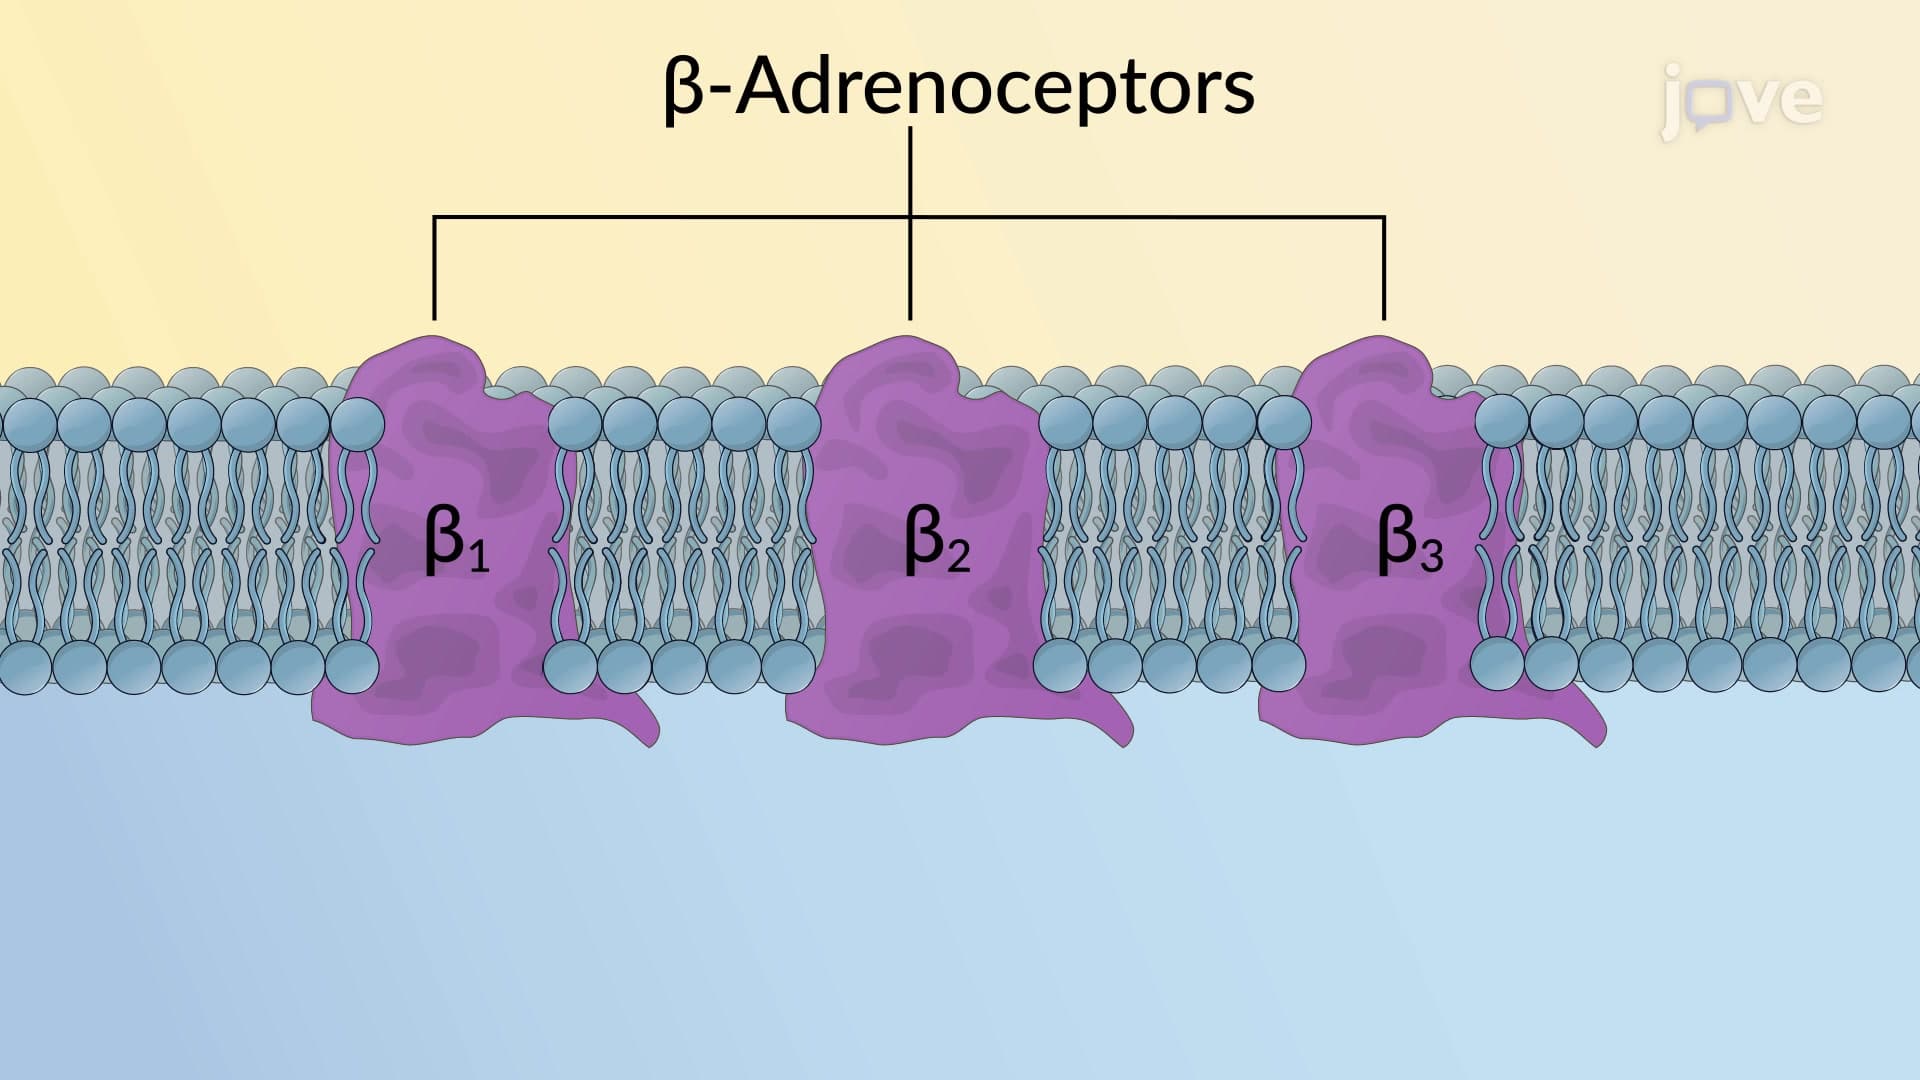
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:21
Satellite Stem Cells and Muscular Dystrophy
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:27
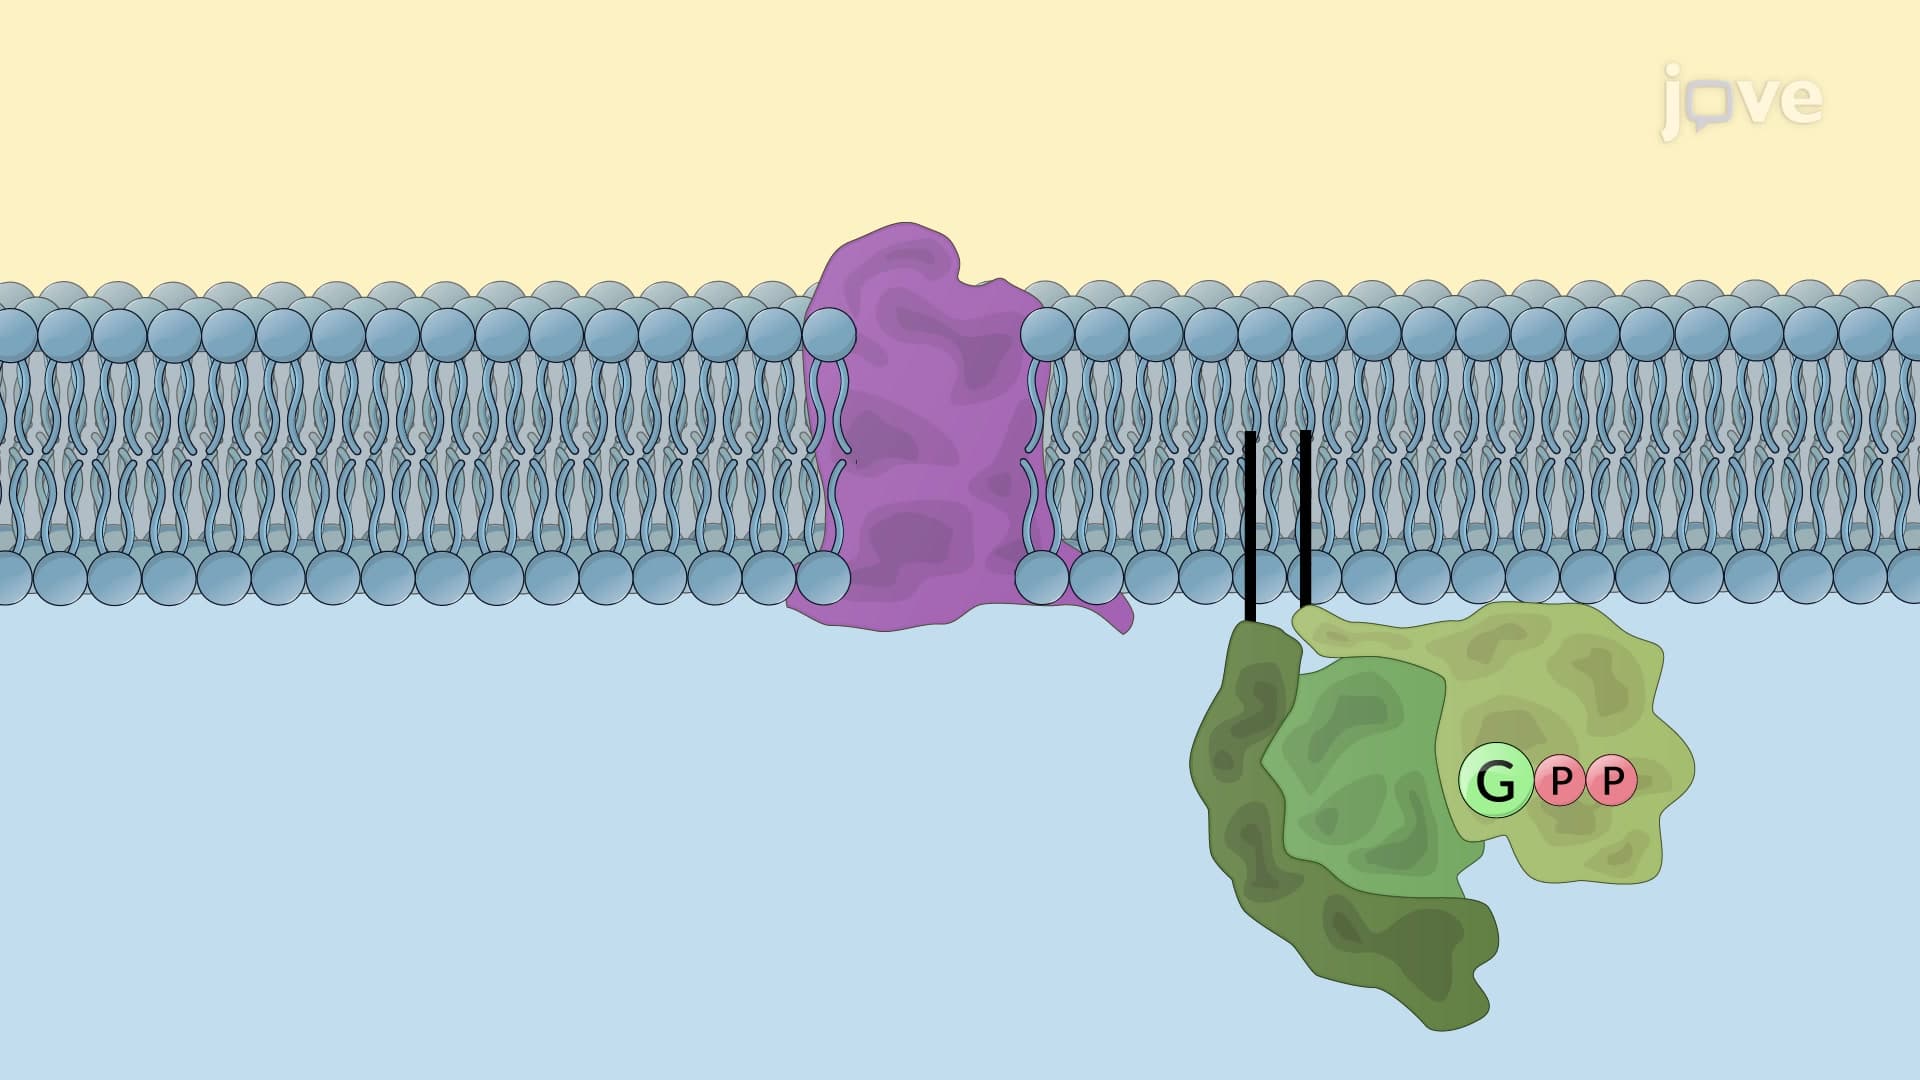
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:22
Myasthenia Gravis ll: Pathophysiology