Related Experiment Video
Updated: Jul 16, 2026


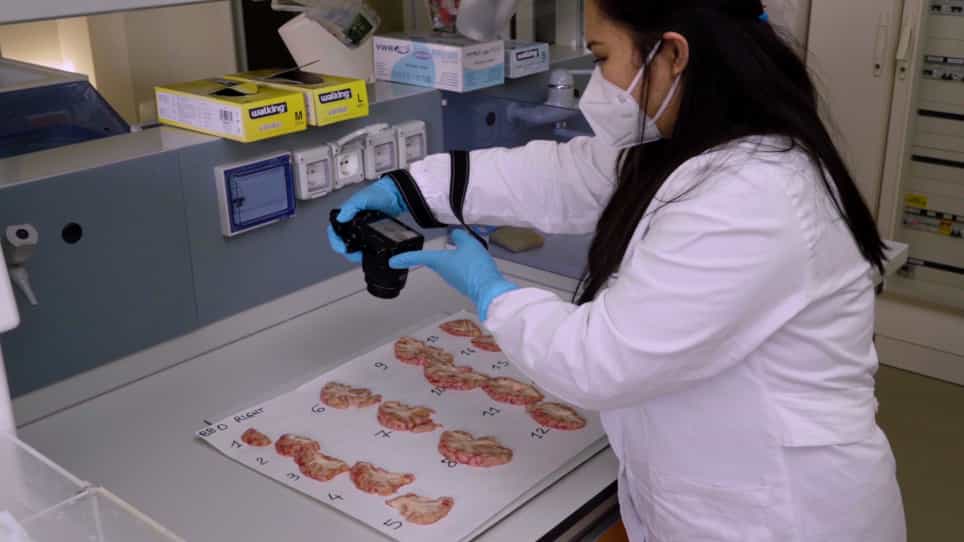
Symmetric Bihemispheric Postmortem Brain Cutting to Study Healthy and Pathological Brain Conditions in Humans
Published on: December 18, 2016
Neuropathological evaluation of mixed dementia
1Institute of Clinical Neurobiology, 18, Kenyongasse, A-1070 Vienna, Austria. kurt.jellinger@univie.ac.at

Abstract:
Mixed dementia (MD) refers to a combination of definite Alzheimer disease (AD) and vascular encephalopathy, but the distinction between both disorders is controversial. For the diagnosis of MD the clinical/neuroimaging criteria of possible AD plus cerebrovascular disease (CVD) as separate entities are used, but causal relations between vascular brain lesions and dementia are unclear. We proposed the combination of autopsy-proven AD with multiple vascular or ischemic lesions with about 30-50 ml of infarcted/damaged brain tissue. The population-based prevalence of MD is unknown. In retrospective and prospective autopsy studies, it ranges from 2 to 58% with reasonable means of 6-12%. In a consecutive autopsy series of 1500 demented elderly subjects, 830 of which with clinically probable AD, in Vienna, Austria, 41.5 to 52.0% showed "pure" AD, 7% atypical AD, 16-20% AD plus cerebrovascular lesions, and 9% AD plus Lewy body pathology; MD was diagnosed in 4.6 and 2.4%, and "pure" vascular dementia (VaD) in 11 and 2.0%, respectively, while 16.3/6.1% were other dementing disorders, and 1% showed no specific pathology. Like the MRC-CFAS and other studies, this indicates frequent coexistence of AD with multiple cerebrovascular lesions in cognitively impaired patients. In both AD and VaD, vascular lesions frequently involved subcortical regions (basal ganglia, thalamus, hippocampus, and white matter) or were multiple microinfarcts, whereas in MD, large/hemispheral infarcts and multiple microinfarcts were more frequent, suggesting different pathogenic mechanisms. In early/mild AD, critically located small vascular lesions may induce/promote cognitive decline, but in full-blown AD they appear of minor importance. Discussion of the major pathogenic factors inducing AD, VaD and MD suggests synergistic relations between these disorders. However, currently available morphological criteria for AD and VaD are of limited value for the diagnosis of MD and generally accepted and validated histopathological criteria for the diagnosis of VaD and MD are currently not available. Therefore, more distinct and critically evaluated clinico-pathological criteria are warranted.
Insights
Mixed dementia, combining Alzheimer disease and vascular issues, presents diagnostic challenges. Autopsy studies reveal frequent co-occurrence, highlighting the need for better diagnostic criteria for mixed dementia.
Area of Science:
- Neurology
- Pathology
- Gerontology
Background:
- Mixed dementia (MD) involves co-occurring Alzheimer disease (AD) and vascular encephalopathy, with controversial diagnostic distinctions.
- Current criteria for MD use clinical/neuroimaging findings of AD and cerebrovascular disease (CVD), but causal links remain unclear.
- Proposed diagnostic criteria for MD combine autopsy-proven AD with significant vascular or ischemic brain lesions.
Purpose of the Study:
- To investigate the prevalence and pathological characteristics of mixed dementia (MD).
- To evaluate the coexistence of Alzheimer disease (AD) and cerebrovascular lesions in elderly demented subjects.
- To discuss the pathogenic factors and diagnostic limitations in differentiating AD, vascular dementia (VaD), and MD.
Main Methods:
- Retrospective and prospective autopsy studies were conducted on demented elderly subjects.
- Analysis included a series of 1500 demented individuals, with 830 having clinically probable AD.
- Histopathological examination assessed AD, vascular lesions, and other dementing pathologies.
Main Results:
- Mixed dementia (MD) prevalence in autopsy studies ranged from 2% to 58% (mean 6-12%).
- In a Vienna series, MD was diagnosed in 2.4-4.6% of cases, while pure AD was 41.5-52.0% and pure VaD was 2.0-11%.
- Vascular lesions were common in AD and VaD (subcortical/microinfarcts), but large/hemispheral infarcts were more frequent in MD, suggesting distinct pathogenetic mechanisms.
Conclusions:
- Alzheimer disease (AD) and cerebrovascular lesions frequently coexist in cognitively impaired patients.
- Distinct pathological patterns in AD, VaD, and MD suggest different underlying pathogenic mechanisms.
- Current clinico-pathological criteria for diagnosing VaD and MD are insufficient, necessitating development of validated histopathological criteria.

Related Concept Videos
 01:22
Dementia l: Introduction
 01:30
Dementia
The progression of dementia is generally gradual.
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:23
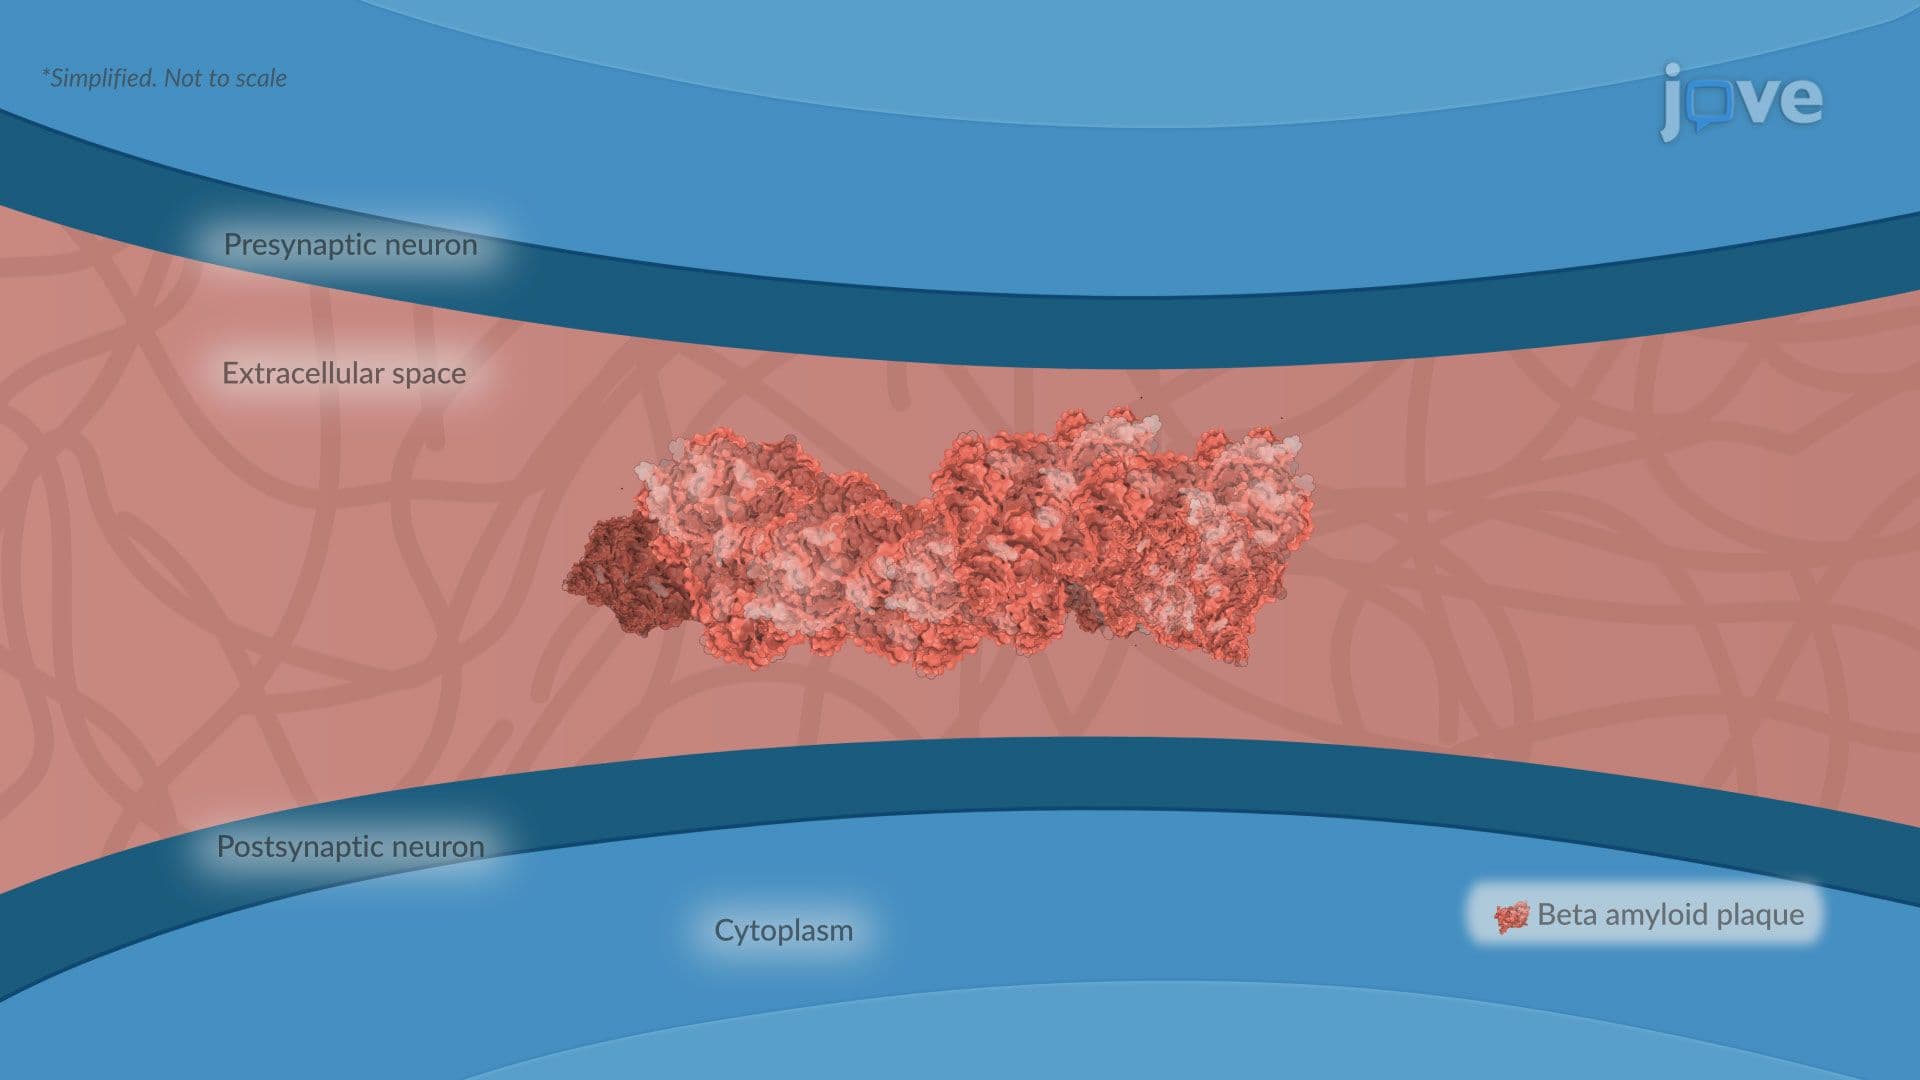
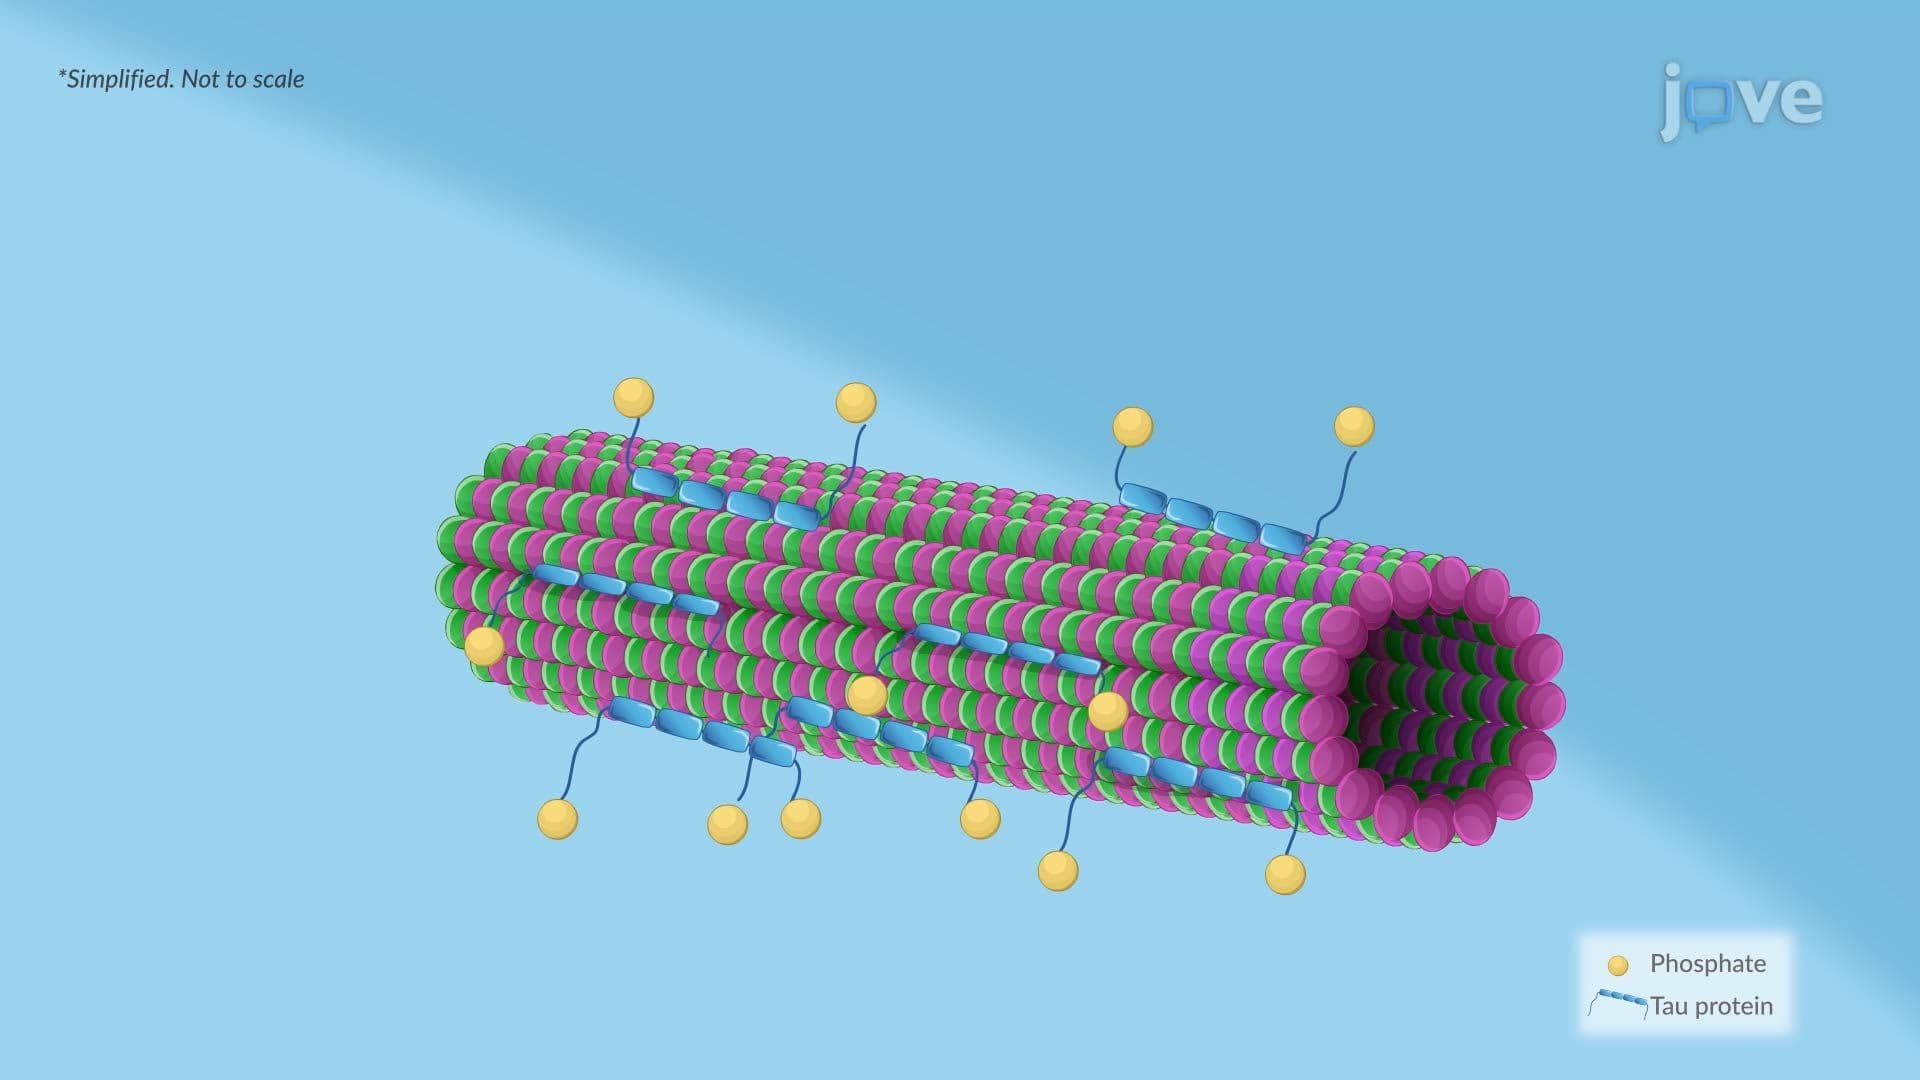
Alzheimer Disease ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:37
Neural Regulation