Pulmonary alveolar proteinosis in extremis: the case for aggressive whole lung lavage with extracorporeal membrane

Alan D L Sihoe1, Vivian M W Ng, Raymond W T Liu

  • 1Division of Cardiothoracic Surgery, The University of Hong Kong, Grantham Hospital, Hong Kong SAR, China.

Related Concept Videos

Acute Respiratory Failure-V01:29

Acute Respiratory Failure-V

The treatment for acute respiratory failure varies based on factors like the underlying cause, overall health, and severity. A collaborative healthcare team is essential for early detection, often through arterial blood gas analysis. Identifying the cause is the primary goal, with treatment strategies adjusted for ventilation/perfusion (V/Q) mismatch, shunting, or diffusion impairment.
Ensure that patients are monitored continuously for their response to therapy, including changes in...
Pulmonary Edema II: Pathophysiology01:18

Pulmonary Edema II: Pathophysiology

Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...
Pneumonia IV: Management01:28

Pneumonia IV: Management

The treatment of pneumonia varies based on its severity and the causative pathogen. Here is a structured approach to managing pneumonia, integrating pharmaceutical and supportive care strategies.
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
Acute Respiratory Failure-III01:30

Acute Respiratory Failure-III

Hypercapnic respiratory failure, also known as Type 2 or ventilatory respiratory failure, is a severe condition characterized by the body's inability to effectively remove carbon dioxide (CO2) from the bloodstream. It leads to an arterial CO2 pressure (PaCO2) exceeding 45 mmHg and a blood pH above 7.35. This situation indicates that the body's ventilatory demand, or the ventilation needed to maintain normal PaCO2 levels, surpasses its supply or the maximum gas flow achievable without causing...
Chronic Obstructive Pulmonary Disease II: Emphysema01:23

Chronic Obstructive Pulmonary Disease II: Emphysema

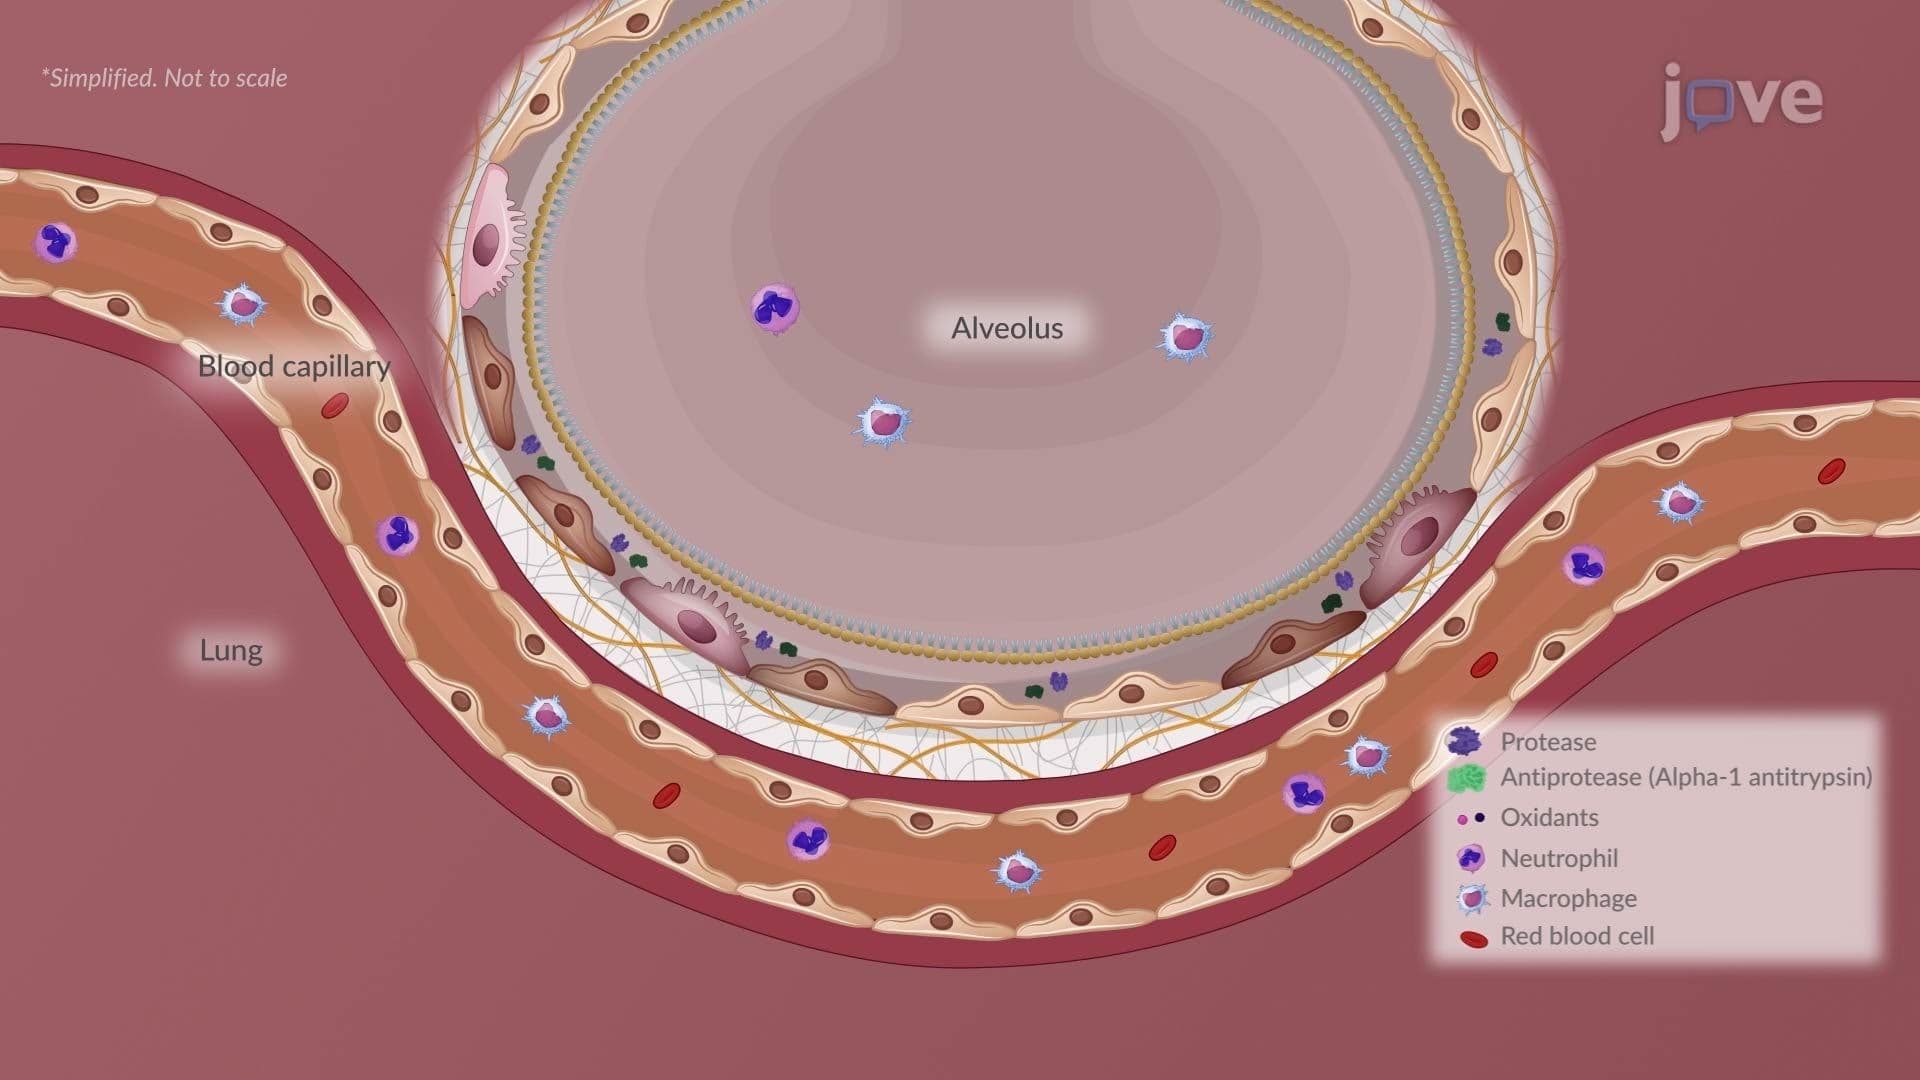
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
Pneumothorax II: Pathophysiology01:08

Pneumothorax II: Pathophysiology

Pneumothorax means the presence of air in the pleural space — the thin potential gap between the visceral and parietal pleura. This condition disrupts the normal pressure balance that keeps the lungs inflated, leading to partial or complete collapse of the affected lung.Normal physiologyUnder normal conditions, the pleural space maintains a slightly negative intrapleural pressure, which keeps the lungs expanded against the chest wall. This negative pressure creates a delicate balance between...