Related Experiment Video
Updated: Jul 16, 2026


Hyperinsulinemic-euglycemic Clamps in Conscious, Unrestrained Mice
Published on: November 16, 2011
Reversal of defective glucagon responses to hypoglycemia in insulin-dependent autoimmune diabetic BB rats
Huarong Zhou1, Tao Zhang, Elizabeth Oseid
1Pacific Northwest Research Institute, 720 Broadway, Seattle, WA 98122, USA.

The intraislet insulin hypothesis has been proposed to explain absent glucagon responses to hypoglycemia. Recently we directly confirmed this hypothesis by restoring glucagon secretion via provision of a pancreatic artery insulin infusion, which was switched off at the time of hypoglycemia in Wistar rats made diabetic by streptozotocin. The current study examined this hypothesis in a model of spontaneous, autoimmune diabetes, the insulin-dependent diabetic BB rat. The insulin switch-off signal restored the defective glucagon responses to hypoglycemia. However, the magnitude of the restored response was markedly less than that observed in control nondiabetic BB rats (4- to 5-month-old diabetic BB rats = 147 +/- 27; 2-month-old nondiabetic BB rats = 1038 +/- 112 pg/ml, peak delta; P < 0.0001). Because time was required for the BB rat to spontaneously develop diabetes, we asked whether the incomplete restoration of the glucagon response might be related to the animals' growth and development. This led us to compare the glucagon response to hypoglycemia in nondiabetic BB and Wistar rats at 2 and 4-5 months of age. We observed age-related deterioration of not only glucose tolerance and insulin sensitivity but also glucagon responses to hypoglycemia in both strains. There was no significant difference between the glucagon responses to hypoglycemia in age-matched nondiabetic BB rats and diabetic BB rats provided with the insulin switch-off signal. We conclude that defective glucagon responses to hypoglycemia in BB rats can be corrected by restoring regulation of alpha-cell function by insulin.
The intraislet insulin hypothesis has been proposed to explain absent glucagon responses to hypoglycemia. Recently we directly confirmed this hypothesis by restoring glucagon secretion via provision of a pancreatic artery insulin infusion, which was switched off at the time of hypoglycemia in Wistar rats made diabetic by streptozotocin. The current study examined this hypothesis in a model of spontaneous, autoimmune diabetes, the insulin-dependent diabetic BB rat. The insulin switch-off signal restored the defective glucagon responses to hypoglycemia. However, the magnitude of the restored response was markedly less than that observed in control nondiabetic BB rats (4- to 5-month-old diabetic BB rats = 147 +/- 27; 2-month-old nondiabetic BB rats = 1038 +/- 112 pg/ml, peak delta; P < 0.0001). Because time was required for the BB rat to spontaneously develop diabetes, we asked whether the incomplete restoration of the glucagon response might be related to the animals' growth and development. This led us to compare the glucagon response to hypoglycemia in nondiabetic BB and Wistar rats at 2 and 4-5 months of age. We observed age-related deterioration of not only glucose tolerance and insulin sensitivity but also glucagon responses to hypoglycemia in both strains. There was no significant difference between the glucagon responses to hypoglycemia in age-matched nondiabetic BB rats and diabetic BB rats provided with the insulin switch-off signal. We conclude that defective glucagon responses to hypoglycemia in BB rats can be corrected by restoring regulation of alpha-cell function by insulin.

Related Concept Videos
 01:26
Type I Diabetes II: Pathophysiology
 01:12
Type I Diabetes I: Introduction
 01:24
Type II Diabetes II: Pathophysiology
 01:15
Hypoglycemia and Glucagon
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:25
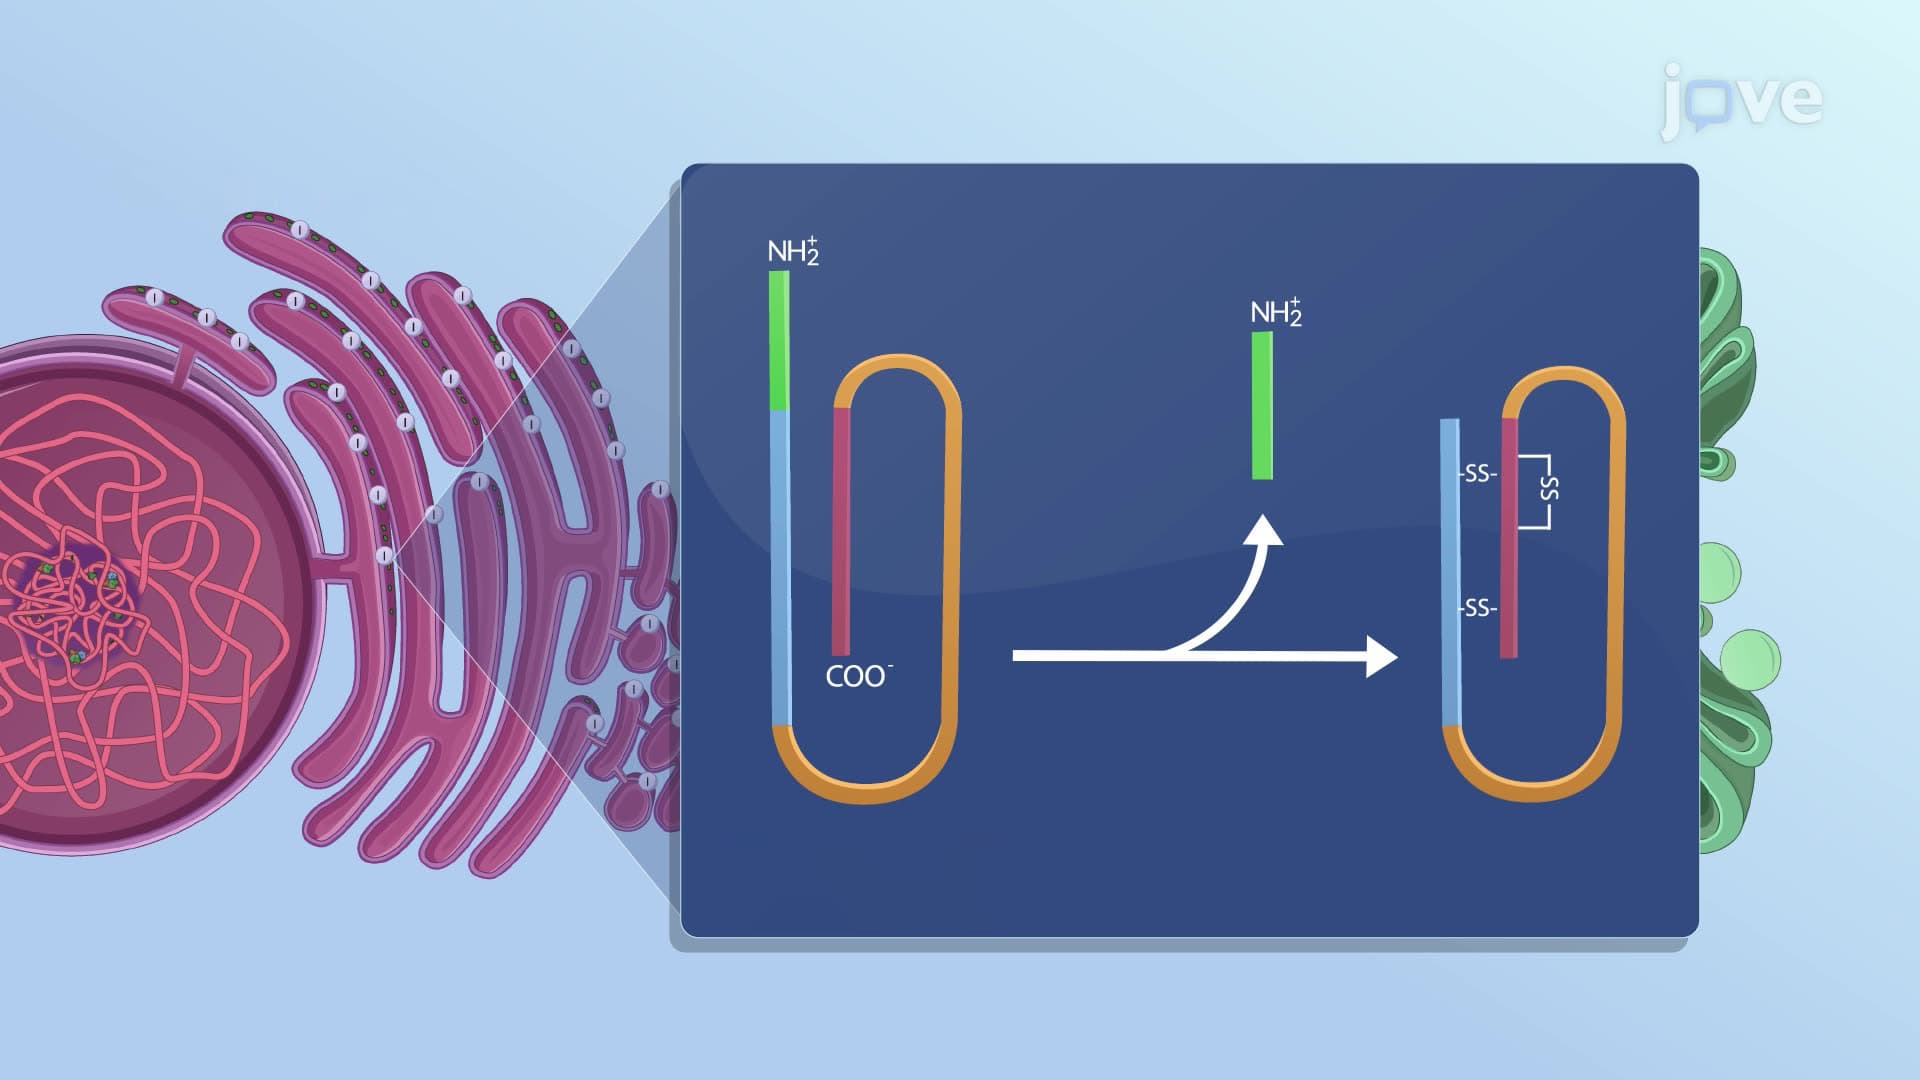
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...