Related Experiment Video
Updated: Jul 16, 2026
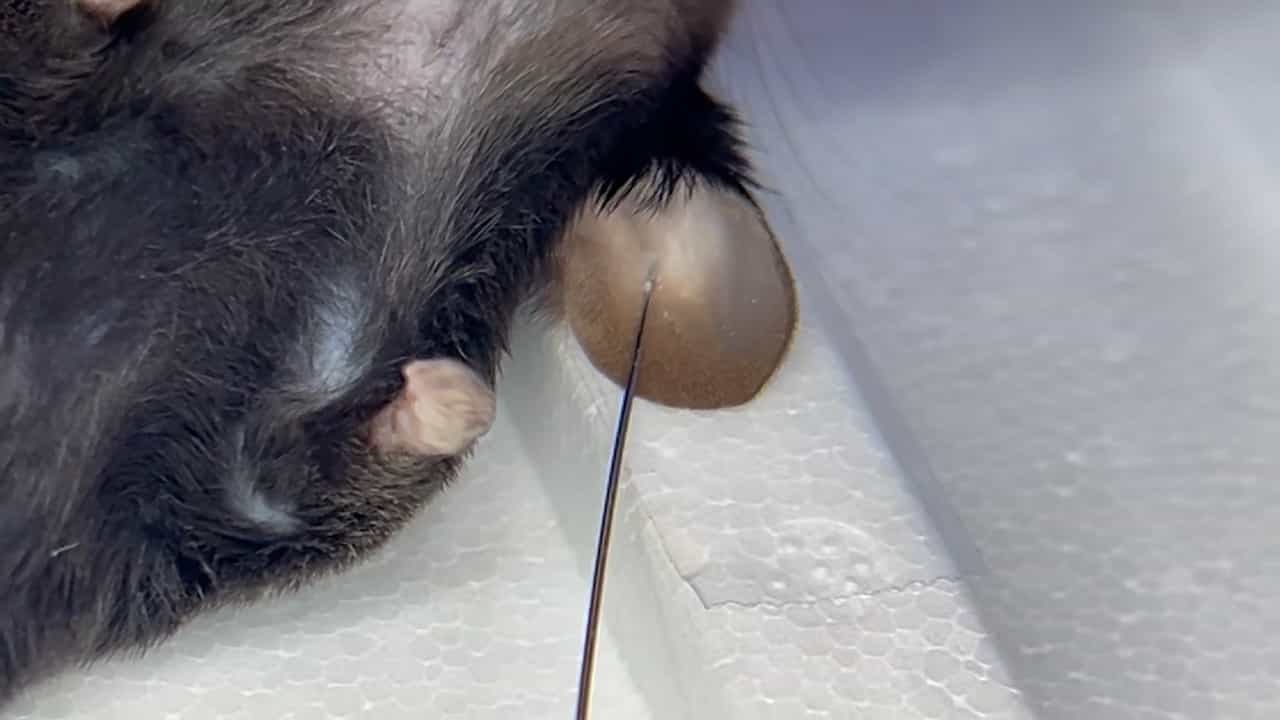

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
[Nontuberculous mycobacterial lymphadenitis]
A Méndez Echevarría1, F Baquero Artigao, M J García Miguel
1Unidad de Infectología Pediátrica, Hospital Infantil La Paz, Madrid, España. amendezes@yahoo.es

Objective:
To study the clinical features, epidemiology and outcome of nontuberculous mycobacterial lymphadenitis (NTML).
Methods:
A retrospective study was performed on 54 patients under 14 years old diagnosed with atypical mycobacterial lymphadenitis between 1987 and 2004. Inclusion criteria were: (i) positive polymerase chain reaction (PCR) test or culture; (ii) positive sensitin skin test 6 mm above Mantoux; (iii) histopathologic features compatible with mycobacterial infection and/or positive direct smear for acid-fast bacilli, Mantoux reaction less than 15 mm, a normal chest radiograph, absence of exposure to an adult with tuberculosis, negative Mantoux test reactions in family members, and exclusion of other causes of granulomatous adenitis.
Results:
Fifty-four patients were included in the study. The number of NTML cases increased notably from 1996, coinciding with a decrease in cases of tuberculous adenitis. The mean age was 35 months (range: 14 months-6 years). Submandibular nodes were involved in 22 of 63 cases of adenitis (34.9%) and cervical nodes were involved in 21 (33.3%). In 8/42 patients (19%) the tuberculin skin test was larger than 10 mm. Cultures were positive in 52.9% of the cases (18/34) and PCR in 53.3% (8/15). The most frequently isolated mycobacteria was Mycobacterium avium (61%). Therapy failed in 8/21 patients receiving antibiotics (38%), in 10/13 patients with drainage alone (77%) and in none of the patients who underwent surgery (8/8).
Conclusions:
Nontuberculous mycobacterial adenitis has become more frequent in our hospital since 1996. Cultures do not always allow isolation of mycobacteria and the Mantoux test frequently yields false positive results, thus hampering diagnosis. The most effective treatment was surgical excision. Nevertheless, when the surgical approach is difficult or there is postoperative recurrence, pharmacological treatment can be useful.
Related Concept Videos
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:23
Tuberculosis
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:14
Atypical Pneumonia
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...