Related Experiment Video
Updated: Jul 26, 2026
Ultrasound Assessment of Endothelial Function: A Technical Guideline of the Flow-mediated Dilation Test
Published on: April 27, 2016
Diuretics, serum and intracellular electrolyte levels, and ventricular arrhythmias in hypertensive men
D Siegel1, S B Hulley, D M Black
1Department of Epidemiology and Biostatistics, University of California, San Francisco.

Insights
Thiazide diuretics can lower serum potassium, but routine potassium supplementation isn't always needed. Monitor potassium levels and use potassium-sparing strategies for individuals developing hypokalemia to prevent ventricular arrhythmias.
Area of Science:
- Cardiology
- Clinical Pharmacology
Background:
- Thiazide diuretics are commonly prescribed for hypertension.
- Controversy exists regarding the routine use of potassium-conserving therapy with thiazides due to potential electrolyte abnormalities and arrhythmias.
Purpose of the Study:
- To investigate electrolyte abnormalities from thiazide administration.
- To determine if these abnormalities cause ventricular arrhythmias.
- To resolve the controversy on routine potassium-conserving therapy with thiazides.
Main Methods:
- Double-blind, randomized controlled trial involving 233 hypertensive men.
- Participants received hydrochlorothiazide, chlorthalidone, or placebo, with or without potassium and magnesium supplementation or triamterene.
- Ventricular arrhythmias and serum/intracellular electrolyte levels were monitored.
Main Results:
- Hydrochlorothiazide lowered serum potassium by 0.4 mmol/L compared to placebo, unaffected by supplementation.
- Supplementation prevented marked hypokalemia (serum potassium ≤ 3.0 mmol/L) in individuals.
- Ventricular arrhythmias were not increased overall but doubled in individuals with serum potassium ≤ 3.0 mmol/L.
Conclusions:
- Most hypertensive patients on hydrochlorothiazide (50 mg/d) do not develop marked hypokalemia or ventricular arrhythmias.
- Monitoring serum potassium and using potassium-sparing strategies are recommended for individuals developing hypokalemia during diuretic therapy.
Objective:
To investigate the patterns of electrolyte abnormalities resulting from thiazide administration and whether they cause ventricular arrhythmias, and to help resolve the controversy over whether clinicians should routinely prescribe potassium-conserving therapy to all patients treated with thiazides.
Design:
Double-blind, randomized controlled trial.
Participants:
A total of 233 hypertensive men aged 35 to 70 years.
Interventions:
Participants were withdrawn from prior diuretic treatment and were replenished with oral potassium chloride and magnesium oxide. They were then randomized to 2 months of treatment with (1) hydrochlorothiazide; (2) hydrochlorothiazide with oral potassium; (3) hydrochlorothiazide with oral potassium and magnesium; (4) hydrochlorothiazide and triamterene; (5) chlorthalidone; or (6) placebo.
Main Outcome Measures:
Ventricular arrhythmias on 24-hour Holter monitoring and serum and intracellular potassium and magnesium levels.
Results:
Of the 233 participants, 212 (91%) completed the study. Serum potassium levels were 0.4 mmol/L lower in the hydrochlorothiazide group than in the placebo group (P less than 0.01), and this mean difference was not affected by supplementation with potassium, with potassium and magnesium, or with triamterene. However, the supplements did prevent the occasional occurrence of marked hypokalemia; all 12 of the men who developed serum potassium levels of 3.0 mmol/L or less were among the 90 who received diuretics without supplementation (P less than 0.01). Similarly, the overall proportion of men with ventricular arrhythmias was not affected by randomized treatment, but there was a twofold increase in the proportion with arrhythmias among the 12 men with serum potassium levels of 3.0 mmol/L or less (P = .02). Serum magnesium and intracellular potassium and magnesium levels were not reduced by hydrochlorothiazide, nor were they related to ventricular arrhythmias.
Conclusions:
In the majority of hypertensive patients, treatment with 50 mg/d of hydrochlorothiazide does not cause marked hypokalemia or ventricular arrhythmias. However, because some individuals will develop hypokalemia after starting diuretic therapy, serum potassium levels should be monitored and potassium-sparing strategies should be used when indicated.
More Related Videos
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
 05:57
The Antihypertensive Effects and Mechanisms of Huotan Jiedu Tongluo Decoction in Rats with H-Type Hypertension
Published on: May 17, 2024
Related Concept Videos
 01:30
Blood Pressure
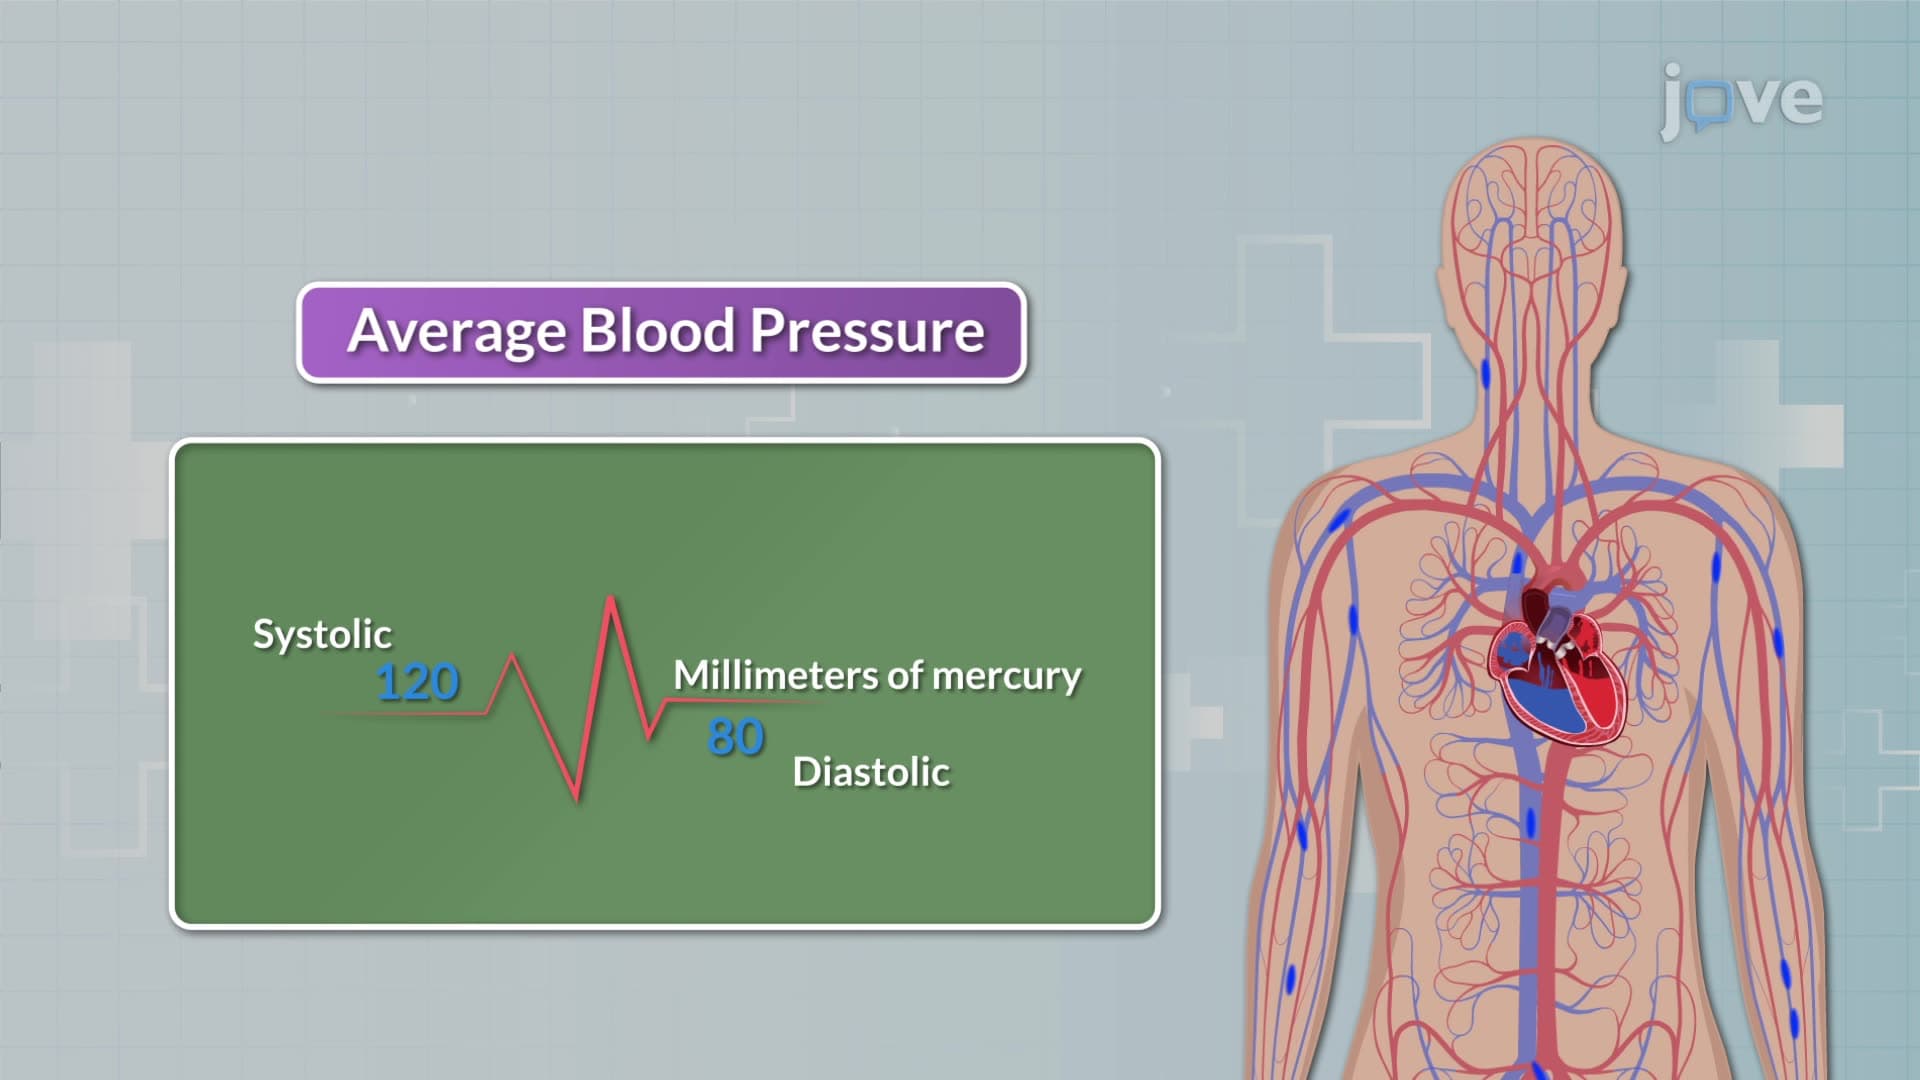
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:18
Hypertension and Regulation of Blood Pressure
 01:24
Blood Pressure
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra. Symptoms...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies