Related Experiment Video
Updated: Jul 16, 2026

Design of Cecal Ligation and Puncture and Intranasal Infection Dual Model of Sepsis-Induced Immunosuppression
Published on: June 15, 2019
Hemofiltration in sepsis and systemic inflammatory response syndrome: the role of dosing and timing
Catherine S C Bouman1, Heleen M Oudemans-van Straaten, Marcus J Schultz
1Department of Intensive Care, Academic Medical Center, University of Amsterdam, PO 22660, 1100 DD Amsterdam, The Netherlands. c.s.bouman@amc.uva.nl

Introduction:
The benefit of hemofiltration (HF) as an adjunctive treatment of sepsis or the systemic inflammatory response syndrome (SIRS) in critically ill patients is a subject of severe debate. Firm conclusions on this subject are hampered by the heterogeneity in study populations and HF treatments, and the lack of adequately sized randomized controlled clinical trials. The aim of this review was to determine the importance of ultrafiltration dose and timing on the physiologic and clinical effects of HF in sepsis and SIRS. In addition, we discuss the issue of filter pore size.
Methods:
Literature search was done in Embase and PubMed database for animal and human studies.
Results:
Animal studies suggest beneficial effects of HF on hemodynamics; gas exchange; sepsis-induced immunoparalysis; histology of gut, lung, and kidney; and (short-term) survival. These effects were more prominent with "very high" ultrafiltrate rates (> or =100 mL/kg per hour) and early initiation of HF (ie, before or very early after the septic challenge). Three small randomized studies and 3 observational studies in patients with sepsis or SIRS show beneficial effects of short-term or pulse HF using very high ultrafiltrate rates and/or early initiation of HF on physiologic endpoints and survival. However, the studies were underpowered for survival. The first observations of high permeability HF (pore size, about 10 nm; in vitro cutoff, 100 kd) are promising, but so far, it has not been sufficiently examined to allow strong conclusions.
Conclusion:
Human and animal studies suggest that early initiation and high ultrafiltrate volumes are determinants of the beneficial physiologic and clinical effect of HF in sepsis and SIRS. As yet, the evidence in humans is too low to recommend HF as an adjunctive therapy for critically ill patients with sepsis or SIRS. Regarding the many uncertainties about optimal volume (high or very high) and type of membrane, clinical studies should first focus on endpoints as recovery from organ failure and length of treatment before survival studies are started.
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
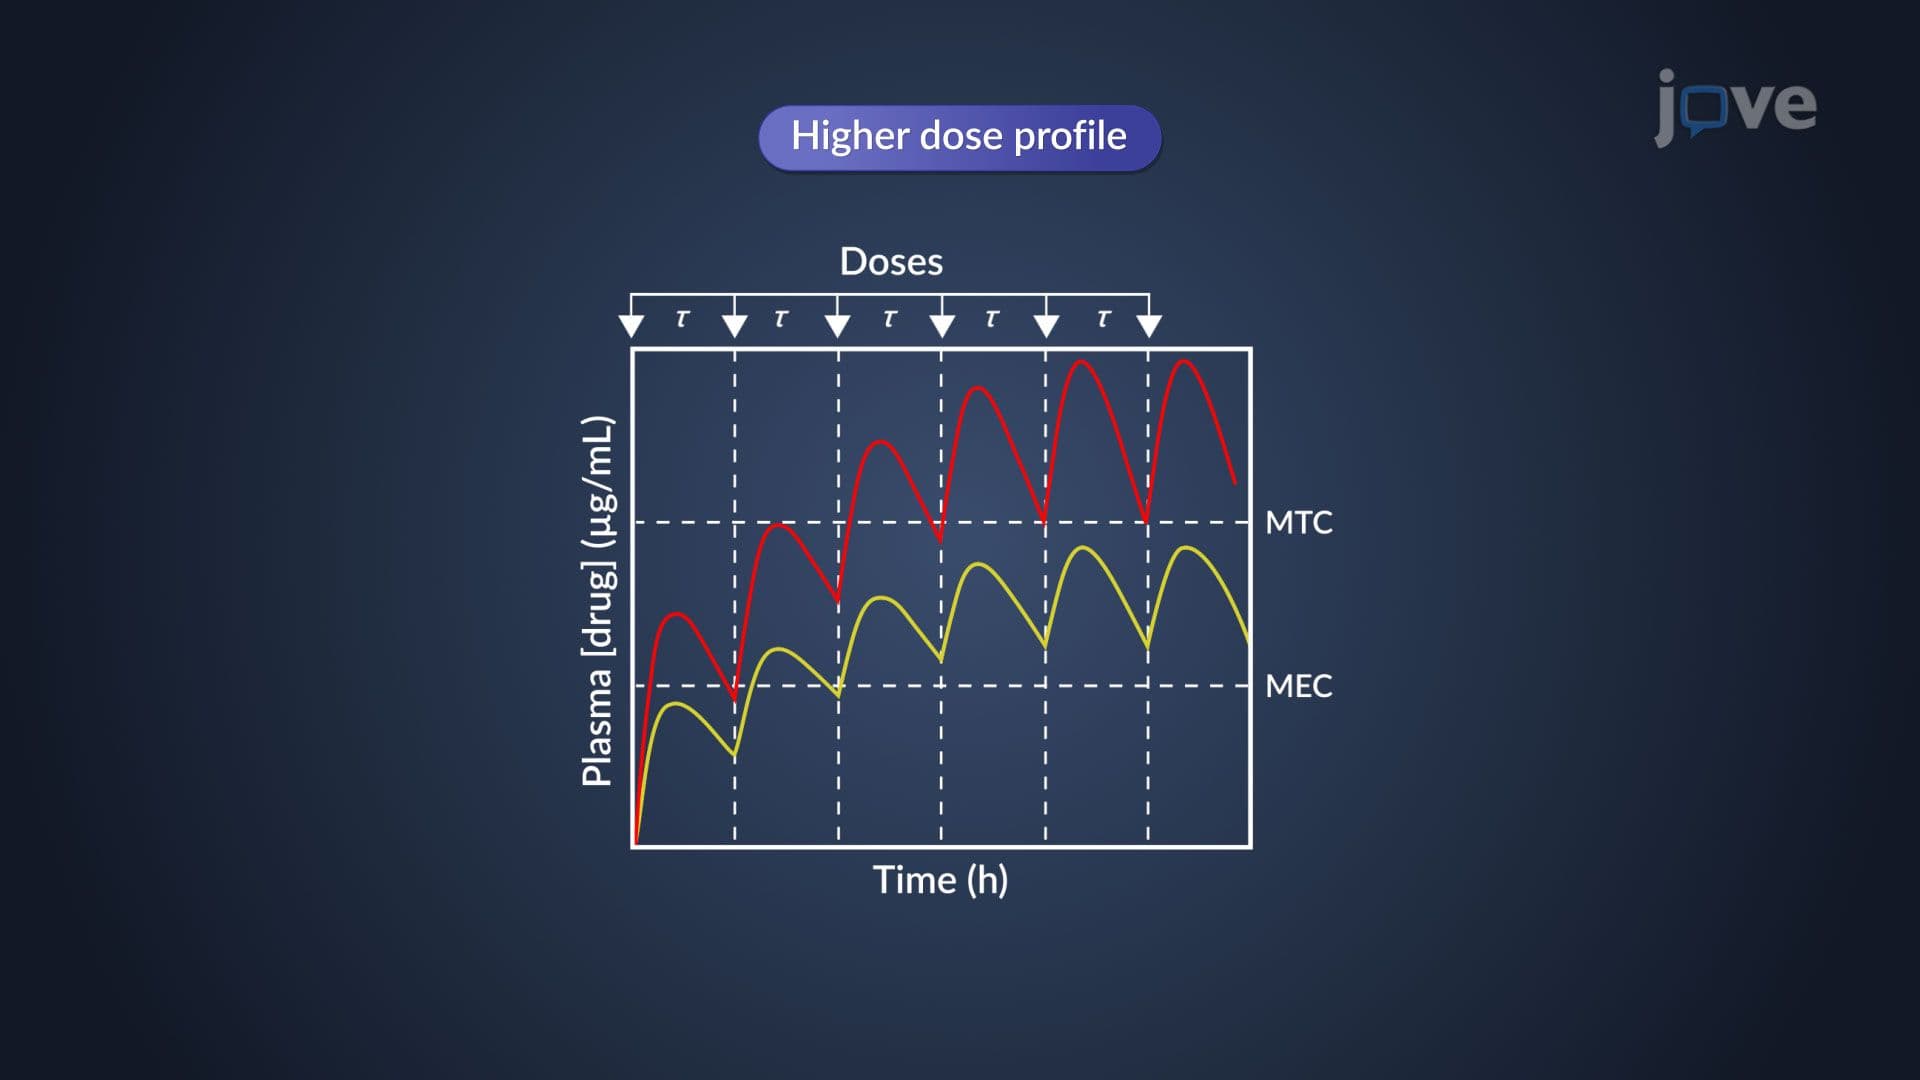 01:21
Dose Size and Dosing Frequency: Determination Methods
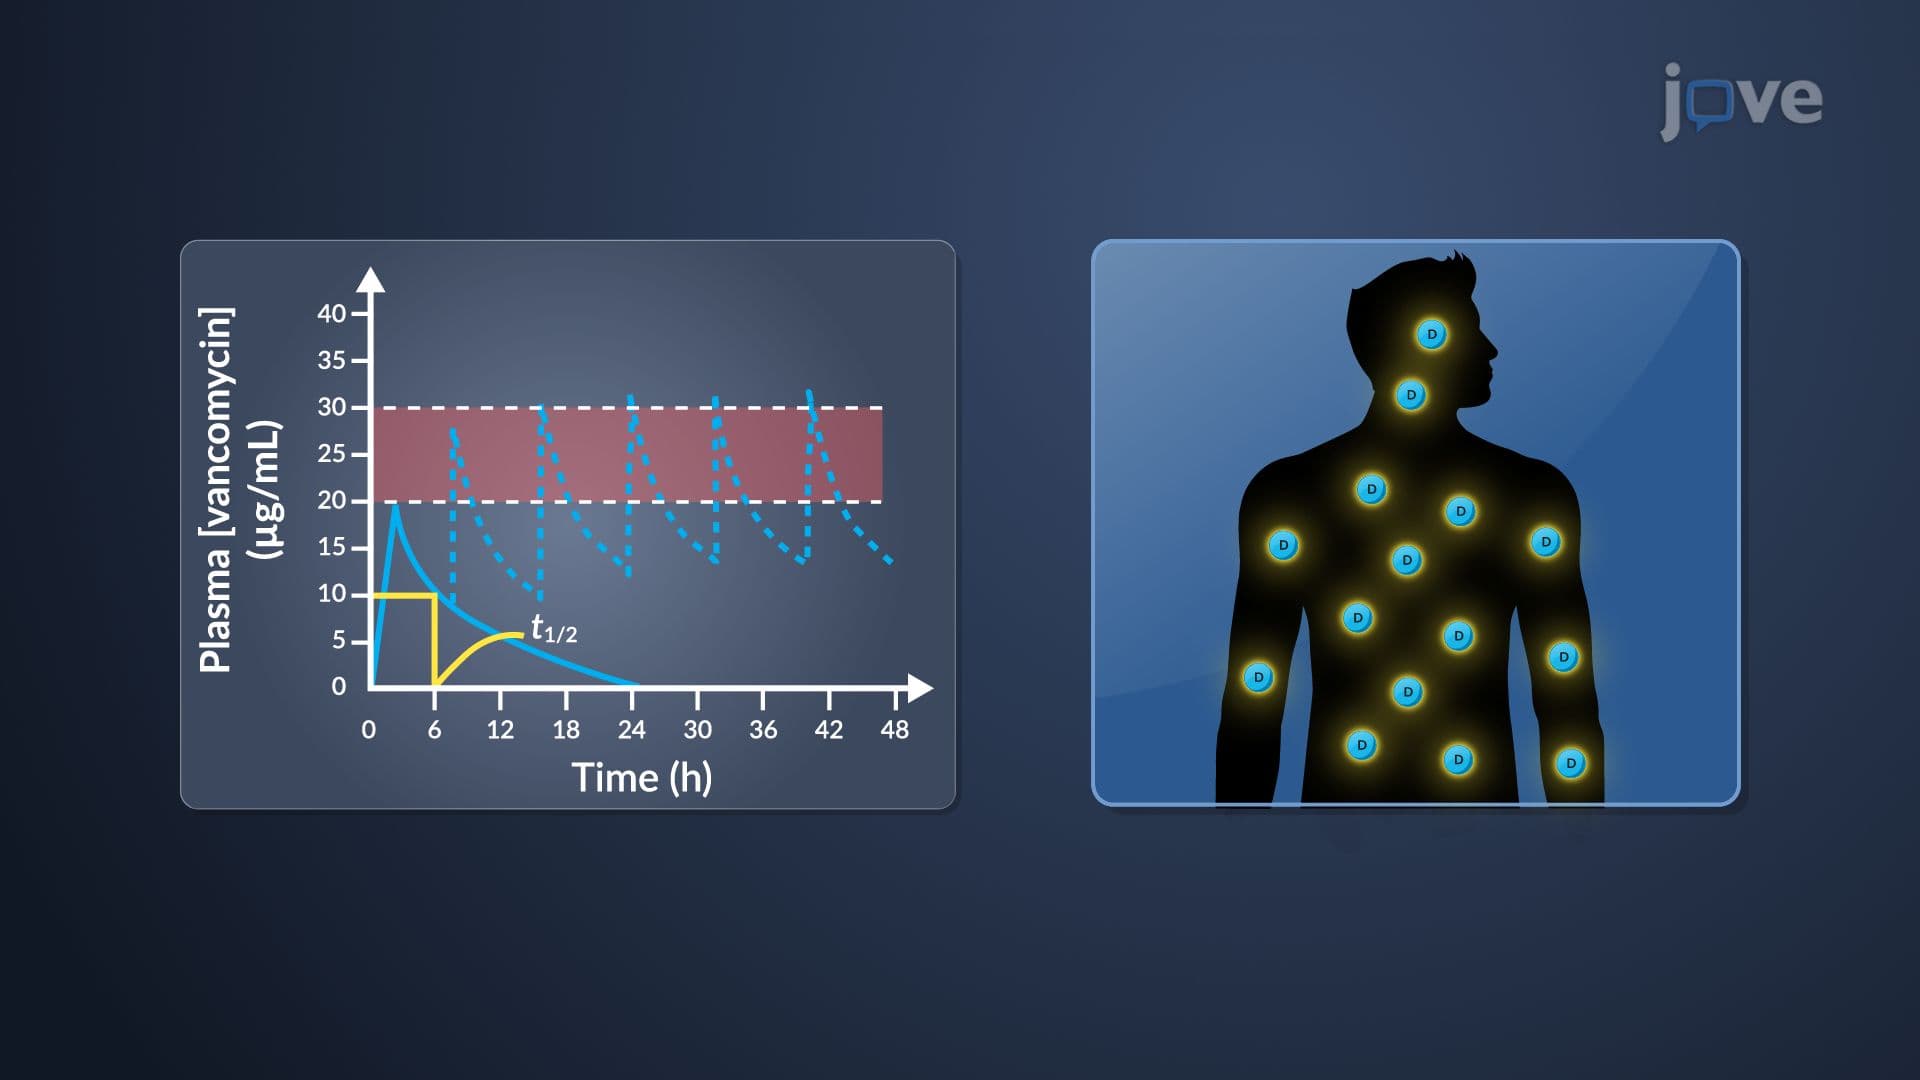 01:19
Dosage Interval and Administration Route: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...