Related Experiment Video
Updated: Jul 16, 2026


Murine Appendectomy Model of Chronic Colitis Associated Colorectal Cancer by Precise Localization of Caecal Patch
Published on: August 24, 2019
Risk factors for the development of abdominal abscess following operation for perforated appendicitis in children: a
Marion C W Henry1, Angela Walker, Bonnie L Silverman
1Yale University School of Medicine, New Haven, CT 06520, USA.

Insights
Intraoperative fecaliths and diarrhea at presentation are key risk factors for intra-abdominal abscesses after perforated appendicitis in children. Children who are fever-free and eating by postoperative day 3 can be safely discharged with a low risk of abscess.
Area of Science:
- Pediatric Surgery
- Gastrointestinal Surgery
- Infectious Disease
Background:
- Perforated appendicitis in children leads to significant morbidity, including intra-abdominal abscesses.
- Intra-abdominal abscesses necessitate prolonged hospitalization, extensive antibiotic use, and invasive procedures.
Purpose of the Study:
- To identify risk factors associated with the development of intra-abdominal abscesses following treatment for perforated appendicitis in children.
Main Methods:
- A case-control study was conducted across four tertiary care children's hospitals.
- Data from 265 children (aged 1-18 years) with appendicitis were analyzed using multivariable logistic regression.
- Outcomes included postoperative abscess development, hospital stay, fever, and diet tolerance on postoperative day 3.
Main Results:
- An intraoperative fecalith (OR, 8.77) and diarrhea at presentation were significant predictors of abscess development.
- Commonly suspected factors like pain history, antibiotic timing, and operative findings were not significant predictors.
- Children discharged on or before postoperative day 3 had no abscesses, while 2 remaining children developed abscesses (P = .06).
Conclusions:
- Traditional predictors of abscess formation after perforated appendicitis are unreliable.
- Discharging children who are afebrile and tolerating a diet by postoperative day 3 is associated with a low rate of abscess development.
Hypothesis:
The morbidity following treatment for perforated appendicitis in children is significant, with intra-abdominal abscess being one of the more serious complications. This can lead to prolonged hospitalizations and antibiotic administration, multiple computed tomographic scans, and invasive procedures. The purpose of our study was to determine risk factors for developing an intra-abdominal abscess following treatment for perforated appendicitis.
Design:
Case-control study.
Setting:
Four tertiary care children's hospitals.
Patients:
Children aged 1 to 18 years with appendicitis.
Intervention:
Multivariable logistic regression.
Main Outcome Measures:
Development of postoperative abscess, length of hospital stay, presence or absence of fever, and tolerance of diet on postoperative day 3.
Results:
Thirty-five (13.2%) of 265 children developed an abscess. Ten factors with a bivariate P value <.20 were included in the regression model. The final multivariable model revealed only 2 factors influencing abscess development: an intraoperative fecalith (odds ratio, 8.77 [95% confidence interval, 1.50-51.40]) and diarrhea at presentation. Many factors proposed to be associated with abscess were not, including pain history, type and timing of preoperative antibiotics, abscess at operation, laparoscopic procedure, and length of antibiotics postoperatively. Thiry-seven children were discharged on or before postoperative day 3. Another 21 children were afebrile and tolerating a diet at that time but remained in the hospital. There were no significant differences between the 2 groups. None of the early-discharge group developed an abscess, and 2 of those remaining in the hospital developed an abscess (P = .06).
Conclusions:
Clinical factors commonly thought to be predictive of abscess formation following perforated appendicitis were not reliable predictors of this outcome. Our results suggest that if children are afebrile and eating on postoperative day 3 they can be discharged with a low rate of abscess development.
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
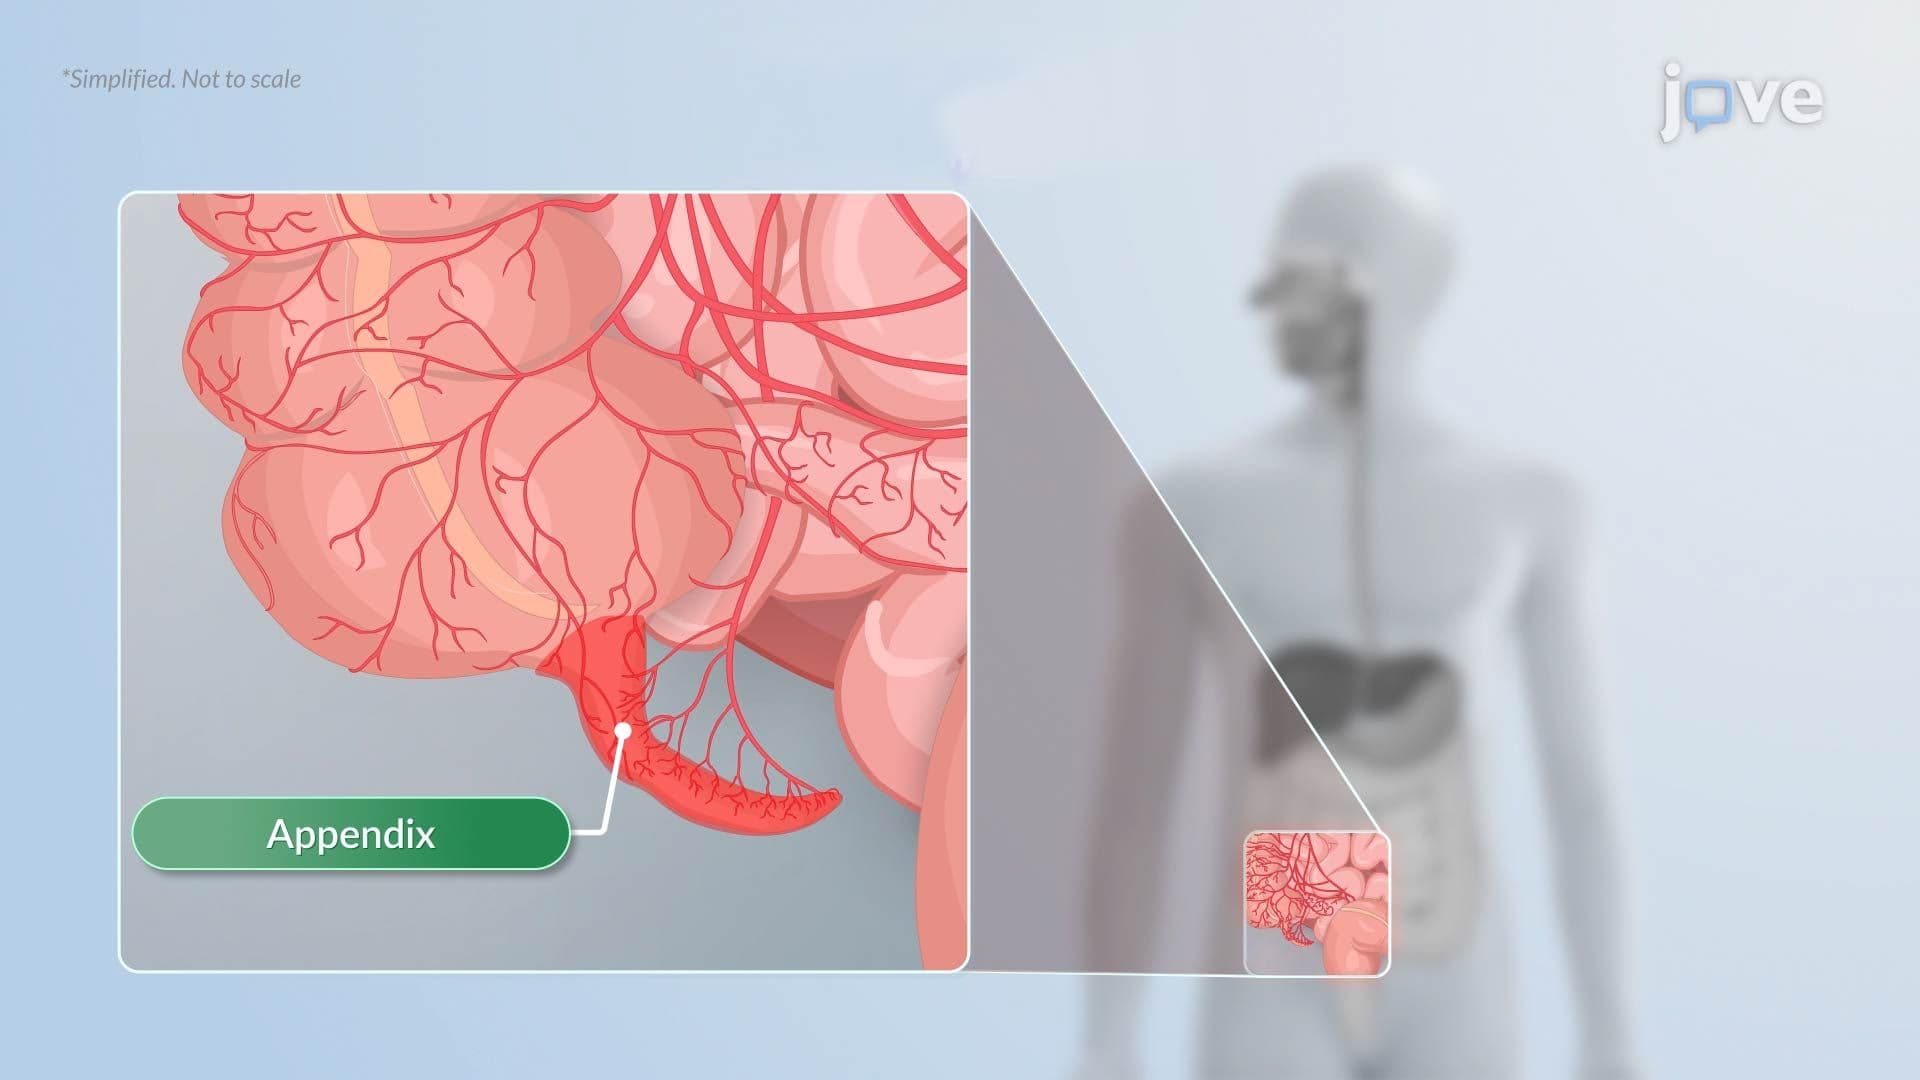
Appendicitis
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:07
Intestinal Obstruction II: Pathophysiology