Related Experiment Video
Updated: Jul 16, 2026


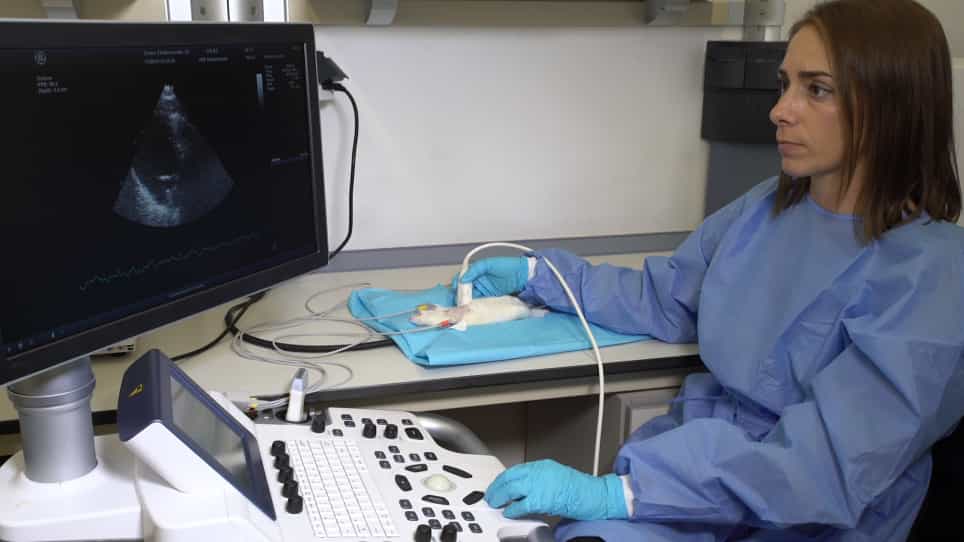
Pulsed Wave Doppler Assessment of Diastolic Dysfunction in the ZSF-1 Rat Model of Pulmonary Hypertension Due to Left Heart Disease
Published on: May 22, 2026
Left ventricular diastolic dysfunction in chronic aortic dissection
Yasushige Shingu1, Norihiko Shiiya, Taisei Mikami
1Department of Cardiovascular Surgery, Hokkaido University Hospital, Sapporo, Hokkaido, Japan. fwpc1650@mb.infoweb.ne.jp

Insights
Chronic aortic dissection with a double-barrel aorta and narrowed true lumen significantly impairs left ventricular diastolic function. This condition leads to more severe diastolic dysfunction compared to other forms of aortic dissection.
Area of Science:
- Cardiology
- Cardiovascular Imaging
- Aortic Diseases
Background:
- Chronic aortic dissection can elevate left ventricular afterload due to true lumen compression by an expanded false lumen.
- This compression may lead to impaired left ventricular diastolic function.
Purpose of the Study:
- To compare left ventricular diastolic function in patients with double-barrel descending aortic dissection versus those without.
- To investigate the impact of true lumen narrowing on diastolic function.
Main Methods:
- Echocardiography was used to evaluate left ventricular diastolic function in 12 patients with chronic type B aortic dissection.
- Patients were divided into two groups: double-barrel dissection with a narrowed true lumen (n=7) and wider true lumen with thrombosed false lumen (n=5).
- Transmitral flow patterns (E/A waves) and flow propagation velocity (FPV) were assessed and diastolic dysfunction was graded.
Main Results:
- Patients with a narrowed true lumen (double-barrel) showed a higher E/A ratio (1.16 +/- 0.39) compared to those with a wider true lumen (0.68 +/- 0.18).
- Four of seven patients in the double-barrel group exhibited grade II diastolic dysfunction (pseudonormalization), indicated by FPV/E < 0.6 and E/A > 1.0.
- All patients with a wider true lumen had grade I diastolic dysfunction (abnormal relaxation) with E/A < 1.0.
Conclusions:
- Left ventricular diastolic function is significantly reduced in patients with aortic dissection characterized by a double-barrel aorta and a narrowed true lumen.
- True lumen compression in double-barrel aortic dissection is associated with more severe diastolic dysfunction.
Background:
In chronic aortic dissection, compression of the true lumen by the expanded false lumen may be a cause of left ventricular afterload elevation, which may result in diastolic dysfunction. We compared the left ventricular diastolic function by echocardiography between those patients who had double-barrel descending aortic dissection and those who did not.
Methods:
Twelve patients (mean age, 61 +/- 12 years) with chronic type B aortic dissection were enrolled in this study. Patients in group I had double-barrel aortic dissection that had expanded the patent false lumen and narrowed the true lumen (n = 7, 58.3%), and patients in group II had a wider-caliber true lumen with a thrombosed false lumen (n = 5, 41.7%). We evaluated the left ventricular diastolic function with the transmitral flow pattern (E and A waves) with the pulsed Doppler method and flow propagation velocity (FPV) with color M-mode Doppler images, and classified its severity into grade I (abnormal relaxation), grade II (pseudonormalization) and grade III (restriction).
Results:
All patients in group II had grade I diastolic dysfunction, with an E/A of less than 1.0. By contrast, 4 of the 7 patients in group I had grade II diastolic dysfunction, with an FPV/E of less than 0.6 and a pseudonormalized (> 1.0) E/A ratio (p = 0.081). Consequently, the E/A ratio was higher in group I than in group II (1.16 +/- 0.39 versus 0.68 +/- 0.18; p < 0.05).
Conclusions:
It is suggested that left ventricular diastolic function is severely reduced in the patients having aortic dissection with a double-barrel and narrowed true lumen.

Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:25
Aortic Regurgitation III: Medical Management
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction