Related Experiment Video
Updated: Jul 16, 2026
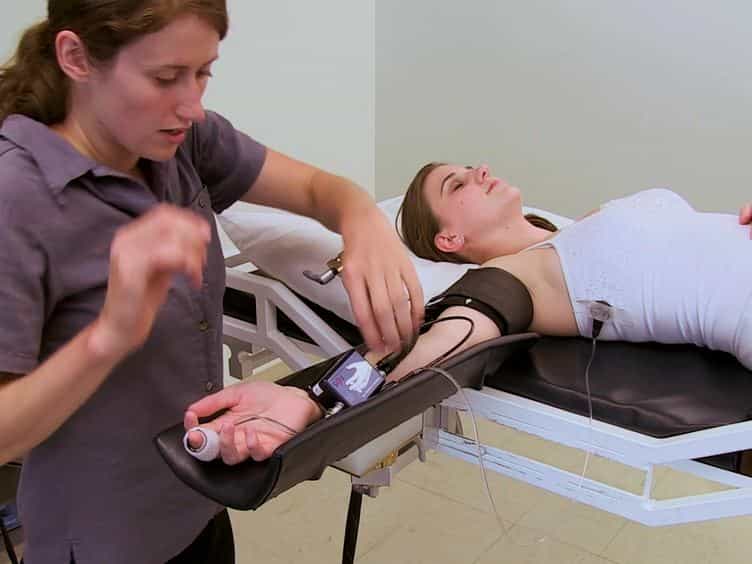

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
The Risk stratification Of Syncope in the Emergency department (ROSE) pilot study: a comparison of existing syncope
Matthew J Reed1, David E Newby, Andrew J Coull
1Emergency Department, Royal Infirmary of Edinburgh, 51 Little France Crescent, Edinburgh EH16 4SA, UK. mattreed1@hotmail.com

Aims:
This study was conducted as a feasibility pilot for the Risk stratification Of Syncope in the Emergency department (ROSE) study. The secondary aim was to compare the performance of our existing emergency department (ED) guidelines with existing clinical decision rules (Osservatorio Epidemiologico sulla Sincope nel Lazio (OESIL) Score and San Francisco Syncope Rule; SFSR) at predicting short-term (1 week and 1 month) and medium-term (3 months) serious outcomes for patients with syncope presenting to the ED.
Methods:
This was a prospective cohort study. All patients presenting with syncope aged > or = 16 years between 7 November 2005 and 7 February 2006 were prospectively enrolled.
Results:
99 patients were recruited over a 3-month period. 44 patients were admitted and 55 discharged from the ED. 11 patients had a serious outcome: 8 by 7 days and a further 3 by 3 months. Five patients died by 3 months and six others had an alternative serious outcome. All 11 patients had been admitted from the ED, 7 were at high risk, 4 were at medium risk and none were at low risk according to our existing ED guidelines. Percentages of serious outcomes were 0%, 2.9%, 8.0%, 22.7% and 37.5% for OESIL scores of 0, 1, 2, 3 and 4 respectively. 40 patients had none of the 5 SFSR high-risk factors (0 serious outcomes = 0%) and 59 patients had an SFSR high-risk factor (11 serious outcomes = 18.6%). The risk of serious outcome at 7 days, 1 month and 3 months was 8.1%, 8.1% and 11.1%, respectively.
Conclusions:
A study to derive and validate a UK ED syncope clinical decision rule is feasible. This pilot study has evaluated the OESIL score, the SFSR and our existing ED guidelines, and has shown that each is able to identify an increased probability of medium-term serious outcome in patients with syncope. The SFSR shows good sensitivity at the expense of an increase in admissions to hospital; however, our existing ED syncope guidelines and the OESIL Score, although being able to successfully risk stratify patients, are not sufficiently sensitive to be able to reduce admissions without missing patients at risk of a serious outcome. Undoubtedly there is a need for a simple UK-derived clinical decision rule for patients presenting with syncope to enable safe, effective clinical care and to aid less experienced decision makers.
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:30
Acute Coronary Syndrome I: Introduction
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Dysrhythmias V: Evaluating Dysrhythmias