Related Experiment Video
Updated: Jul 16, 2026
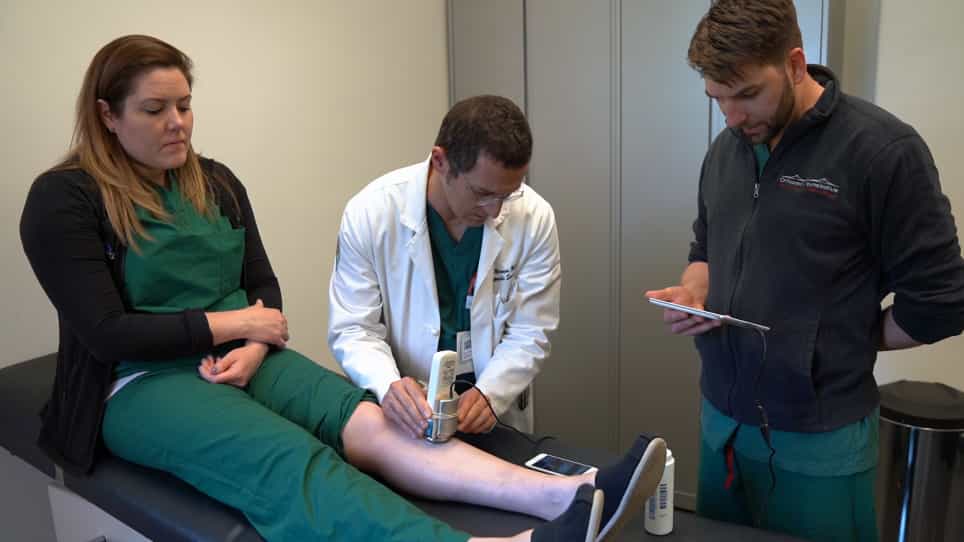

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
Compartment syndrome secondary to spontaneous rupture of a Baker's cyst
1Tulane Hospitals and Clinics, USA.

Abstract:
A 49-year-old woman with end-stage renal disease secondary to posterior urethral valves has received two kidney transplants since 1975, and both have succumbed to chronic rejection. She has been anuric since 2003 and undergoes hemodialysis three times a week. She was admitted to our hospital for evaluation for a third kidney transplant. The kidney was found to be unsuitable for this recipient, and she was taken to dialysis prior to discharge. Shortly after dialysis, she developed acute pain in the lower portion of her left leg and received a venous ultrasound to rule out possible deep vein thrombosis. No thrombus was appreciated. Instead, a Baker's cyst appeared to have ruptured its contents into her deep posterior compartment. In the twenty minutes it took to perform the ultrasound, her symptoms worsened, and her leg became firm. The patient reported extreme pain, paresthesias over the lateral aspect of the lower portion of the leg, and an inability to plantarflex or dorsiflex the foot. The foot was warm to the touch and still had a palpable pulse. The leg was beginning to lighten in color. The patient underwent an emergent fasciotomy. Pressure within the posterior compartment of the leg was measured at 120 mm Hg just prior to incision. The anterior, medial, and lateral compartments were measured at pressures of 23, 32, and 26 mm Hg, respectively. A two-incision anterolateral faciotomy was performed, and the wounds were left open to heal by secondary intention. The patient's convalescence was unremarkable, and she is still listed for renal transplantation.
Related Concept Videos
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology
 01:24
Healing II: Complications
 01:14
Increased Intracranial Pressure l: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:14
Spinal Cord Injury ll: Pathophysiology