Related Experiment Video
Updated: Jul 15, 2026

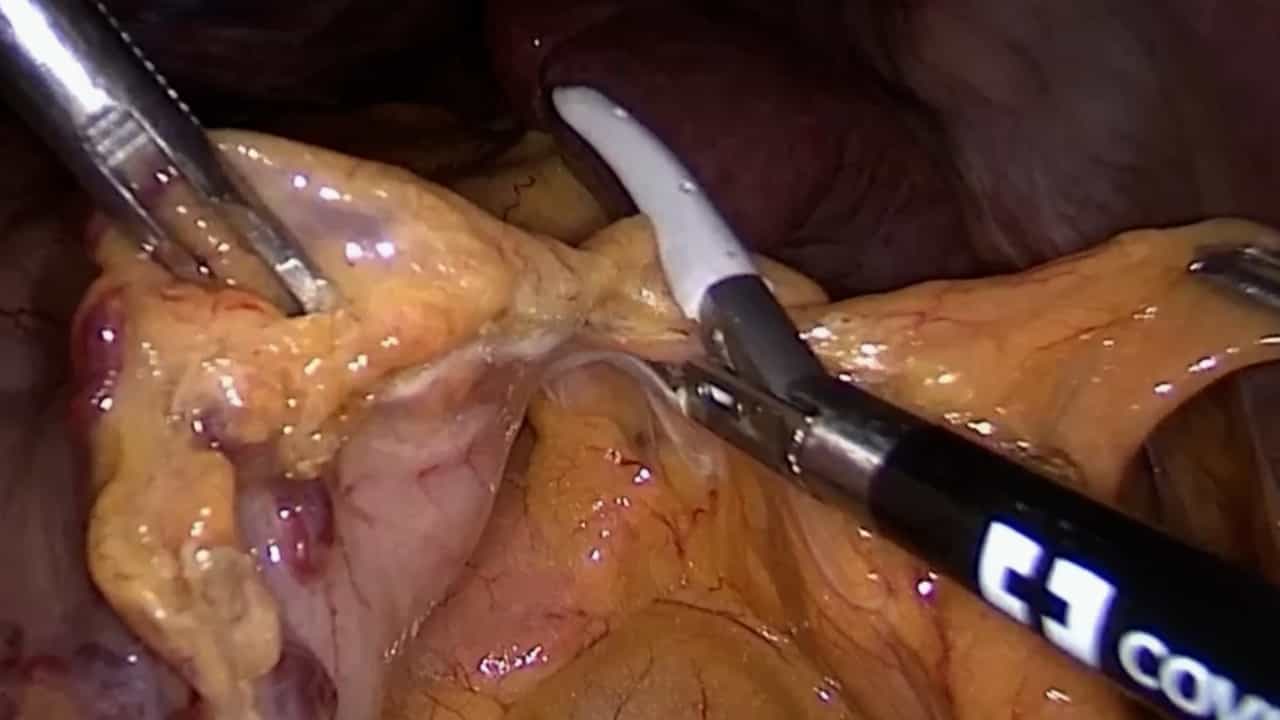
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Laparoscopic splenectomy in a pregnant patient with immune thrombocytopenic purpura
T W Felbinger1, M Posner, H K Eltzschig
1Department of Anesthesiology, Perioperative and Pain Medicine, Brigham and Women's Hospital, Harvard Medical School, Boston, USA.

We describe the perioperative management of a pregnant woman at 19 weeks' gestation with idiopathic thrombocytopenic purpura requiring laparoscopic splenectomy. The preoperative platelet count ranged between 1 and 5 x 10(9)/L and did not respond to conventional medical therapy. To reduce the risk of intracerebral hemorrhage, platelets were transfused before induction of anesthesia to maintain platelet count closer to 20 x 10(9)/L. The blood pressure was monitored continuously via an arterial line and remifentanil was infused to prevent a hypertensive response to induction/intubation, carbon dioxide insufflation, and surgery. After the splenic artery was clamped, additional platelet units were transfused to assure surgical hemostasis.
We describe the perioperative management of a pregnant woman at 19 weeks' gestation with idiopathic thrombocytopenic purpura requiring laparoscopic splenectomy. The preoperative platelet count ranged between 1 and 5 x 10(9)/L and did not respond to conventional medical therapy. To reduce the risk of intracerebral hemorrhage, platelets were transfused before induction of anesthesia to maintain platelet count closer to 20 x 10(9)/L. The blood pressure was monitored continuously via an arterial line and remifentanil was infused to prevent a hypertensive response to induction/intubation, carbon dioxide insufflation, and surgery. After the splenic artery was clamped, additional platelet units were transfused to assure surgical hemostasis.