Related Experiment Video
Updated: Jul 15, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
[Intravenous cyclophosphamide in lupus nephritis: twenty years reducing dose]
M A Frutos1, A Martín Gómez, E de Ramón
1Nefrología, Hospital Universitario Carlos Haya. mfrutoss@senefro.org

The prognosis for patients with proliferative glomerulonephritis associated with systemic lupus erythematosus has dramatically improved over recent decades. We review our experience with intermittent pulse therapy with intravenous cyclophosphamide (IC) in 97 patients (75 female) aged over 20 years. The series was divided into three groups. Group A (n=39) received monthly IC pulses (begin 1 g) for up to 24 months between 1985-1991. Group B (n=47) received monthly IC pulses (1 g) for six months with additional quarterly doses for a maximum of 18 months, depending on the therapeutic response (from 1991). From 1999, Group C (n=11) patients were treated with low-dose IC (3 g in three months) followed by azathioprine (2 mg/kg) or mycophenolate mofetil (1.5-2.0 g/day) for 12-18 months. The total IC doses (g) administered were: Group A, 15.1+/-9.0; Group B, 8.5+/-3.5; and Group C, 3.0+/-0.0. These figures show the trend progressive reduction in exposure to IC. Overall, treatment with the different IC regimens achieved satisfactory control of lupus nephritis in 76% of the patients. Comparison of the values at baseline and after 24 months showed that the serum creatinine (mg/dl) fell in Group A from 1.77+/-1.06 to 1.09+/-0.63, in Group B from 1.22+/- 0.85 to 0.95+/- 0.45, and in Group C from 0.90+/-0.23 to 1.17+/-0.54 (p<0.05). In the same period, proteinuria (g/day) fell in Group A from 6.19+/-4.31 to 0.79+/-1.76, in Group B from 4.43+/- 3.17 to 2.08+/-3.65, and in Group C from 5.43+/- 3.37 to 3.22+/-4.00 (p=0.05). There was not differences between the three groups in both variables. The adverse effects were mainly viral and bacterial infections, with no intergroup differences. Avascular osteonecrosis requiring hip replacement and early menopause were more frequent in Group A. Nine patients died, seven due to cardiovascular causes and two with infection. No differences were detected between the three groups when analyzing the overall patient survival at 5, 10 and 15 years (95%, 92%, and 84%, respectively). The likelihood of maintaining serum creatinine within normal ranges or less than twice the baseline range was similar in the three groups at 5, 10 and 15 years (92%, 72% and 66%, respectively). There were 47 episodes of relapse, with no differences between the three groups. In Summary, treatment with different regimens of intermittent IC is relatively safe and efficient to control the disease and lupus nephritis in SLE patients even with progressively smaller doses. The price paid concerned infectious complications, and bone and ovarian toxicity. New alternatives should at least maintain the same efficacy, but with fewer adverse effects and relapses.
The prognosis for patients with proliferative glomerulonephritis associated with systemic lupus erythematosus has dramatically improved over recent decades. We review our experience with intermittent pulse therapy with intravenous cyclophosphamide (IC) in 97 patients (75 female) aged over 20 years. The series was divided into three groups. Group A (n=39) received monthly IC pulses (begin 1 g) for up to 24 months between 1985-1991. Group B (n=47) received monthly IC pulses (1 g) for six months with additional quarterly doses for a maximum of 18 months, depending on the therapeutic response (from 1991). From 1999, Group C (n=11) patients were treated with low-dose IC (3 g in three months) followed by azathioprine (2 mg/kg) or mycophenolate mofetil (1.5-2.0 g/day) for 12-18 months. The total IC doses (g) administered were: Group A, 15.1+/-9.0; Group B, 8.5+/-3.5; and Group C, 3.0+/-0.0. These figures show the trend progressive reduction in exposure to IC. Overall, treatment with the different IC regimens achieved satisfactory control of lupus nephritis in 76% of the patients. Comparison of the values at baseline and after 24 months showed that the serum creatinine (mg/dl) fell in Group A from 1.77+/-1.06 to 1.09+/-0.63, in Group B from 1.22+/- 0.85 to 0.95+/- 0.45, and in Group C from 0.90+/-0.23 to 1.17+/-0.54 (p<0.05). In the same period, proteinuria (g/day) fell in Group A from 6.19+/-4.31 to 0.79+/-1.76, in Group B from 4.43+/- 3.17 to 2.08+/-3.65, and in Group C from 5.43+/- 3.37 to 3.22+/-4.00 (p=0.05). There was not differences between the three groups in both variables. The adverse effects were mainly viral and bacterial infections, with no intergroup differences. Avascular osteonecrosis requiring hip replacement and early menopause were more frequent in Group A. Nine patients died, seven due to cardiovascular causes and two with infection. No differences were detected between the three groups when analyzing the overall patient survival at 5, 10 and 15 years (95%, 92%, and 84%, respectively). The likelihood of maintaining serum creatinine within normal ranges or less than twice the baseline range was similar in the three groups at 5, 10 and 15 years (92%, 72% and 66%, respectively). There were 47 episodes of relapse, with no differences between the three groups. In Summary, treatment with different regimens of intermittent IC is relatively safe and efficient to control the disease and lupus nephritis in SLE patients even with progressively smaller doses. The price paid concerned infectious complications, and bone and ovarian toxicity. New alternatives should at least maintain the same efficacy, but with fewer adverse effects and relapses.
Related Concept Videos
 01:24
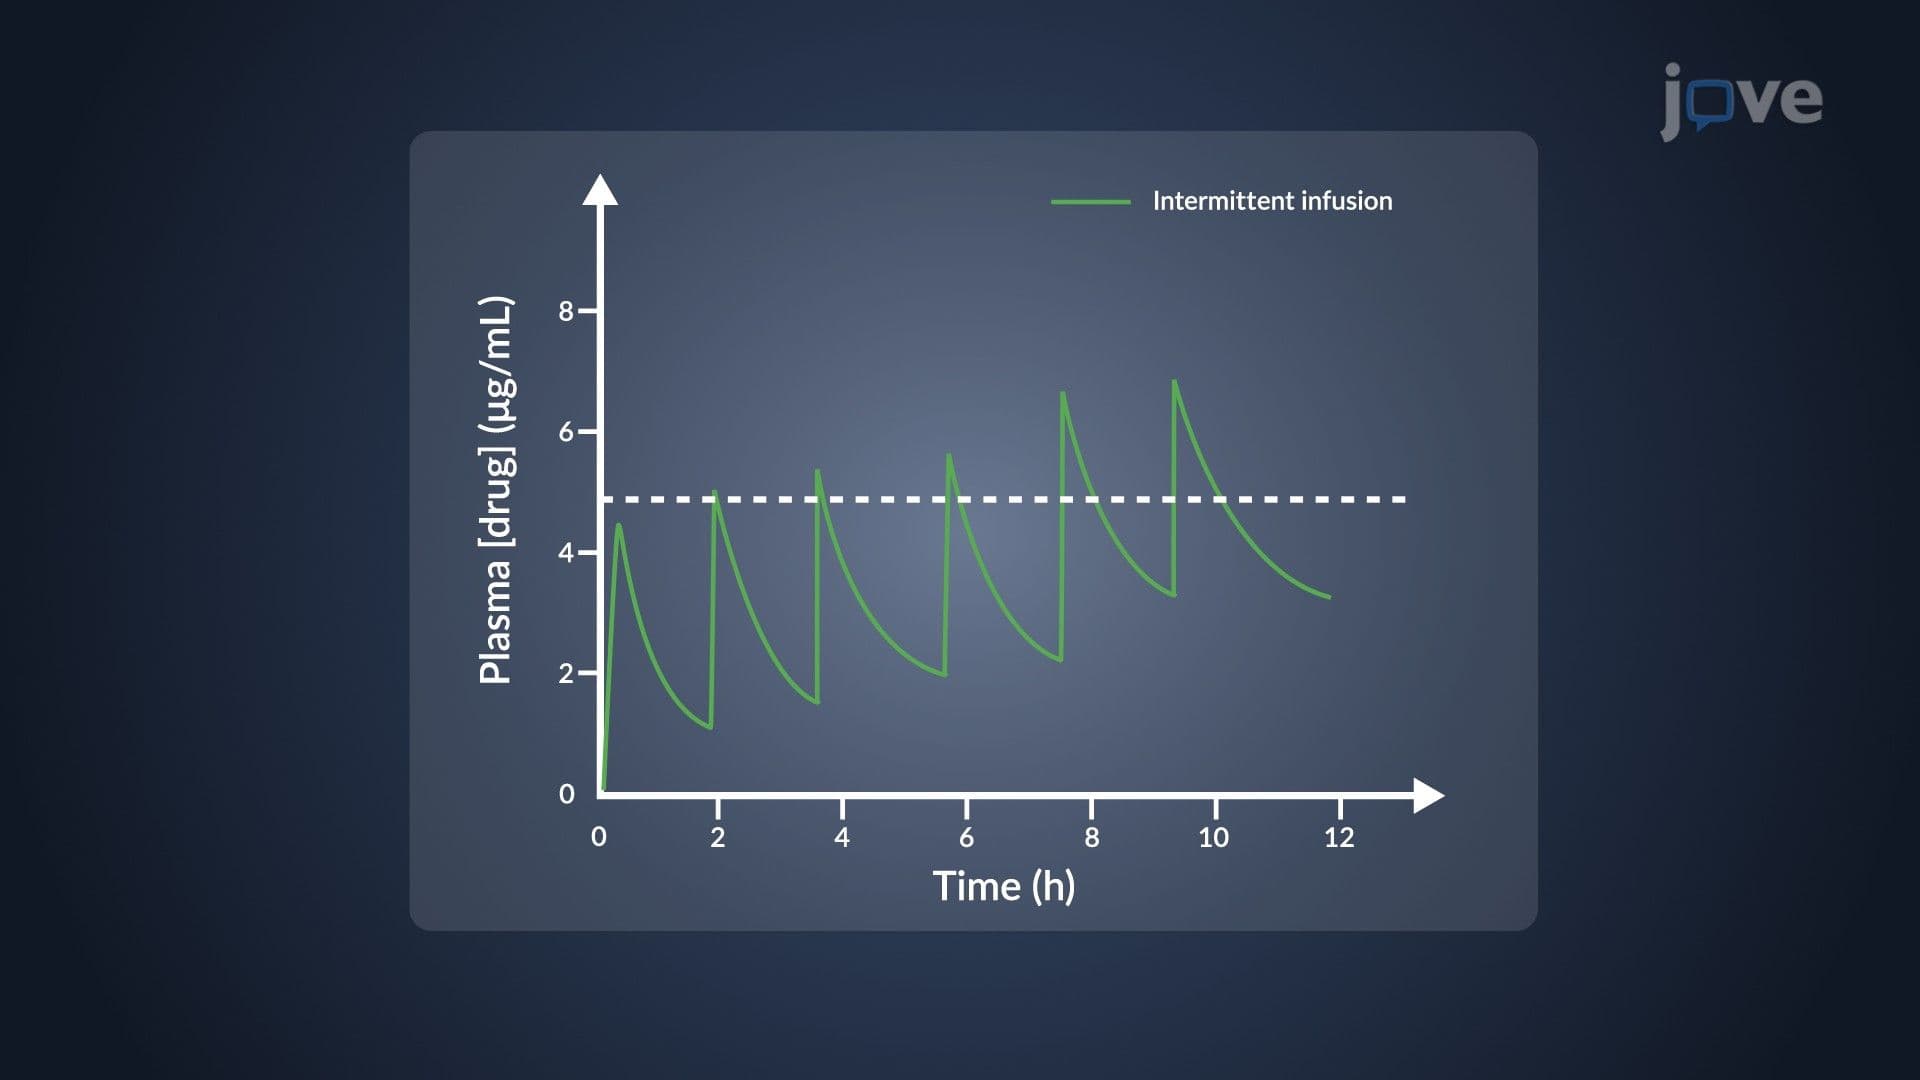
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion