

Insights
Neuraminidase inhibitors like oseltamivir and zanamivir are effective antiviral treatments for children
Area of Science:
- Pediatric Infectious Diseases
- Virology
- Pharmacology
Background:
- Antiviral agents are available for treating and preventing influenza in children.
- Neuraminidase inhibitors (oseltamivir, zanamivir) are preferred over adamantanes (amantadine, rimantadine) due to widespread resistance.
- Influenza virus infections pose a significant health concern in pediatric populations.
Purpose of the Study:
- To outline the appropriate use of antiviral agents for influenza treatment and prophylaxis in children.
- To highlight the role of neuraminidase inhibitors in managing influenza infections.
- To discuss the implications of antiviral resistance and potential pandemic strains.
Main Methods:
- Review of current clinical guidelines and scientific literature on pediatric influenza management.
- Analysis of antiviral resistance patterns to adamantanes and neuraminidase inhibitors.
- Evaluation of data on H5N1 avian influenza virus susceptibility to antivirals.
Main Results:
- Neuraminidase inhibitors are safe and effective for pediatric influenza treatment and prophylaxis.
- Adamantane resistance is widespread, making them less effective.
- Oseltamivir and zanamivir show susceptibility against H5N1 avian influenza virus isolates.
Conclusions:
- Antiviral therapy is recommended for high-risk children or those with moderate-to-severe influenza to reduce symptom duration.
- Prophylaxis is indicated for unvaccinated high-risk children, close contacts, and during institutional outbreaks.
- While promising, further research is needed on H5N1 treatment efficacy and optimal dosing in humans.
Abstract:
Antiviral agents are available that are safe and effective for the treatment and prophylaxis of influenza virus infections in children. The neuraminidase inhibitors (oseltamivir [Tamiflu] and zanamivir [Relenza]) are preferred agents because of current widespread resistance to the adamantanes (amantadine [Symmetrel] and rimantadine [Flumadine]). Therapy should be provided to children with influenza infection who are at high risk of severe infection and to children with moderate-to-severe influenza infection who may benefit from a decrease in the duration of symptoms. Prophylaxis should be provided (1) to high-risk children who have not yet received immunization and during the 2 weeks after immunization, (2) to unimmunized family members and health care professionals with close contact with high-risk unimmunized children or infants who are younger than 6 months, and (3) for control of influenza outbreaks in unimmunized staff and children in an institutional setting. Testing of current H5N1 avian influenza virus isolates, the potential agents of pandemic influenza, suggests susceptibility to oseltamivir and zanamivir. Because no prospective data exist on the efficacy of these agents in humans for H5N1 strains, the dosage and duration of therapy in adults and children may differ from those documented to be effective for epidemic influenza strains.
More Related Videos
 09:07
Using Zebrafish Models of Human Influenza A Virus Infections to Screen Antiviral Drugs and Characterize Host Immune Cell Responses
Published on: January 20, 2017
 05:21
A Luciferase-fluorescent Reporter Influenza Virus for Live Imaging and Quantification of Viral Infection
Published on: August 14, 2019
Related Concept Videos
 01:29
Respiratory Syncytial Virus Disease
 01:30
Inhibitors of Viral Protein Synthesis
 01:25
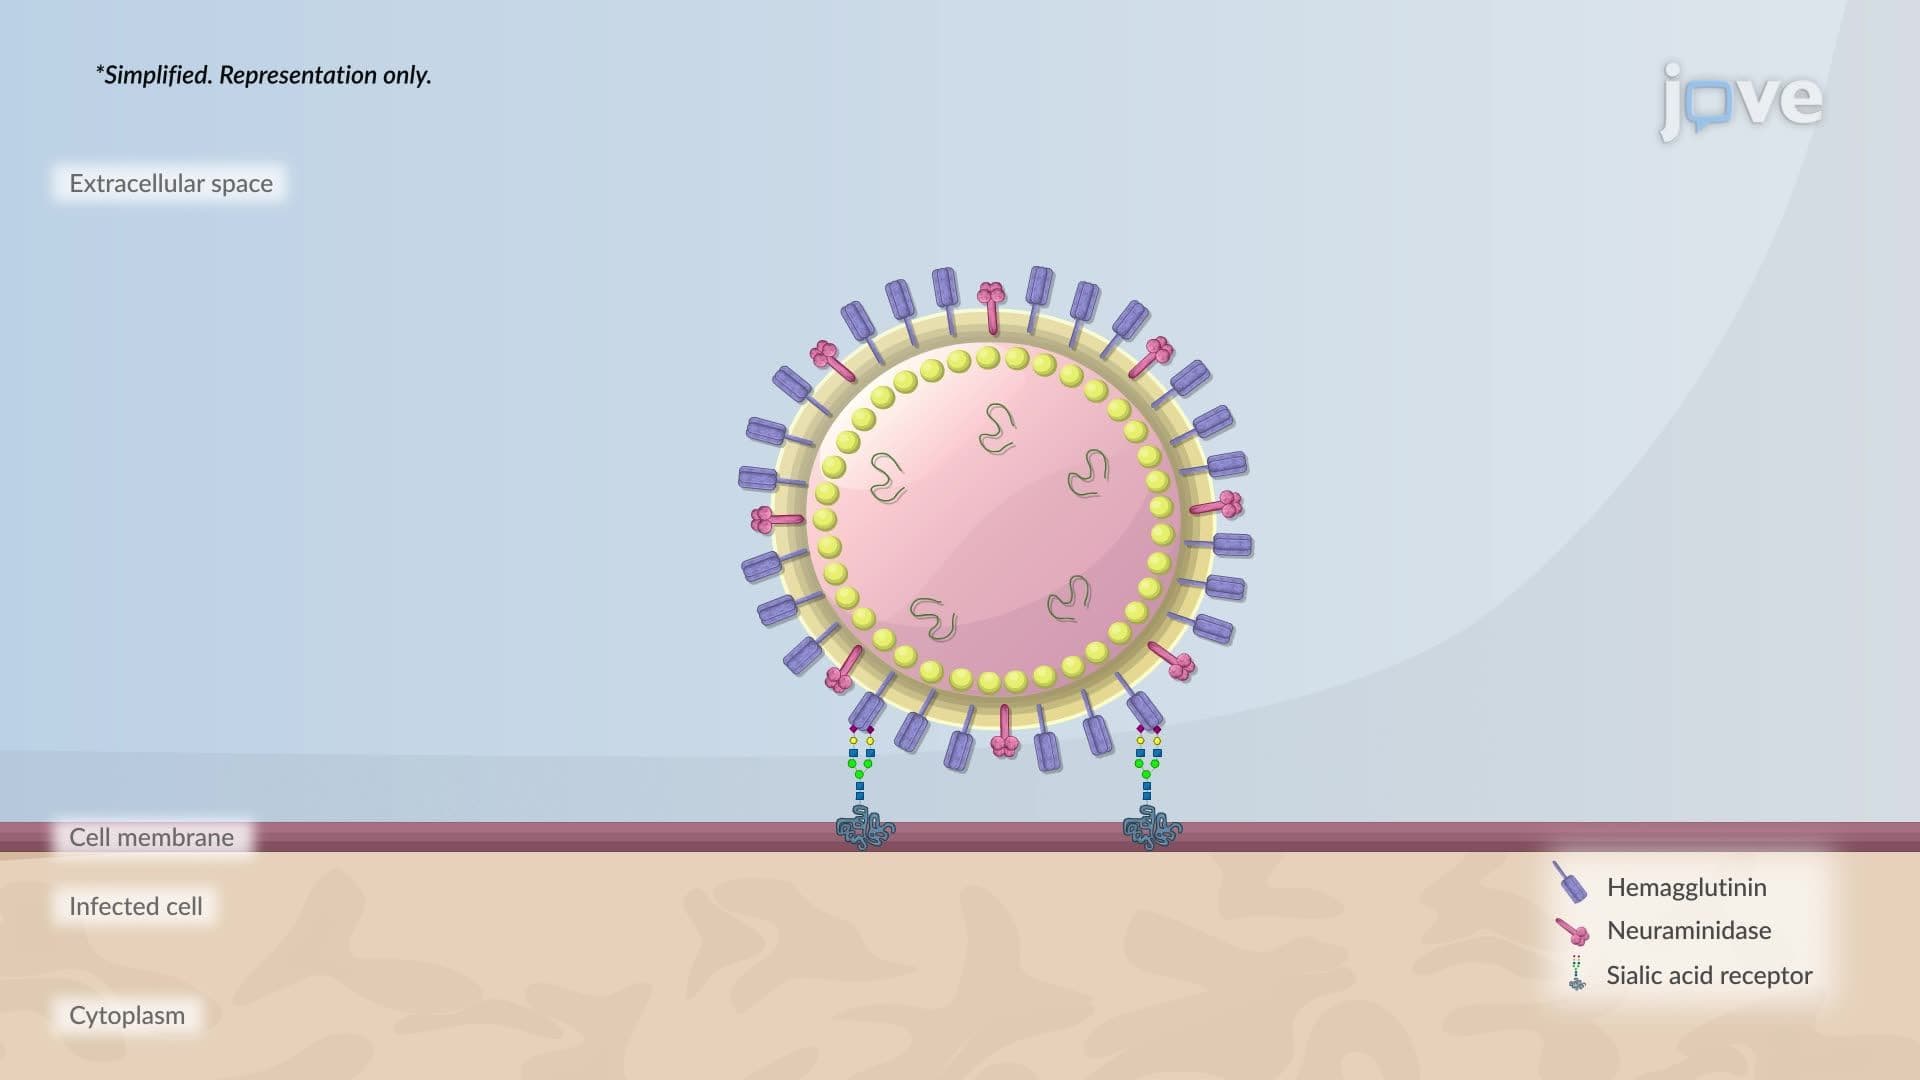
Inhibitors Of Virion Release
 01:22
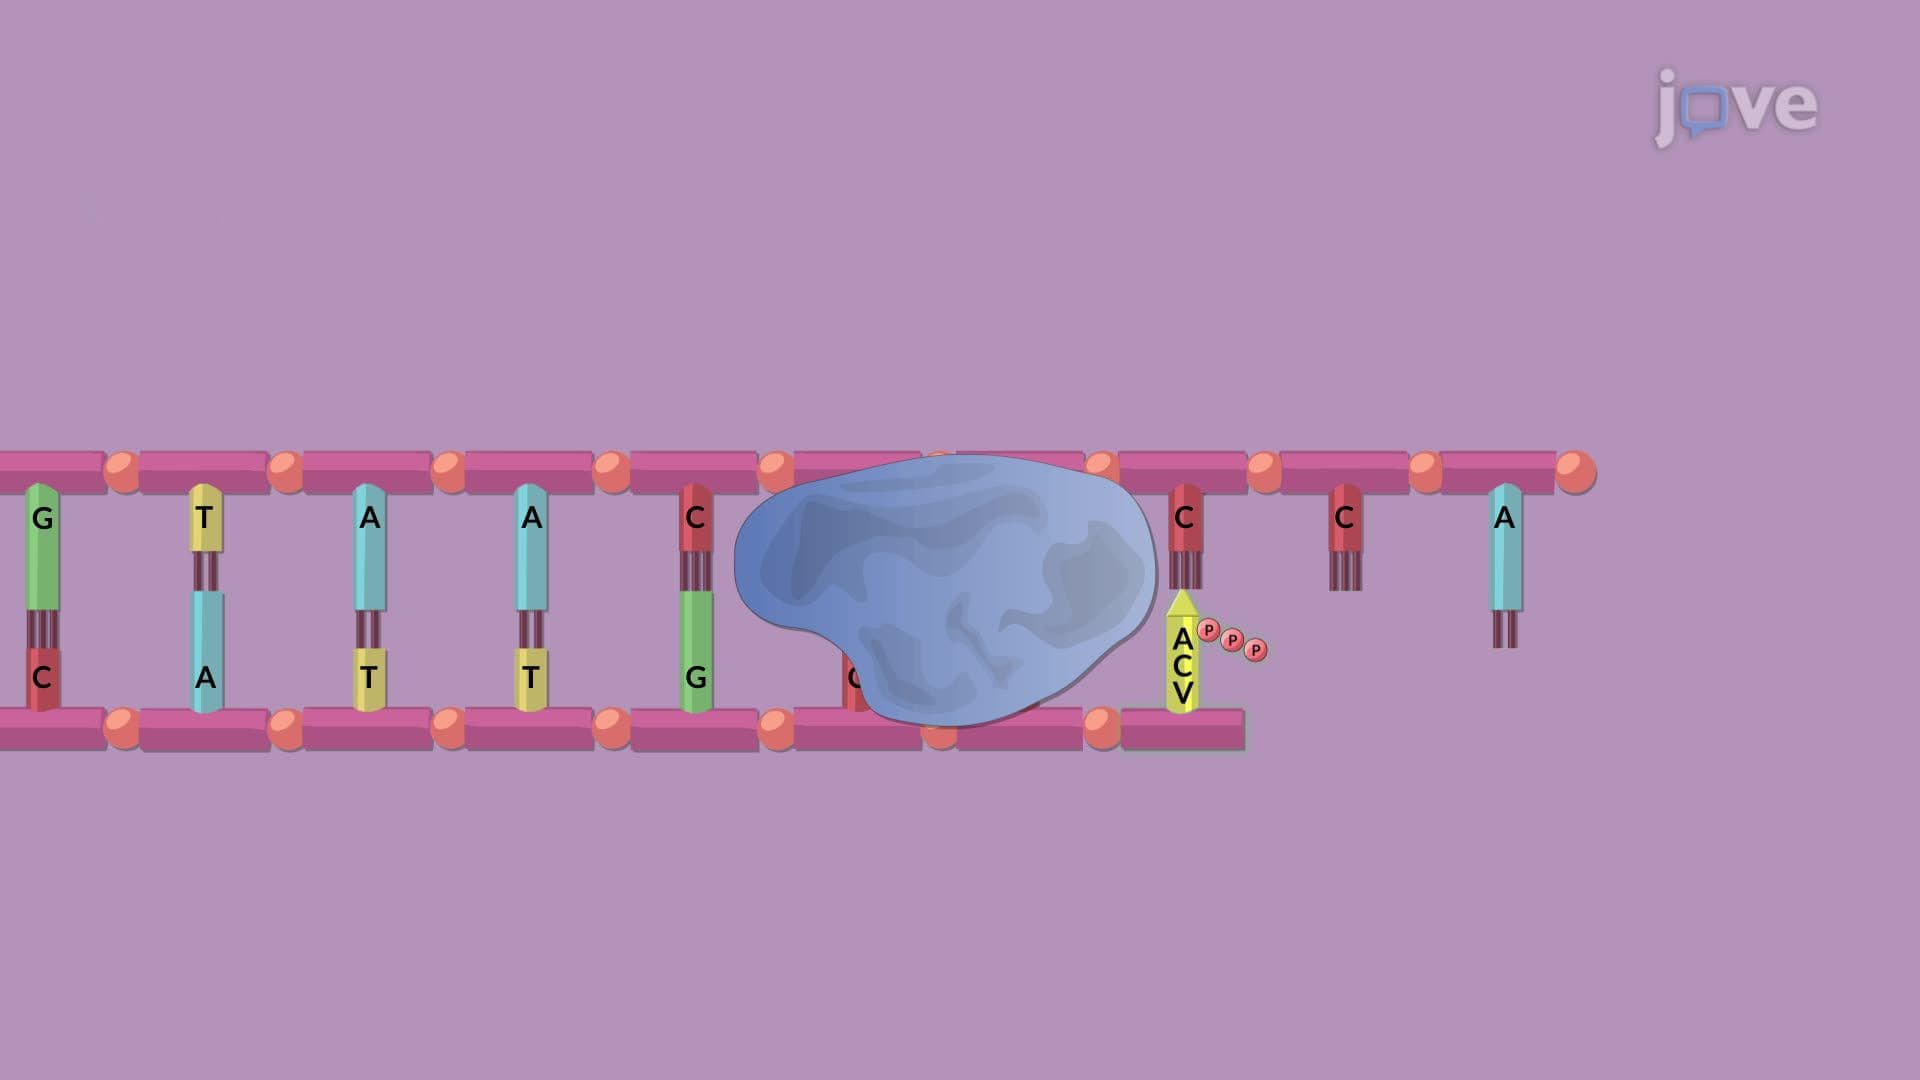
Antiviral Nucleoside Inhibitors
 01:27
Influenza
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion