Related Experiment Video
Updated: Jul 15, 2026


Fecal Glucocorticoid Analysis: Non-invasive Adrenal Monitoring in Equids
Published on: April 25, 2016
Urinary acidification assessed by simultaneous furosemide and fludrocortisone treatment: an alternative to ammonium
S B Walsh1, D G Shirley, O M Wrong
1Department of Physiology and Centre for Nephrology, Royal Free and University College Medical School, London, UK. s.walsh@medsch.ucl.ac.uk

Abstract:
Distal renal tubular acidosis (RTA) can lead to rickets in children or osteomalacia in adults if undetected. This disorder is normally diagnosed by means of an oral ammonium chloride-loading test; however, the procedure often leads to vomiting and abandonment of the test. In this study, we assess an alternative, more palatable approach to test urinary acidification. This was achieved by the simultaneous oral administration of the diuretic furosemide and the mineralocorticoid fludrocortisone to increase distal tubular sodium delivery, principal cell sodium reabsorption, and alpha-intercalated cell proton secretion. We evaluated 11 control subjects and 10 patients with known distal RTA by giving oral ammonium chloride or furosemide/fludrocortisone in random order on separate days. One control and two patients were unable to complete the study owing to vomiting after NH4Cl; however, there were no adverse effects with the furosemide/fludrocortisone treatment. The urine pH decreased to less than 5.3 in the controls with both tests, whereas none of the patients was able to lower the urine pH below 5.3 with either test. We conclude that the simultaneous administration of furosemide and fludrocortisone provides an easy, effective, and well-tolerated alternative to the standard ammonium chloride urinary acidification test for the diagnosis of distal RTA.
Related Concept Videos
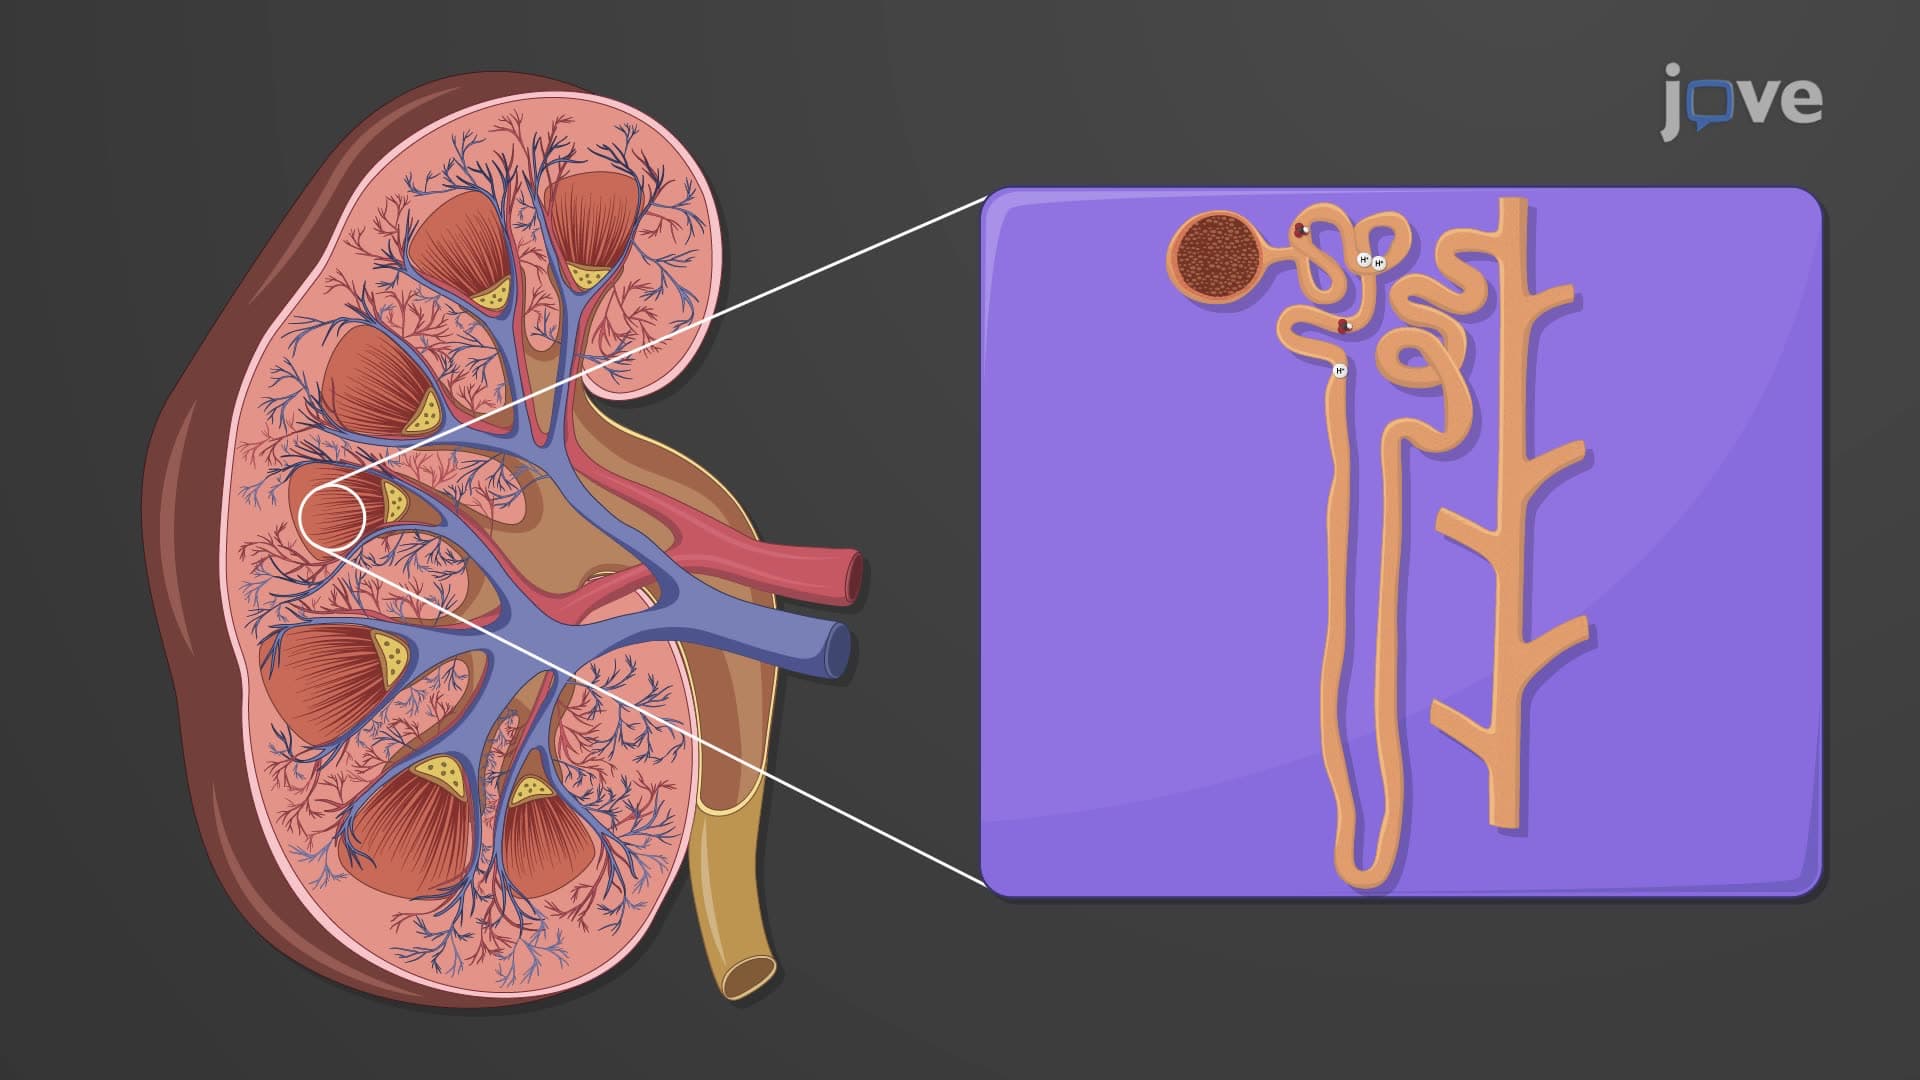 01:29
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:20
Acute Kidney Injury V: Interprofessional Care
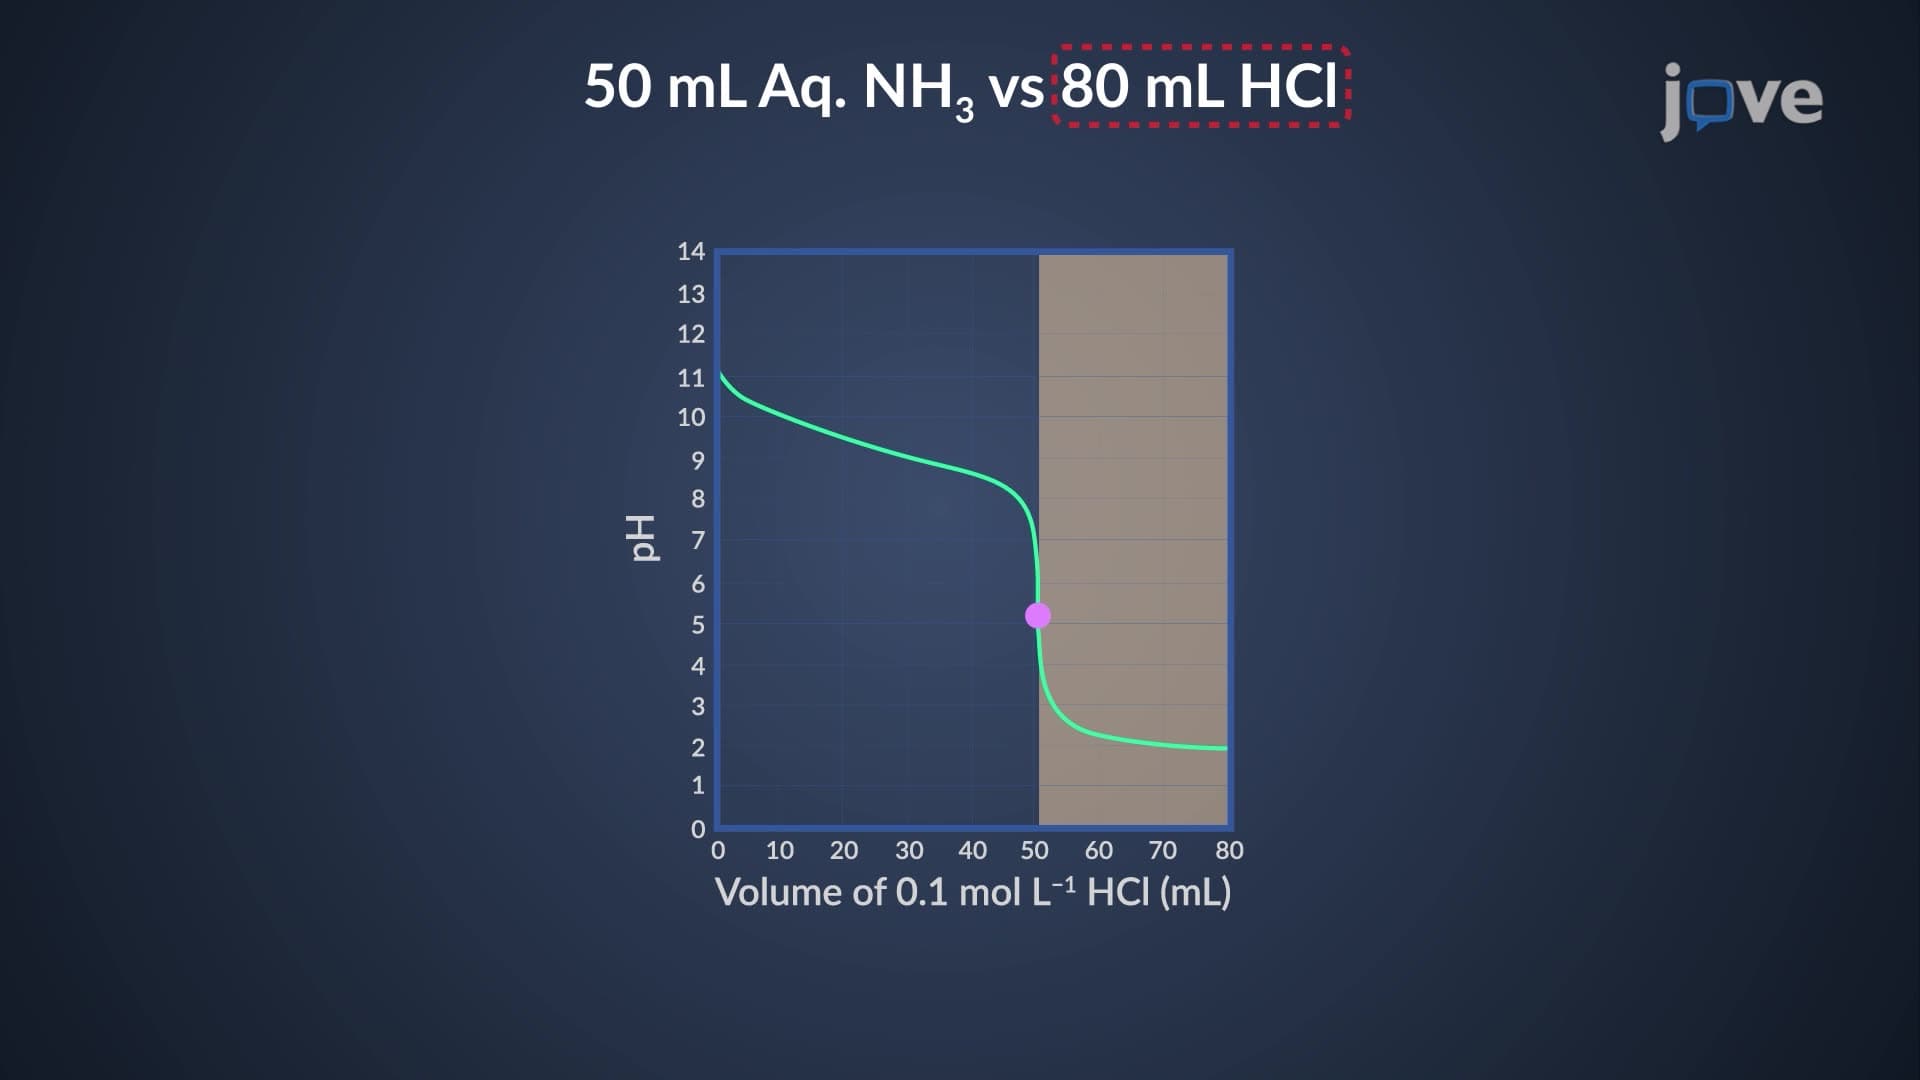 01:20
Titration of a Weak Base with a Strong Acid
Using the ICE table and substituting the Kb value, we calculate the initial pH of 50 mL of 0.1 M ammonia to be 11.11. Addition of 25 mL of 0.1 M hydrochloric acid to this solution of ammonia results in a buffer with an equal concentration of ammonia and ammonium ions. The pH of this buffer can be calculated by substituting these...
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:30
Urinary Tract Calculi III: Medical Management
 01:30
Continuous Renal Replacement Therapy